


L2-L3 Disc Bulge & Herniation: Signs, Symptoms and Treatment
L2-L3 sits high in the lower back, beside the nerve roots that serve the front of the thigh and the knee. A disc bulge between L2 and L3 that presses on a nerve can cause aching, burning, tingling or numbness in the front of the thigh. It can reach the inner knee or the groin, and the knee may feel weak on stairs or when rising from a chair. Others feel only a cramp-like ache in the back or buttock.
Most L2-L3 disc problems follow an injury, sudden or repeated, or repeated harmful strain from long sitting, bending and twisting. Yama Zafer, D.C., describes the damage as progressive, from a bulge to a protrusion, prolapse and herniation, often with no pain at first.
Care starts by examining the back, the nerves and the hip, since hip problems can feel alike. Any MRI is read alongside those findings. Treatment combines gentle, non-rotatory chiropractic, physiotherapy, hands-on muscle work and spinal decompression, kept within what the patient can comfortably tolerate. Twisting, cracking and yoga are avoided, and exercise starts only when the body is ready. The sections below explain the examination tests, MRI stages, causes, what care involves and avoids, and daily habits.
This guide, L2-L3 Spine: Where It Is, Disc Bulge Symptoms and Nerves, is published by Chiropractic Specialty Center, Bukit Damansara (KL) main center: WhatsApp+60 17 269 1873 Call+603 2093 1000
L2-L3 Disc Bulge: Key Takeaways
| Question | What to know |
|---|---|
| What L2 and L3 control | The L2 and L3 nerve roots carry feeling from the groin, the front of the thigh and the inner knee. They also help power the muscle that straightens the knee. |
| Is it serious? | Yama Zafer, D.C., teaches that no back pain is normal, so even pain that comes and goes deserves an assessment. New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours. |
| Does it mean surgery? | Surgery is the last option. It is considered only when conservative care is not working, or in severe cases such as a sequestered disc or an infection. |
| What decides the next step? | The examination: the femoral nerve stretch test, the knee reflex, thigh strength and feeling, and the hip. When a disc problem is suspected, an MRI is arranged, because a final diagnosis is never guessed. |
| Spinal cord or nerve roots? | In most adults the spinal cord ends at about the first lumbar bone (Elfiky 2025). So at L2-L3 the canal holds nerve roots, not the cord. |
| Can a bulge go back to normal? | Care targets the strain on the disc, not how a scan looks. It decreases what harms the disc and increases what supports it, through treatment and daily habits. |
| How is progress checked? | The first visit's tests are repeated. Without improvement by the 5th session the plan is reassessed, and by the 10th session the next step is discussed together. |
L2-L3 Spine and Disc Bulge: Page Guide and Key Sections
- Where Are L2 and L3 on the Spine? L1 to L5 Numbers Explained
- Arranging an Assessment for Thigh and Knee Symptoms in KL
- L2-L3 Disc Bulge Symptoms: Thigh, Knee and Groin
- Femoral Nerve Stretch Test & Other L2 and L3 Checks
- MRI Terms for L2 and L3: The Stages of Disc Damage
- Why the Disc Between L2 and L3 Gets Damaged: Common Causes
- L2-L3 Disc Bulge Treatment Without Surgery: What Care Involves
- Daily Habits That Protect the Disc Between L2 and L3
- How a Disc Herniates: Bulge, Prolapse and Herniation Explained
- FAQ: L2-L3 Disc and Nerve Care
- How to Read This L2-L3 Guide
- References
Where Are L2 and L3 on the Spine? L1 to L5 Numbers Explained
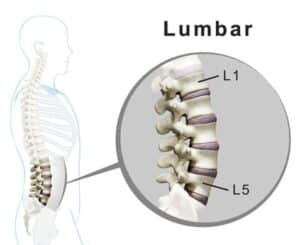
The lower back, or lumbar spine, has five bones, numbered L1 to L5 from the top down. Each disc is named after the two bones it sits between. So L2-L3 is the disc and joints between the second and third lumbar bones, in the upper half of the lower back.
At each level, a spinal disc cushions the bones at the front, and a pair of facet joints at the back guides and limits movement. Yama Zafer, D.C., calls mobility the disc's most important function: "Bending, twisting, all of this is because of the spinal disc."
Two nerve roots matter at this level. The L2 root leaves the spine through the side opening at L2-L3. The L3 root passes behind the disc and leaves one level lower. A bulge toward the back of the canal usually presses on the L3 root. One out in the side opening presses on the L2 root.
In most adults the spinal cord ends at about the lower part of the first lumbar bone (Elfiky 2025). So at L2-L3 the canal holds a bundle of nerve roots, called the cauda equina, rather than the cord itself.
Arranging an Assessment for Thigh and Knee Symptoms in KL
Thigh and knee symptoms can come from the hip as well as from L2-L3, so the first visit compares the two. It includes the femoral nerve stretch test, the knee reflex, thigh strength and feeling, and hip and back movement. Any MRI or X-ray is reviewed against those findings. Either Kuala Lumpur center can arrange it:
- Bukit Damansara (KL, main center): Call +603 2093 1000 or WhatsApp +60 17 269 1873 to see the Bukit Damansara / KL center.
- Bandar Sri Damansara (KL): Call +603 6262 5777 or WhatsApp +60 12 455 6939 to see the Bandar Sri Damansara center.
Directions and opening hours for both centers are on CSC Locations in Kuala Lumpur.
L2-L3 Disc Bulge Symptoms: Thigh, Knee and Groin
The symptoms of an L2-L3 disc bulge depend on whether it reaches a nerve root, and which one.
When the L3 Nerve Root Is Pressed
Pain, burning, tingling or numbness runs down the front of the thigh, often to the inner knee and sometimes the upper shin. The big muscle at the front of the thigh can weaken. The knee may then give way on stairs or when standing up from a chair. The knee reflex can be reduced.
When the L2 Nerve Root Is Pressed
Symptoms sit higher, in the groin and the upper front of the thigh. In one study, reduced feeling at the front of the thigh was the examination finding that pointed to the L2 root (Suri 2011).
Back and Buttock Pain Without Thigh Symptoms
Some people feel only a cramp-like ache high in the lower back or in the buttock, and some feel nothing at all. Yama Zafer, D.C., notes that "the most common symptom of spinal disc damage is zero." He also explains that sitting and bending forward raise the pressure inside the disc.
He stresses that no back pain is normal: "if you experience it even on an intermittent basis, you need to pay attention."
When a child or teenager has back pain, the guide to chiropractic care for children explains how the whole lower back, L2-L3 included, is assessed with growth in mind.
When Symptoms Need Urgent Care
With an L2-L3 disc bulge, any new symptom is weighed alongside the back or leg pain. New or worsening numbness around your genitals, between your genitals and anus, or around your anus needs urgent medical attention: a thorough assessment at a hospital emergency department straight away, within hours. New difficulty passing urine needs the same urgent assessment, even if bladder and bowel control remain intact, and so does any loss of that control. Several conditions can cause these symptoms. Some may call for an invasive procedure, but being assessed helps identify the cause and does not automatically lead to surgery.
Leg weakness that keeps getting worse should not be ignored. It calls for a careful assessment by a competent provider, and conservative care can continue only while the weakness itself is improving.
Femoral Nerve Stretch Test & Other L2 and L3 Checks
The L2, L3 and L4 nerve roots join to form the femoral nerve. It runs down the front of the thigh and powers the big muscle that straightens the knee. It also carries feeling from the front of the thigh and, through a branch, the inner shin.
The examination follows the order Yama Zafer, D.C., uses for every lower back problem. Questions about the history come first, then movement, orthopedic and nerve tests and muscle testing. Imaging is decided only after that. For the L2 and L3 roots, the key checks are:
- The femoral nerve stretch test: lying face down, the knee is bent slowly. Pain at the front of the thigh points to an irritated nerve root in the middle of the lower back.
- The knee reflex, tapped just below the kneecap.
- Thigh strength, including standing up from a chair.
- Feeling over the front of the thigh, the knee and the inner shin.
- Hip movement, because hip problems can cause the same thigh pain.
One study checked examination findings against MRI (Suri 2011). The femoral nerve stretch test and the knee reflex each made pressure on the L2, L3 or L4 roots much more or much less likely. Combining the stretch test with the knee reflex, or with standing up from a chair, made the picture clearer still.
Together with any MRI, these checks help tell an L2-L3 problem apart from hip, knee or groin problems that feel similar.
MRI Terms for L2 and L3: The Stages of Disc Damage
An MRI report for L2-L3 uses terms that follow the stages of disc damage. Yama Zafer, D.C., names those stages in the video on this page. In his words, "A bulge becomes a protrusion, then a prolapse, then a herniation, a rupture, fragmentation, and sequestration." He adds that small tears can be missed on an MRI, which is one reason a report is always read with the examination.
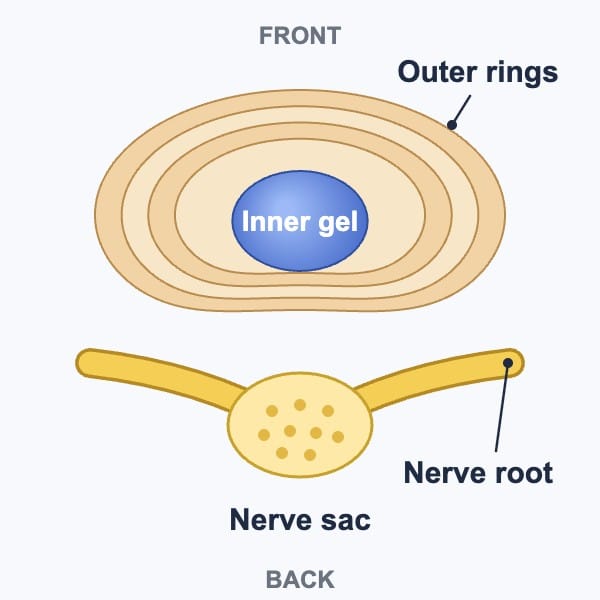
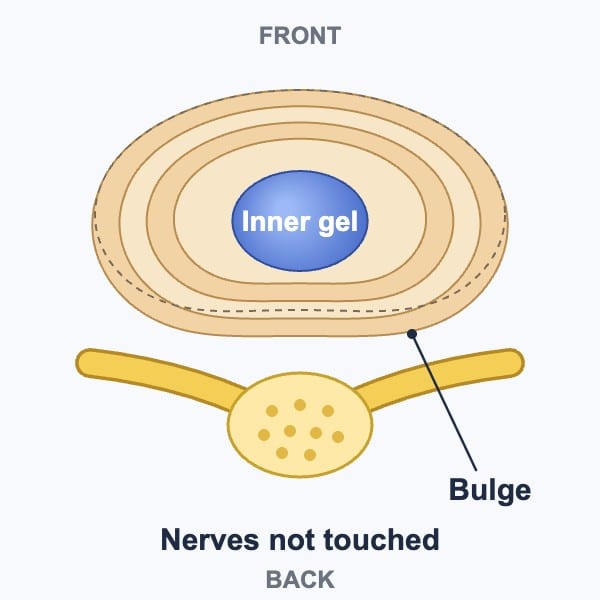
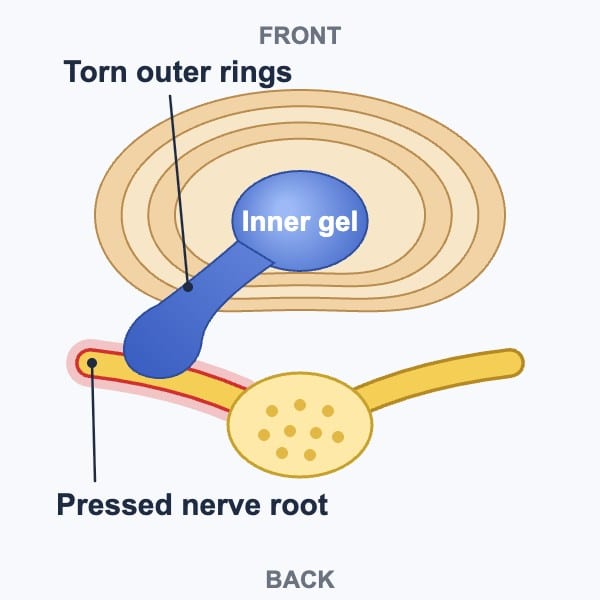
The drawings below show a lumbar disc, such as L2-L3, seen from above. The front of the body is at the top, and the nerve roots and the sac around them sit behind the disc.
| Term on the report | What it means |
|---|---|
| Disc bulge | In his definition: swelling of the outer disc fibers that has not yet pressed on or moved the nerves or the thecal sac around them. |
| Protrusion and prolapse | The next stages: the bulge has grown enough to press on the thecal sac, the nerves or both, in his definition. |
| Herniation | The inner gel pushes further out through the weakened outer rings, toward the nerves. |
| Extrusion | In his words, "an extrusion is a progression of a herniation." |
| Rupture, fragmentation and sequestration | The later stages: the outer wall gives way, and pieces of disc material can break off and separate. |
| Annular tear | A tear in the outer rings. Once these fibers are damaged, the inner part is damaged too, and the reverse, as he explains. |
| Disc desiccation or degeneration | The disc has lost water and height. He links it to daily load and poor habits, and notes that it does not mean pain starts at once. |
| Facet hypertrophy | Enlarged facet joints. A narrowed disc puts more stress on them, in his answers on disc narrowing. |
| Ligamentum flavum hypertrophy | A thickened ligament behind the nerves. A narrowed disc can let it buckle into the canal. |
| Foraminal narrowing | Less room in the side opening where the L2 root leaves the spine. |
| Spondylolisthesis | One vertebra sits forward on the one below. In his answers it is more common at L4-L5 and L5-S1. |
Each term describes what the scan shows. Whether it explains the symptoms is decided with the examination, never from the report alone.
Why the Disc Between L2 and L3 Gets Damaged: Common Causes
Most damage at L2-L3 follows an injury, whether one sudden event or many small ones, or strain repeated over months and years. Yama Zafer, D.C., puts the main cause plainly: what damages a disc is "our lifestyle, our poor habits." The common causes are:
- Long sitting, which presses the body's weight down on the discs, more so when leaning forward.
- Poor posture kept up for months or years: it strains the muscles, then the ligaments and joints, and finally reaches deep into the disc.
- Bending and twisting at the waist, above all while lifting.
- Standing for long periods.
- Gym work that twists, bends or lifts free weights.
- A fall, a sports injury or an awkward lift.
He also describes how daily load adds up: "as the day progresses, the weight comes down: the discs degenerate. Once degeneration occurs, then the fibers tear."
L2-L3 Disc Bulge Treatment Without Surgery: What Care Involves
Every case begins with a thorough assessment, and the plan is then matched to the tissues involved. At CSC, chiropractors and physiotherapists work together on one plan, kept within what the patient can comfortably tolerate. Depending on the findings, the plan can include:
- Gentle, non-rotatory chiropractic adjustment, such as chiropractic manipulation that is non-rotatory using the Activator instrument, and flexion-distraction.
- Spinal decompression on a decompression table.
- Physiotherapy methods: therapeutic ultrasound, electrotherapy, shockwave therapy and high-intensity laser therapy.
- Cold therapy, and heat only where the area is not inflamed.
- Trigger point therapy and myofascial work for the muscles around the irritated level.
- Stretching, strengthening and balance exercises, added only when the body is ready.
His motto for comfort is "No pain, more gain." The patient tells the clinician at once if anything hurts, because discomfort during care may increase inflammation and pain later.

What Care and Habits Are Avoided
- Twisting and cracking. Rotational or aggressive chiropractic, physiotherapy or manual therapy is not used on a damaged disc. He is clear that cracking and twisting "should not be done on a spine that has a damaged disc," even by a very experienced chiropractor.
- Spine pulling such as the Ring Dinger®, towel jerks and the Y-Strap.
- Stretching or exercise in the early stage, apart from Kegel exercises, and hard hamstring stretches at any stage.
- Yoga, which must be avoided with an L2-L3 disc problem, as with every other spinal disc problem, whatever the style of class.
- Deadlifts, free weights and swimming laps.
- Hot packs on an inflamed area.
- Thai massage, or anyone walking on the back.
- Bending and twisting at the waist in daily life, which he advises keeping to zero.
When Exercise Starts
Exercise begins only when the body is ready, usually from about the 5th to 7th session, and for some from the 3rd. In his words, "If you're not ready and you do these exercises, you create more problems." Kegel exercises for the pelvic floor can start right away.
The first exercises are usually wall-assisted squats, cat and camel, and core canister breathing. Strengthening for the glutes, hamstrings, calves and thigh muscles is added by severity.
How Progress Is Checked
The tests from the first visit are repeated, pain is scored on the visual analog scale (VAS), and the patient's own feedback is recorded. Yama Zafer, D.C., sets two review points. In his words, "if improvements are not present by the fifth session, your chiropractor should assess you." Without improvement by the 10th session, whether to stop or continue is decided together.
When Surgery Is Considered
Surgery is the last option. In his words, "if you have spinal disc issues, even if it's a herniation or bulge, surgery should be the last option. Exhaust conservative route." It is considered when the conservative plan is not working. It is also considered in severe cases: a sequestered disc, numbness around the genitals or anus, bladder or bowel problems, or infection. He does not recommend steroid injections or surgery as a first choice, and refers to a doctor when the signs call for it.
Daily Habits That Protect the Disc Between L2 and L3
Yama Zafer, D.C., puts habits ahead of treatment: "The most important thing is not the treatment. The most important thing is to make lifestyle changes." His advice for a damaged L2-L3 disc, as for any damaged lumbar disc:
- Sitting: with acute back pain, stand up every 15 minutes and walk for 10 to 20 seconds. People without back problems should still take a break every 30 to 45 minutes. Sit with the knees level with the hips or slightly above, the feet under the knees, and the hips back against the chair.
- Sleep: at least six hours. Sleep on the right side first, the left side second, or on the back with a bolster under the knees. On the side, a pillow keeps the spine straight and a bolster sits between the knees.
- Lifting: avoid it, and if it cannot be avoided, keep the load under 2 kg.
- Travel: avoid long road trips. As a passenger, sit in the front with the seat reclined. When driving, stop every 45 to 60 minutes to get out, walk and stretch the calves.
- Ice: two to three times a day for 10 to 15 minutes, at least two hours apart. Wrap the ice pack in cloth and set a timer.
- Standing: stand tall, with the belly button drawn toward the spine and the weight even on both feet. Keep the knees soft rather than locked.
- Sport: return only after recovery. Skip any activity that hurts now or brings pain on within 72 hours, because inflammation can take that long to show.
He adds that habits are easiest to change while the back still hurts, "because when you're feeling better, you're not going to change anything."
How a Disc Herniates: Bulge, Prolapse and Herniation Explained
Key moments and an edited transcript of this video are on the Why Spinal Discs Get Damaged page.
A spinal disc bulge or "slipped disc" develops in stages. This short animation shows what a healthy disc looks like, how daily load degenerates it, and how a bulge can progress and press on spinal nerves.
CHAPTERS
0:00 A healthy spinal disc: nucleus pulposus and annulus
0:28 How daily load degenerates the disc
0:54 How disc damage inflames nerves and relates to sciatica
1:19 Animation: herniation and the stages of disc damage
1:46 When to get assessed
What You'll Learn
- What a healthy disc is made of: the nucleus pulposus and the annular fibers
- Why discs degenerate under daily load, and how annular tears begin
- How the nucleus migrates toward the weakest point and bulges
- The stages of disc damage: bulge, protrusion, prolapse, herniation, rupture, fragmentation, and sequestration
- Why disc changes can irritate spinal nerves and relate to sciatica
This video is presented by Yama Zafer, D.C., Doctor of Chiropractic, Cleveland University-Kansas City.
Planning a visit? You can review the current chiropractic price in Kuala Lumpur and physiotherapy fees in Kuala Lumpur before you come in.
FAQ: L2-L3 Disc and Nerve Care
Can a Disc Bulge Between L2 and L3 Go Back to Normal?
Yama Zafer, D.C., describes disc damage as progressive, so care aims to stop what keeps damaging the disc rather than to make it look normal again. He explains that a damaged disc "can go rapidly or it can take years." What a person can change is the load on the disc. That means decreasing what is harmful, such as long sitting, bending, twisting and lifting. It also means increasing what is beneficial: care kept within comfort, the right exercise once the body is ready, ice and enough sleep. Progress is judged by repeating the first visit's tests rather than by expecting the MRI to look different.
What Are the Symptoms of L2 and L3 Disc Degeneration?
Degeneration at L2 and L3 can cause no symptoms for a long time. In the words of Yama Zafer, D.C., "Degeneration is part of life, but it doesn't mean that the moment you degenerate, you'll have pain." When symptoms come, they can include a cramp-like ache high in the lower back or buttock, and thigh pain once a nerve is involved. His answers on disc narrowing add that a narrowed disc can affect the nerves before much pain is felt. Leg numbness, weakness or trouble standing and walking can follow. It also puts more stress on the facet joints and can let the ligament behind the nerves buckle inward, narrowing the canal.
How Long Does Recovery From an L2-L3 Disc Bulge Take?
The timeline is set after the examination, because the pace varies. It depends on how severe the damage is, other health conditions, how closely the advice is followed and how consistent care is. These are the factors Yama Zafer, D.C., names in his video on chiropractic safety. Progress is measured rather than guessed: the first visit's tests are repeated, pain scores are compared and the patient's feedback is recorded. Without improvement by the 5th session the plan is reassessed, and without improvement by the 10th, whether to continue is discussed together. He also observes that a problem neglected for a long time may leave some lasting symptoms or flare-ups.
Is an MRI Needed for a Disc Problem Between L2 and L3?
An MRI is arranged when the examination suggests a disc problem, because Yama Zafer, D.C., never guesses a final diagnosis. He also teaches that not every patient needs imaging: it is decided case by case, after a thorough assessment. For a disc, an MRI is his gold standard. It shows the bone, joints, muscles, ligaments and the space the nerves use, with zero radiation. An X-ray costs less but shows only bone, so it is used for questions of alignment, and for a slipped vertebra together with an MRI. Bringing any earlier images and reports to the first visit lets them be read with the examination.
Should I See a Chiropractor or Physiotherapist?
Both, working together, is the advice of Yama Zafer, D.C.: "Don't choose between one or the other. Choose both." He explains that holistic care means comprehensive care, and it "cannot be comprehensive if it is a singular approach." Chiropractic and physiotherapy are separate professions with separate registration. At CSC, chiropractors use gentle, non-rotatory methods on the joints of the spine. Physiotherapists work on the muscles, movement and strength around them, with ultrasound, electrotherapy and exercise once the body is ready. For an L2-L3 disc problem, one plan draws on both.
Can I Still Go to the Gym With a Bulging Disc?
The gym is discouraged at first and possible later, within clear limits. Yama Zafer, D.C., advises avoiding free weights for the first two to six months. Once the disc is stable, free weights, deadlifts and leg presses still stay off the list. Some machines can be used: adductor and abductor machines, leg curls and leg extensions, light rowing and lat pulldowns. Treadmill walking is done at zero incline, because an incline adds load on the lumbar discs. Swimming laps are avoided too, and walking in water is gentler. Any exercise that brings pain on within 72 hours is dropped, and each step up is agreed with the clinician.
How to Read This L2-L3 Guide
The reader questions at the end of this page are genuine questions left by readers, kept in their own words, and the replies are general education only. They are not a diagnosis or a care plan for any individual, online information has limits, and an in-person assessment is needed before any care.
References
- Elfiky T, El Mansy Y, Stienen MN, et al. Magnetic Resonance Imaging-Based Anatomy of the Conus Medullaris: Variations of Location and Morphology. World Neurosurg. 2025;195:123646.
- Suri P, Rainville J, Katz JN, et al. The accuracy of the physical examination for the diagnosis of midlumbar and low lumbar nerve root impingement. Spine (Phila Pa 1976). 2011;36(1):63-73.
These references describe lumbar anatomy and the examination of the lumbar nerve roots in general. Neither of them evaluates care at Chiropractic Specialty Center.
The Author of L2-L3 Spine: Where It Is, Disc Bulge Symptoms and Nerves
L2-L3 Spine: Where It Is, Disc Bulge Symptoms and Nerves was written by Yama Zafer, D.C., who has 30+ years in chiropractic and physiotherapy and founded Chiropractic Specialty Center in Kuala Lumpur in 2006.
Last Updated: L2-L3 Disc Bulge & Herniation: Signs, Symptoms and Treatment
L2-L3 Disc Bulge & Herniation: Signs, Symptoms and Treatment was last reviewed and updated on October 9, 2026.
I have been having pain in my back for the last 6 months. It has increased in the lower part and since the last 8 days. I feel the pain when bending, exercising, morning pain, and nightly pains. Pain also runs down my legs. What can be done?
Back pain for six months that has worsened over the last eight days and now runs down your legs needs an assessment rather than more waiting. Pain is a symptom, not a yardstick, and ignoring it lets a problem progress. The examination should check how far down the leg pain reaches, the strength, reflexes and feeling in both legs, and which movements ease or worsen it, and imaging is used when a disc problem is suspected. Morning stiffness that lasts more than half an hour and eases with movement, or night pain that wakes you, should also be mentioned to your doctor, because those patterns are checked for other causes.
Until then, avoid bending, twisting, lifting and any exercise that brings on pain. Stand up and walk briefly every 15 minutes while the pain is acute, sleep at least six hours on your side or on your back with a pillow under your knees, and ice the area two to three times a day for 10 to 15 minutes, at least two hours apart, wrapped in a cloth. Care for a disc problem at CSC is gentle, without twisting and within what you can comfortably tolerate, with exercise added when your body is ready.
New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours.
Greetings,
My name is Chitranjan. I have problems with C2, C4, C5-C6, and lumbar L4, L5, S1. These issues were less severe 5 to 6 months ago but have now worsened. I consulted a doctor who suggested surgery after an MRI.
The discomfort is such that below the waist, there is numbness and tingling, and my legs have become so weak that I am unable to walk properly. However, I want to tell you that I do not have any pain, just numbness and weakness in my legs.
Can you please tell me why I experience weakness but no pain? I am taking some medicines prescribed by my doctor, and I do feel some relief, but I am also concerned because even if I walk a little, my feet and legs don't function well. What should I do to avoid surgery? Please advise.
🙏
A pinched nerve or a pressed spinal cord can cause numbness and weakness with little or no pain, because the nerve fibers that carry pain and the ones that control the muscles can be affected differently. With findings in both your neck and your lower back, the numbness and weakness below your waist may come from the neck as well as the lower back, since pressure on the spinal cord in the neck affects everything below it. Ask your surgeon which region explains your leg symptoms and whether the MRI shows any change inside the spinal cord.
For disc problems, surgery should be the last option after conservative care has had a fair trial, but nerve function that keeps getting worse calls for prompt assessment, and severity can change the order of care. While the spinal cord in the neck may be involved, the neck must not be cracked, twisted or pulled.
Weakness that keeps getting worse should not be ignored. It calls for a careful assessment by a competent provider, and conservative care can continue only while the weakness itself is improving. New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours.
I have had herniated discs in L4 and L5 since 1986, and the pain was relieved with pain pills and occasionally seeing a chiropractor. On July 1st, I saw my Chiropractor of 12 years for an adjustment because of slight numbness in my right fingertips. After one adjustment, I could barely walk and was in pain, so on the 12th, I went again, but he refused to treat me and took me off his patient list.
I went to another Chiropractor, hoping she could undo what he had done. After three adjustments, the pain in my hip., shin and groin area were unbearable, and I could only walk with a Walker. She also refused to treat me, so I went to a neurosurgeon, and he ordered a new MRI and injection in my spine. I had never had trouble with L2 and L3 before. The injection did not help, and I now have an appointment with a surgeon as I cannot deal with the pain. Do you have a suggestion or opinion of why the Chiropractor caused me to be like this and why can’t it be undone?
I am sorry this has been so hard. No one can tell from a description exactly what happened. With a damaged disc, twisting and cracking manipulation should not be done, even by an experienced chiropractor, because it can irritate the disc and nerves further; gentle methods without twisting are used instead. Whether the adjustments caused the change or the disc was already getting worse can only be judged by comparing your earlier MRI with the new one, so ask for that comparison.
Your new hip, groin and shin pain can come from the upper lumbar levels, L2 and L3, becoming involved. Numbness in the fingertips comes from the neck or the arm, not from the lower back, and together with the trouble walking it is worth asking whether your neck has been examined and imaged. Another adjustment cannot undo a disc injury, so further manipulation is not the answer now. For the surgical consultation, take both scans and ask which level explains your symptoms; surgery has its place, and your surgeon will weigh it with you.
Leg weakness that keeps getting worse should not be ignored. It calls for a careful assessment by a competent provider, and conservative care can continue only while the weakness itself is improving. New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours.
Hi, I had an MRI and was told I had a disc bulge and some arthritis. They told me to get an injection, but I want to try chiro, and I have a terrible time standing up. I slipped and fell into a pothole. What is a disc bulge, and can it be fixed? THANK YOU.
A disc bulge means the outer rings of the disc have swollen outward, but not yet enough to press on the nerves or the sac around them. It is one stage of disc damage, which can go on to a protrusion, a prolapse and a herniation, so it deserves attention even when the pain eases. Care does not push a bulge back into place; it aims to lower the strain on the disc, build strength and change the habits that load it.
Because you fell into a pothole and now have trouble standing up, make sure a fracture has been ruled out before any hands-on care, especially if the MRI was taken before the fall. As a first choice, steroid injections are not something we recommend; conservative care comes first. Chiropractic care for a damaged disc avoids twisting and cracking and uses gentle methods within what you can comfortably tolerate, together with physiotherapy, and exercise is added when your body is ready.
Avoid bending and twisting, and stand up briefly every 15 minutes while the pain is acute. New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours.
Hi there, I have had bad back pain in the lower right side of the back for about seven years now. In the last six months or so, I have started to get awful pain down the right leg above the knee, and now it's going down my shin. The doctors don't seem to know what it is. I have had MRI, but I am on all sorts of pills that don't do much. It's very painful and aches so much.
Please tell me what it might be so I can go back to my doctor and try to get the ball rolling to stop this pain.
Thanks very much for your help. I am from New Zealand.
Pain that started in your lower back and has spread over six months from above the knee down to the shin is moving away from the spine, and that change is the most useful thing to tell your doctor. It usually means a nerve root in the lower back is becoming more involved. Pain along the shin toward the top of the foot often comes from the L5 nerve root, which a disc at L4-L5 commonly pinches.
Ask your doctor which level on your MRI matches that pattern on the right side, and whether a nerve conduction test would help if the scan does not explain it. You can check one thing at home: lift your big toes against light pressure and compare the two sides, and report any weakness. Nerve pain does not always respond to ordinary painkillers, so ask your doctor whether a different approach would suit you.
Conservative care for a disc problem avoids twisting and cracking, stays within what you can comfortably tolerate and adds exercise only when your body is ready, with surgery kept as the last option. Leg weakness that keeps getting worse should not be ignored. It calls for a careful assessment by a competent provider, and conservative care can continue only while the weakness itself is improving. New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours.
I have been suffering from neck pain related to disc desiccation changes at C2, C3 & C4 levels for the last four years. What are your recommendations?
Disc desiccation means the discs have lost some of their water. It is not simply an age-related change. Age is one factor, and genetics, daily habits, lifestyle, previous injury and posture all play a part, which is why it can appear far earlier than most people expect. C2 to C4 are in the upper neck, where problems can send pain into the back of the head as well as the neck, so mention any headaches to your clinician.
Care for a damaged disc in the neck is gentle and specific: no cracking, twisting or forceful neck pulls, and care kept within what you can comfortably tolerate. It combines chiropractic without twisting, physiotherapy and hands-on muscle work, with exercise added when you are ready. Daily habits matter as much as the sessions: keep the top of your screen at about eye level, hold your phone up instead of looking down, use a pillow that keeps your neck level, avoid sleeping on your stomach, sleep at least six hours, and stand up and walk briefly every 15 minutes when you work at a desk.
Pain, numbness or weakness spreading into an arm, or hands that become clumsy, should be checked promptly.
Hi Sir,
As per the MRI scan, my father has an L2-L3 disc bulge. Is it treatable without surgery?
Yes. A disc bulge at L2-L3 is managed with conservative care first, and surgery is the last option, kept for cases where conservative care has had a fair trial and is not working, or for severe problems. The first step is an assessment that compares the MRI with your father's symptoms and examines his back, nerves and hips. The nerves at L2-L3 serve the front of the thigh and the knee, so symptoms there, or a knee that feels weak on stairs, fit that level, while pain running down the back of the leg to the foot usually comes from lower levels.
Care at CSC for a disc bulge combines gentle chiropractic without twisting, physiotherapy, hands-on muscle work and spinal decompression, kept within what he can comfortably tolerate, with exercise added only when his body is ready. For an older person, the plan is usually gentler, with more attention to daily habits, balance and stability. At home, he should avoid bending, twisting and lifting, sleep at least six hours, and stand up for a short walk every 15 minutes while the pain is acute.
New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours.
Hi,
As per the MRI scan, I have an L2-L3 disc bulge, and I have been asked to use the lumbar support belt for daily functions to keep my back straight. I tend to walk slow now, as if I try to walk too fast or get up from the bed too quickly, and I start having sharp pains in the front portion of my right thigh. Also, I cannot bend to pick up things, as it hurts my lower back.
Can you let me know what other diagnosis or treatment I should be taking to get myself better and heal this?
I also want to know whether this ever heals completely. Will I be able to go to the gym and lift weights again as
I did earlier? Or, in the end, is surgery the only solution to this?
Any advice would be appreciated.
I appreciate any help you can provide.
Swati Misra
Pain in the front of the thigh fits an L2-L3 disc bulge, because the nerves at that level serve the front of the thigh and the knee, so your scan and your symptoms point the same way. An examination should still check your knee reflex, the strength of the muscle at the front of the thigh and the feeling over the thigh and inner knee, and look at the hip, which can cause similar pain.
Surgery is not the only option. It is the last one, considered when conservative care has had a fair trial and is not working, or in severe cases. Conservative care for a disc bulge avoids twisting and cracking, uses gentle methods within what you can comfortably tolerate, and adds exercise only when your body is ready, usually from about the fifth to seventh session. Until then, avoid bending, twisting and lifting; if lifting cannot be avoided, keep the load under 2 kg. While the pain is acute, stand up and walk briefly every 15 minutes.
The gym is put aside at first, and free weights are avoided for two to six months. Once your back is stable, some machines can be used, such as leg curls and extensions, light rowing and lat pulldowns, while free weights, deadlifts and leg presses stay out. How completely a disc heals differs from person to person, and a problem that was neglected can leave lasting symptoms or flare-ups, which is why the daily habits matter as much as the care. New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours.
Since childhood, I have often fallen or easily slipped. Initially, I only received traditional massages. As an adult, at age 25, I started experiencing recurrent issues due to a fall at age 18 in the bathroom, which led to significant pain when sitting, lying down, or walking. Initially, I underwent regular therapy. The issue recurred when I sat for long periods while teaching. Every two days, I would have pain from the middle of my waist downwards.
At age 27, I was taken to an orthopedic clinic at a hospital. The diagnosis was low back lumbar pain. The diagnosis during crack therapy was pain in the T1_T3 and L1-L5 areas. I only had one session of physiotherapy and did not continue. Five months later, the condition worsened to the point where I could not work. Even shifting positions while lying down was painful. I then had to take pain medication again and underwent physiotherapy with a medical device that felt like electric shocks. It has been almost six months now without a recurrence.
What is your opinion? Is my diagnosis correct? I have never had an MRI or X-ray because the orthopedic doctor said it wouldn’t show anything. Can this condition be cured, or could it cause paralysis or difficulty in becoming pregnant due to it affecting the lumbar area which supports the upper and lower body? What solutions would you recommend?
A diagnosis of low back pain describes where it hurts, not why, so it is fair to ask for more. Falling and slipping easily since childhood, with problems that keep coming back, is worth looking into: some people have very flexible joints that depend on their muscles for support, and a doctor can also check for a nerve cause of the falls. When a disc or joint problem is suspected, imaging helps confirm it instead of guessing a final diagnosis, so ask whether an X-ray or MRI is now needed.
Paralysis comes from severe pressure on the spinal cord or nerves, and it shows itself through weakness, numbness, changes in walking, or changes in bladder or bowel control, which are the signs to watch for. Your doctor can answer the pregnancy question with your full history, so tell them about your back as well. Care for a recurring problem like yours should build strength and control rather than only loosening the joints, with exercise added when your body is ready.
Daily habits matter as much as treatment: stand up and walk briefly every 15 minutes while the pain is acute, sit with your hips back against the chair, and sleep at least six hours. New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours.
I have had strong leg pain in my thighs off and on for many years now. A surgery on my L4-L5 disc fixed a great deal of pain deep in the center of my right thigh. For the last few weeks, the pain in my outer thighs has been unbearable. Can’t get out of bed. Can’t think or focus. So much of my energy is used on dealing with the pain. I see the doctor in a few days. What can I expect in terms of diagnosis and treatment?
The change in where the pain sits is the first thing to tell your doctor. Your surgery eased pain deep in the center of the right thigh, and the pain now runs along the outer thighs, so it needs a fresh look rather than being taken as the old problem.
Expect questions about what eases or worsens the pain, a check of the strength, reflexes and feeling in both legs, and an examination of the hips. The levels above the operated one, such as L2-L3 and L3-L4, are worth checking, and so is the nerve that supplies the skin of the outer thigh, which can be pinched near the front of the hip bone, sometimes by a tight belt. A new MRI, compared with your scans from before the surgery, is likely. Write down exactly where the pain runs, what changes it (sitting, standing, walking, lying down) and whether it burns or aches, and tell the doctor plainly that the pain keeps you in bed.
Once the cause is clear, conservative care for a disc problem avoids twisting and cracking, stays within what you can comfortably tolerate, and adds exercise only when your body is ready. New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours.
I got a slipped at L4-L5. It started about one month ago, now going through treatment at a chiropractic clinic in KK, Sabah. Do you know any clinics that offer NSD Therapy in KK? Please advise. Thank you.
CSC's centers are all in Kuala Lumpur and Selangor, so we cannot point you to a clinic in Kota Kinabalu that offers NSD Therapy. What matters most is that your current care suits a damaged disc. With a slipped disc at L4-L5, twisting and cracking manipulation should be avoided, and gentle methods without twisting are used instead, such as non-rotatory chiropractic manipulation with the Activator instrument, or flexion-distraction. Stretching and exercise start only when your body is ready, not in the first stage.
Ask your practitioner which tests were done at the first visit, how progress is measured against them, and what happens if there is no clear improvement by about the fifth session. At home, avoid bending, twisting and lifting, sit with your hips back against the chair, and stand up for a short walk every 15 minutes while the pain is acute.
New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours.
I have no constant pain but difficulty walking without support, unable to wear my clothes, unable to comb difficulty getting up from a sitting position. Do you think your treatment can benefit me?
Weakness without pain deserves a thorough medical assessment first, because a pinched nerve or a pressed spinal cord can cause weakness with little or no pain. Difficulty with both your arms (dressing, combing your hair) and your legs (walking, rising from a chair) at the same time suggests the cause may lie higher than the lower back, for example in the neck, and some medical conditions cause the same pattern.
Please see a doctor soon for a neurological examination, imaging of the neck as well as the lower back, a review of your medicines and blood tests. Write down when each difficulty began and whether it is getting worse. Whether chiropractic care and physiotherapy can help depends on what that assessment finds. If the spinal cord in the neck is involved, the neck is not manipulated, and any care stays gentle and within what you can comfortably tolerate.
Weakness that keeps getting worse should not be ignored. It calls for a careful assessment by a competent provider, and conservative care can continue only while the weakness itself is improving. New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours.