


Disc Bulge: Meaning, Symptoms, Treatment & Can It Be Reversed?
By Yama Zafer, D.C.
A disc bulge on an MRI report does not, by itself, show where neck or back pain comes from. A bulging disc means the disc's outer rings have swollen slightly beyond their normal borders without pressing on the nerves. In the neck it can bring stiffness or arm pain. In the lower back it can bring back ache, buttock pain or a sciatica-like leg ache. Many cause no symptoms.
Most tears and wear-related changes in a disc follow an injury, sudden or repeated, or repeated harmful strain. Long sitting, slouching, bending and twisting at the waist, and lifting in poor positions all add that strain. Care starts with an examination, then combines gentle, non-rotatory chiropractic care with physiotherapy, hands-on soft tissue work and exercise matched to the disc.
Scans show why the examination matters: in 98 adults with no back pain, 52 percent had a disc bulge on MRI (Jensen et al., 1994). A bulge can change but cannot be fully reversed. Yet in my experience, nearly everyone with a true bulge can live a normal life when it is not ignored. The sections below explain report terms, the stages of disc damage, seriousness and the care plan.
This guide, Disc Bulge: Causes, Symptoms and What It Means, is published by Chiropractic Specialty Center, Bukit Damansara (KL) main center: WhatsApp+60 17 269 1873 Call+603 2093 1000
Disc Bulge: Key Takeaways
| Point | What to know |
|---|---|
| Does it explain the pain? | Only if it matches the examination: where the symptoms are felt, how the nerves test and which movements bring them on. |
| Is it serious? | To some degree, always. On my scale of 0 to 10, a true bulge rates 1 or 2, and a disc that reaches the nerves rates 3 to 5. |
| Does it mean surgery? | No. Surgery should be the last option, after the conservative route is exhausted. It is considered when a conservative plan is not working, or in severe cases such as a sequestered disc or an infection. |
| What decides the next step? | The examination, the reports and the scan itself, then whether the retested findings improve by about the fifth visit. |
| What is avoided | Twisting, bending at the waist, deadlifts, swimming laps, yoga and rotational manipulation, while the disc is irritable. |
| Sitting breaks | With back pain, stand up every 15 to 20 minutes. People without back problems should take a break every 30 to 40 minutes. |
| Signs that need a hospital | New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours. |
What a Disc Bulge on an MRI Report Means
A spinal disc has two parts: a gel-like center, the nucleus, and tough outer rings, the annulus, that keep the center in place. In my definition, a disc bulge means the outer rings have swollen beyond their normal borders.
The disc has not pushed the thecal sac, the sac around the spinal nerves, out of place, and it has not pressed on a nerve. Once it does either, it is a prolapse or a herniation. People often call all of these a slipped disc, which is the layman's term for the same thing.
The drawings below show a lumbar disc from above, with the front of the body at the top and the nerves behind the disc.
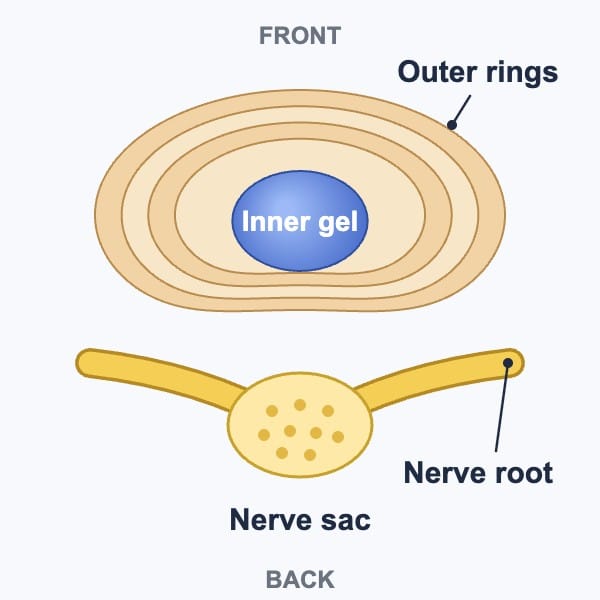
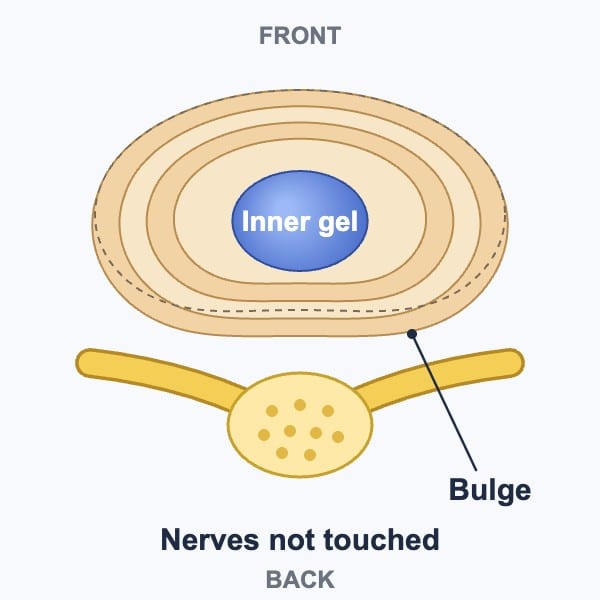
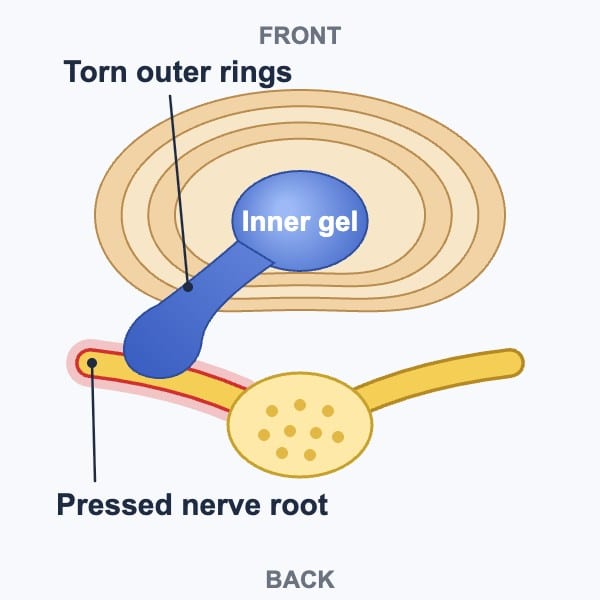
Report words such as diffuse, mild, pseudo, posterior and broad-based describe the disc bulge itself. This is how I explain them to patients:
- Diffuse disc bulge: the disc is bulging in all directions.
- Mild disc bulge: the disc is swollen just a bit and is not displacing the thecal sac, the sac around the spinal nerves, or any other sensitive structure.
- Pseudo disc bulge: a false disc bulge. In essence it is not a disc bulge at all, and it can be a normal variant for that person.
- Non-compressive disc bulge: the bulge is not pressing on the nerves or the sac around them, which by my definition is true of every disc bulge.
- Posterior disc bulge: the bulge points backward, toward the spinal canal and the nerves. Most damaged discs bulge this way, because the ligament behind the disc is thinner than the one in front.
- Broad-based disc bulge: the swelling runs along a wide stretch of the disc's rim, rather than at one point.
- Disc bulge indenting the thecal sac: the disc is pressing into the sac around the nerves. By my definition that is past a true bulge, so it moves up to 3 to 5 on my seriousness scale.
Whatever the word, every disc bulge is approached individually. Before I give advice, I weigh the examination findings, what the person describes, what the tests measure and the reports. Only then do I give a final decision or comment.
A report often lists bulges at several levels. That is common in long-standing neck and back problems, and I weigh each level against the examination on its own.
A disc is one source of neck and back pain among several. According to the statistics I have read, disc bulges and disc herniations are the problem in 40 percent of people with chronic neck or back pain, joint problems in 45 percent, and muscular or other forms of disc problems in the remaining 15 percent.
A bulge on a scan is also common in people without pain. In a 1994 study, 98 adults with no back pain had an MRI of the lower back, read by two specialists who did not know who had pain. Of these adults, 36 percent had normal discs at every level and 52 percent had a bulge at one level or more. A protrusion showed in 27 percent and an extrusion in 1 percent.
The authors concluded that a bulge or protrusion found on an MRI in a person with low back pain "may frequently be coincidental" (Jensen et al., 1994). That is why the scan is read together with the examination.
Common is not the same as healthy. My Back Pain to Leg Pain talk describes a healthy disc as a sponge and a spring. Under load its outer rings widen a little, then spring back once the load comes off. Because an MRI is taken lying down, without that load, a bulge that still shows tells me the rings have lost some spring.
Arranging a Disc Bulge Assessment in KL
The first visit matches a disc bulge on a scan to the person. It checks how the spine moves, the nerves to the arms or legs, strength, sensation and reflexes. It also reviews the reports together with the scan itself, so the CD or film is worth bringing along with the report. Either Kuala Lumpur center can arrange it:
- Bukit Damansara (KL, main center): Call +603 2093 1000 or WhatsApp +60 17 269 1873 to see the Bukit Damansara / KL center.
- Bandar Sri Damansara (KL): Call +603 6262 5777 or WhatsApp +60 12 455 6939 to see the Bandar Sri Damansara center.
Opening hours and directions for both centers are on the CSC locations page.
Bulging Disc Symptoms in the Neck and Lower Back
Many disc bulges cause no symptoms at all. As I often say, the most common symptom of spinal disc damage is zero. When a bulge does cause symptoms, they depend on its level, and they often change with posture and movement.
A true bulge can ache without touching a nerve root. The back of a disc's outer rings, and the thin ligament just behind it, carry pain-sensing fibers from a small nerve called the sinuvertebral nerve. When the rings swell against that ligament, those fibers can register neck or back pain. In my view they act as the spine's alarm, and pain that starts this way is called discogenic pain.
Symptoms From the Neck (Cervical Spine)
A disc bulge in the neck can bring:
- neck stiffness or pain, with less movement;
- pain that travels into the arm or hand;
- tingling or numbness in the arm, hand or fingers;
- weakness in the arm or grip.
As I explain in my video Bulging Disc vs Herniated Disc, when the problem is in the neck, pain can radiate down the arm. The guides to C5-C6 and C6-C7 explain two neck levels where disc problems are found, and the neck pain guide covers the other causes of neck pain.
A true bulge in the neck mostly keeps its symptoms to the neck, the tops of the shoulders and the upper back. When numbness, tingling or burning reach the arm or hand, I look for a bulge in transition or a later stage. A bulge in transition presses further out once the body is upright.
Symptoms From the Lower Back (Lumbar Spine)
In the lower back, disc problems are most often found at L4-L5 and L5-S1. Most forward bending happens at L4-L5, which is why these two levels carry so much of the load. The upper levels, L1-L2, L2-L3 and L3-L4, have their own guides.
A lumbar disc bulge can bring:
- lower back stiffness or ache;
- muscle cramp-like sensations in the low back or the buttocks;
- a sciatica-like ache down one leg, and sometimes both;
- numbness or tingling in the leg or foot;
- weakness in the leg;
- pain made worse by long sitting;
- trouble walking long distances.
To me, sciatica is not a diagnosis. It describes a symptom: an inflamed sciatic nerve.
A disc bulge also often occurs together with facet hypertrophy or ligamentum flavum hypertrophy. In my experience these conditions often co-present, occurring at the same time. A slipped vertebra, spondylolisthesis, is often linked to the same disc and joint changes.
Can a Bulging Disc Cause Numbness or Tingling?
It can, but then it is no longer a typical bulge. I am firm that a true disc bulge, as an MRI shows it, does not press on nerves. The explanation lies in how the scan is taken.
An MRI is done lying down, with no body weight on the spine. After a night's rest, the disc has drawn in fluid and swelled (imbibition). Lying flat, its outer fibers may not push out far enough to reach the nerves, so the report says bulge.
Upright, the weight of the upper body comes down on that disc: after hours hunched over a computer, a long drive or a busy day. The fibers can then push further out and press on a nerve, bringing pain, numbness or tingling down an arm or a leg.
I call this a disc bulge in transition. It looks like a bulge lying down, but under the body's weight it behaves as a prolapse, a protrusion, a herniation or even a focal extrusion. The guide to a pinched nerve explains how nerve symptoms are assessed.
A bulge in transition is one of two things I look for when sitting or driving brings on symptoms the report does not explain. The other is a facet joint problem, in one of the small paired joints at the back of the spine. Bone spurs, a slipped vertebra or a thickened ligamentum flavum, the elastic band behind the nerves, can add to either. Each takes up room the nerve needs, so the bulge itself may touch nothing while the space around the nerve is already crowded.
When Weakness or New Numbness Needs Attention
Arm or leg weakness that keeps getting worse should not be ignored. It calls for a careful assessment by a competent provider, and conservative care can continue only while the weakness itself is improving.
With a lumbar disc bulge, any new symptoms are considered alongside the back or leg pain. New or worsening numbness around the genitals, between the genitals and anus, or around the anus needs urgent medical attention: a thorough assessment at a hospital emergency department straight away, within hours.
New difficulty passing urine needs the same urgent assessment, even if bladder and bowel control remain intact, and so does any loss of that control. Several conditions can cause these symptoms. Some may call for an invasive procedure, but being assessed helps identify the cause and does not automatically lead to surgery.
What Causes a Bulging Disc?
In my experience, it comes back to poor habits. As the day goes on, body weight bears down on the discs, and once degeneration occurs, the fibers tear. Most disc damage begins with an injury, sudden or repeated, or with strain repeated day after day, such as:
- long sitting: when you sit upright, the weight of the body comes down, crushing on the spinal joints and discs, and leaning forward adds to it;
- slouching over a desk or a laptop;
- bending and twisting at the waist, above all together;
- lifting in poor positions, and free weights and deadlifts at the gym;
- standing for long periods;
- an injury, sudden or repeated.
Posture works slowly. Poor posture affects the muscles first, then the ligaments. If it goes on long enough, it damages the joints and eventually reaches deep into the disc.
Age is one factor, but not the only one. I have seen a dried-out disc (disc desiccation) in a girl as young as seven, and healthy discs in people in their 80s. Genetics, daily living, lifestyle, previous injury and posture all play a part.
I also look for what loads one disc more than the next. A sideways curve of the spine, called scoliosis, can do it, and so can one leg shorter than the other. A weak core, trouble in the feet, ankles, knees or hips, extra weight or a spine shaped differently from birth can also tip the load.
For a child or teenager whose scan report mentions a disc bulge, see the guide to chiropractic care for children. It explains how assessment and imaging decisions are made for a growing spine.
Disc Bulge Stages: How Damage Progresses
A disc bulge is a progression of a degenerated or damaged disc. A herniation is a progression of a disc bulge, and an extrusion is a progression of a herniation. My video Why Spinal Discs Get Damaged, 2 minutes 9 seconds long, shows the stages in order. This is how I define each stage of what people call a slipped disc:
- Degenerated or damaged disc: the outer fibers tear and weaken, so they can no longer hold the center of the disc in place.
- Disc bulge: the disc's fibers have swollen more than usual, while the center stays in place. A true bulge does not press on the spinal cord or the nerves. It is a milder form of a contained slipped disc.
- Protrusion: the center of the disc moves outward, toward the spinal canal or the foramina, the openings where the nerves leave the spine, but it does not break through the outer fibers. It is a progression of the bulge and is still contained.
- Prolapse: a progression of the protrusion that is barely contained. A few remaining outer fibers keep the center, the nucleus pulposus, from rupturing into the spinal canal. Some reports use protrusion and prolapse for the same thing.
- Herniation, also called a rupture: the last intact fibers tear, and the center breaks through the outer wall, the annulus fibrosus. It is no longer contained, and it comes in contact with the contents of the spinal canal or the foramina.
- Extrusion: a progression of the herniation, where the center is pushed out from the middle of the disc to its edge. These are large herniations that need prompt attention. That does not automatically mean surgery; it can also mean conservative care, such as the care described below.
- Fragmentation and sequestration: the last and most dangerous stages. Fragmentation can be partial, where part of the center breaks off, or full, where the whole fragment chips off. A full fragmentation, also called a sequestration, leaves that fragment floating free in the spinal canal, and to me it is a severe case, where surgery may be needed sooner. A partial fragmentation may still respond to conservative care. That calls for a thorough assessment that finds none of the urgent signs listed above, then focused, efficient care given precisely by an experienced clinician.
Not every disc moves at the same pace. Once a disc is damaged, the change can come quickly or take years. The signs that need a hospital emergency department straight away are listed under the symptoms above. An MRI can also show changes in the bone beside a damaged disc, called Modic type I or II changes.
Video: Bulging Disc vs Herniation, the Difference
In this video, 3 minutes 12 seconds long, I explain how a disc is built, why its fibers tear and why a disc bulge comes before a herniation. Key moments:
- 0:00 Common questions on disc bulges, herniations and slipped discs
- 0:21 How often discs, joints and muscles are the problem in chronic pain
- 0:35 What a spinal disc does
- 0:46 The nucleus and the annulus
- 1:01 A healthy disc beside a degenerated disc
- 1:28 Annular tears, and why a tear at the back matters more
- 1:45 Bulge or herniation: which comes first
- 2:09 The stages people call a slipped disc
- 2:43 Symptoms in the back, buttock, leg and arm
The edited transcript is on the Bulging Disc vs Herniated Disc: Video Guide page.
Can a Disc Bulge Be Reversed or Cured?
A disc bulge can change, but it cannot be fully reversed. I have never seen a bulge retract 100 percent, and surgery does not return a disc to its original state either.
A permanent cure is not possible for anyone. No matter what I or the best surgeons in the world do, we cannot cure something permanently. There will always be some level of damage.
What happens over the years depends, in my experience, on what the person keeps doing. That means staying mindful of daily habits and keeping up the maintenance care, exercises and stretches given at the end of the active care plan.
My rule for a bulge works both ways at once: add what the disc needs and take away what wears it down. Adding means the home exercises and enough sleep, the time when the disc draws in fluid. Taking away means shorter spells of sitting and driving, the loads that push a bulge outward, and no twisting or bending at the waist. Care itself rests on an accurate diagnosis, a sound plan and careful delivery, with posture and habits changing alongside.
At CSC, the active care plan ends when a person reaches what I call MMI, maximum medical improvement. That is the point where two to three more weeks of care bring no further change in the retested findings. Care then becomes as-needed, with preventive care, daily-living advice and the home exercises.
Is a Disc Bulge Serious?
Every disc bulge is serious to some degree, because the disc has moved beyond its normal borders. How serious depends on the tissues it affects.
I rate seriousness on a scale of 0 to 10: 0 is not serious at all, 1 is the mildest, and 10 is life-altering and critical. A true disc bulge, where the disc has swollen only slightly beyond its normal borders, rates 1 or 2 on my scale.
The rating rises to between 3 and 5 when the disc reaches the nerves. That means it has done one of these:
- pushed the sac around the spinal nerves (the thecal sac) out of place;
- pressed on a nerve;
- filled part of the opening where a nerve leaves the spine (the neural foramen);
- touched the nerve root that runs down past the disc.
By my definition, a disc that presses on the sac or these nerves is no longer a bulge: it is a prolapse or a herniation.
The word bulge is also used loosely. I have seen significant herniations described as a bulge, even in some scan reports, so the word alone does not settle how serious a finding is.
Each case is different. What the scan shows about the sac and the nerves, weighed with the examination, decides it.
Can I Live Normally With a Disc Bulge?
In nearly all cases, yes, as long as the bulge is not ignored, even when its symptoms are mild. Some people have a disc bulge and no symptoms at all.
By a disc bulge, I mean one in its official sense. A disc that presses on the spinal cord or the nerves is labeled a bulge by mistake.
A disc bulge in transition is different. It is quite a serious condition then. Life cannot go on as normal until long sitting or driving no longer brings on symptoms, and that has to be kept up for life.
It rests on following the advice given, keeping up the preventive and wellness plan and the exercises, and making the daily changes the plan sets. With all of that in place, the aim is a normal, healthy, active life.
Disc Bulge Treatment Without Surgery: How Care Is Planned
Every case begins with a thorough assessment. Based on those findings, we discuss a structured care plan that may involve gentle chiropractic with physiotherapy, movement exercises and rehabilitation. The plan is matched to the tissues involved and to the stage of the disc.
Chiropractic and Physiotherapy Together
I recommend the two together. Don't choose between one or the other: choose both. For a damaged disc, chiropractic care is done without twisting the spine. That means chiropractic manipulation that is non-rotatory using the Activator instrument, and flexion-distraction.
Even with the slightest bulge, I am never aggressive. I always start with gentle, non-rotatory methods that target the disc, by hand or with a machine, from our chiropractors or physiotherapists.
Physiotherapy and hands-on care at CSC can include:
- spinal decompression on a decompression table;
- therapeutic ultrasound and electrotherapy;
- shockwave therapy;
- high-intensity laser therapy;
- cryotherapy with the QMD cryothermal device, whose heat setting is kept off a spine with any disc problem;
- trigger point and myofascial therapy;
- stretching, strengthening and balance work once the disc is ready, through exercise rehabilitation and Spinercise® rehabilitation.
Care is kept within what you can comfortably tolerate. Discomfort during care means it is being done too aggressively, so tell the clinician at once. My motto has always been: "No pain, more gain."
What to Avoid While the Disc Is Irritable
While a disc is irritable, bending and twisting at the waist are avoided. So are rotational or aggressive physiotherapy, manual therapy and manipulation, because twisting can aggravate a disc problem. Stretching and exercise wait until the disc has settled, apart from Kegel exercises, buttock squeezes and side-lying leg raises, which can start early.
I am not a big fan of rotary chiropractic manipulation, and I only do it when I am 100 percent sure there is no spinal disc damage. Conservative care does not mean cracking the neck and back, a Thai massage, or letting a child walk on the back. It has to be condition-based and appropriate, care that does no harm.
Other things to avoid:
- deadlifts and free weights;
- swimming laps, since walking in water is gentler;
- hard hamstring stretches;
- hot packs on the neck or back, since heat can add to the inflammation around a damaged disc;
- yoga. Yoga must be avoided with a disc bulge, whether in the neck or the lower back, because its deep forward folds and twists strain the same weakened fibers.
When Exercise Starts
Exercise waits until the disc is stable and the person is ready, usually from the fifth to the seventh session, and for some from the third. Exercise and stretching have to be condition-specific and age-appropriate, and done too early, they create more problems. The first exercises are gentle:
- Kegel exercises for the pelvic floor, which in my view everyone with a lower back problem needs;
- wall-assisted squats;
- cat and camel;
- strengthening of the glutes, hamstrings, calves and thighs, matched to severity;
- core canister breathing exercises.
Kegel exercises need not wait: my Neck and Back Self-Help Tips video tells patients they can start them right away. Buttock squeezes and side-lying leg raises are allowed early as well. A sprained ankle shows why other exercise and stretching wait. A sprain stretches or tears a ligament, and no one would work it hard at the gym or stretch it to chase the pain away. The outer ring of a disc is a ligament too, so its torn fibers get the same time to settle.
Walking, swimming and the gym are covered in the questions below.
Daily Habits: Sitting, Lifting, Travel and Ice
There are 24 hours in a day. I may see a patient for 30 minutes or two hours, so what happens in the other 22 hours matters: posture and habits have to be minded.
- Sitting: with back pain, stand up every 15 to 20 minutes and walk, or stand and move, for 30 seconds to a minute. People without back problems should take a break every 30 to 40 minutes.
- Lifting: none while the disc is irritable; if it cannot be avoided, keep it under 2 kg.
- Travel: avoid long road trips, or travel as the front-seat passenger with the seat reclined. During a phase of acute, intense back pain, a drive lasts roughly 15 minutes, with a safe stop by 20 to 30 minutes at the latest. Once the pain is no longer acute, stop every 45 to 60 minutes, get out and walk; a gentle calf stretch can be added at that stage.
- Ice: 2 to 3 times a day, at least 2 hours apart, for 10 to 15 minutes, with the ice pack wrapped in cloth and a timer set.
- The 72-hour rule: avoid any activity that hurts now or raises the pain within 72 hours afterward, since inflammation can take that long to show.
- Sleep: no less than six hours a night, ideally seven to eight without waking, in the positions set out in the questions below.
How Progress Is Checked
The tests from the first visit are repeated, along with pain scores on a 0 to 10 scale and the person's own account. The pace depends on how severe the problem is, other conditions, and how consistently the advice is followed.
If improvements are not present by the fifth session, the chiropractor should reassess. If there is still no improvement by the 10th session, whether to stop or continue is a decision and a discussion to have together. The active care plan ends at maximum medical improvement, as explained above.
Spinal Decompression with RxDecom®
Spinal decompression applies controlled cycles of tension and relaxation to the spine on a decompression table. At CSC it is one part of a plan with chiropractic care, physiotherapy and exercise, rather than care on its own.
For older adults with spinal stenosis or arthritis, sessions are lighter and shorter. The guides to spinal decompression therapy and NSD Therapy® explain how sessions are run.
Traction vs. Spinal Decompression
Traction and spinal decompression are often discussed together, but they differ. Traditional traction applies a steady pull to the spine, while spinal decompression alternates controlled tension with relaxation.
Forceful pulls on the neck, such as towel or strap pulls, are a different matter. I consider them dangerous, because the neck has small joints, discs and the vertebral artery. The guide to forceful neck pulls explains why.
Can Supplements & Vitamins Help Patients with Bulging Discs?
Supplements and vitamins can support general health but do not change the load on a bulging disc. In one trial, 250 adults with long-standing low back pain and wear-related lumbar arthritis took glucosamine, 1,500 mg a day, for six months. Their pain-related disability eased no more than with a placebo, at six and twelve months (Wilkens et al., 2010).
Glucosamine, chondroitin, MSM and hyaluronic acid taken by mouth do not help the disc. Cells in the disc's center make their own building compounds from the water, oxygen, amino acids and sugar that reach them. I explain this in my Back Pain to Leg Pain talk.
I expect little from glucosamine for the facet joints either. In my view, lower back wear starts with the disc, so a joint is only as healthy as its disc. A medical doctor can advise whether a supplement suits a person's health and medicines.
When Surgery Is Considered
Surgery has its place, and I do not say it should never be done. But with a disc bulge or herniation, surgery should be the last option, after the conservative route is exhausted. It is considered when a conservative plan is not working, or in severe cases:
- a sequestered disc;
- numbness in the genitals or the area between the genitals and anus;
- bladder or bowel problems;
- an infection.
As a first choice, I would not recommend steroid injections or surgery.
Vertebral Discs: Structure & Function
Spinal discs sit between the bones of the spine: six in the neck, twelve in the mid-back and five in the lower back, 23 in all. The first two bones under the skull, C1 and C2, have no disc between them. The most important function of a disc is to allow mobility: bending, twisting, all of it depends on the spinal disc.
The outer ring, the annulus, connects one vertebra to the next, and it is the largest ligament between the segments of the spine. Its 15 to 25 rings, fewer in the neck and more in the lower back, crisscross at about a 120-degree angle. In a healthy disc these fibers are connected together and held firmly in position, keeping the gel-like center, the nucleus, in place.
A disc draws in fluid when the pressure inside it is low, as during sleep, which is why you're taller in the mornings than in the evenings.
How a Spinal Disc Gets Its Nutrients
The adult disc has no blood supply of its own. Its cells depend on nutrients diffusing in from blood vessels at the disc's edges. When that supply fails, cells die, the disc makes less of its own material and breaks it down faster, and the disc degenerates (Urban, Smith and Fairbank, 2004).
At Chiropractic Specialty Center, NSD Therapy® combines targeted spinal decompression with registered physiotherapy and active rehabilitation. Its clinical objective is to reduce compressive load on the disc and improve segmental movement. Individual response varies, and progress is measured by symptoms, function and clinical findings rather than by a promised change in disc shape.
Disc Stress & Damage
A healthy disc does not herniate easily. In the research I have read, a healthy disc herniated in the laboratory only under forces larger than any met in daily life, and in most tests the bone of the vertebra gave way before the disc did. Degenerative changes come first.
Sitting with poor posture, and other heavy or improper loads, raise the pressure inside the disc. That pressure keeps nutrients and water from getting in, and it breaks down the disc's sponge-like molecules, called proteoglycans, which hold water inside it.
Elastin, the bond that holds the fibers of the outer ring tightly together, is broken by normal daily activity and needs those nutrients to be replaced; without them the fibers become easy to injure. The weakened fibers can then buckle or tear and let the center bulge, and later herniate, the changes people call a slipped disc. The guide to degenerative disc disease covers how a disc degenerates.
When the outer ring of a disc is damaged, the inner part will get damaged too, and the other way around. Care for a damaged disc aims to reduce the loads that speed up the damage and to keep the spine moving well.
Annular Tears & Bulges in Spinal Discs
A tear in the outer ring is called an annular tear. Where it sits matters. A tear toward the front of the disc, on the side nearer the stomach, is not as significant as a tear at the back, directly in front of the spinal canal or near the openings where the nerves leave the spine (the neural foramina), because that is where the spinal cord and nerves reside.
A tear there can let the disc herniate, and before it herniates, it bulges. A damaged disc usually pushes backward, because the ligament along the back of the vertebrae, the posterior longitudinal ligament, is thinner than the one along the front, to leave room for the spinal cord.
Forceful pulls or twists can damage a disc further. A small degenerated disc can end up with torn fibers, often reported on an MRI as an annular tear, and a mild bulge can become a severe herniation.
In my experience, a torn disc can wake a person who turns over in bed at night, a cough can feel like a knife in the back, and even laughing can hurt, because every movement makes the torn fibers vibrate. Small tears can be missed on an MRI.
In the 1994 study, 14 percent of adults with no back pain had an annular defect, a break in the outer ring (Jensen et al., 1994). So a tear on a report is matched to the examination too.
Video: Back Pain Into the Leg, Slipped Disc or Sciatica?
In this talk of 1 hour 47 minutes, I explain how back pain that travels into the leg relates to a slipped disc and to sciatica. It also covers how discs are damaged and what to change in daily life.
The chapters of this talk, each with a short summary, are on the Back Pain to Leg Pain Video: Disc or Sciatica? page.
The chiropractic price in Kuala Lumpur and physiotherapy fees in Kuala Lumpur pages list the current fees for an examination and for care at both centers. The fee for a plan is explained and agreed before care begins.
Related Disc and Spine Guides
Related guides cover a slipped disc, how spinal discs work, and physiotherapy at CSC.
Disc Stages
- Degenerative Disc Disease: What the Term Describes
- What Is a Prolapsed Disc in the Spine? Symptoms, Causes and Care
- What Is a Disc Protrusion? Meaning, MRI Locations and Care
- Herniated Disc Treatment in Kuala Lumpur: Signs, Causes and Care
- What Is an Extruded Disc? Meaning, Symptoms and Care in KL
- Fragmented Disc: Partial or Sequestered, Symptoms and Treatment
- Slip Disc Explained: Causes, Stages, Symptoms and Care
- Spinal Discs: What They Do and How They Change
Neck and Lower Back Levels
- C5-C6 Disc Changes and Non-Invasive Neck Care
- C6-C7: What Symptoms at This Neck Level Mean
- L1-L2 Disc Problems: Symptoms, MRI Findings and Care
- L2-L3 Disc Bulge & Herniation: Signs, Symptoms and Treatment
- L3-L4 Spine Care in Kuala Lumpur
- L4-L5 Disc Bulge and Herniated Disc: Symptoms, Causes and Care
- L5-S1 Herniated Disc and Disc Bulge: S1 Nerve Signs and Care
- Pinched Nerve in KL: Targeted, Non-Invasive Care
- Sciatica Treatment: What the First Weeks Involve
Care at CSC
- NSD Therapy®: Components, Suitability and the Care Framework
- Spinal Decompression Therapy in Kuala Lumpur
- Flexion-Distraction for the Spine and Discs
- Activator Technique: How the Instrument Is Used
- Physiotherapy Gym in KL: How It Differs From a Gym
- Chiropractor in Kuala Lumpur with Physiotherapy
- Chiropractor in Bandar Sri Damansara with Physiotherapy
Bulging Disc: Frequently Asked Questions
These answers cover the questions people ask most about living with a disc bulge: flare-ups, both legs, walking, swimming and the gym, choosing care, scans and sleep.
Can a Bulging Disc Come Back After Care?
A disc bulge can flare up again. In my experience, each person responds differently. People who neglected the problem for a long time are more likely to be left with some symptoms or to have flare-ups later. That is why the active care plan does not simply stop. It ends at maximum medical improvement and moves to as-needed care, with preventive care, daily-living advice and home exercises. Long sitting, driving, bending and twisting are the usual tests of whether the gains hold. Pain is not a bad thing; ignoring pain is.
Can a Bulging Disc Affect Both Legs?
Yes. Sciatica-like symptoms usually affect one leg, but they can affect both. The pain can turn into numbness and tingling, and then into weakness. Symptoms in both legs are checked without delay, and weakness that keeps getting worse should not be ignored. New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours.
Is Walking Good for a Bulging Disc?
Yes, within limits. With back pain, I advise standing every 15 to 20 minutes and walking for 30 seconds to a minute, rather than sitting all day. On a treadmill, walk at zero incline, because an incline adds load on the lumbar discs. Walking in water is gentler than swimming laps. A walk that brings on symptoms within 72 hours afterward is shortened next time, because inflammation can take that long to show.
When Can Swimming and the Gym Resume?
Not at first. Swimming laps is avoided, and walking in water is gentler. Free weights are avoided for two to six months, and the gym is discouraged early on. Once the disc is stable, I still rule out free weights, deadlifts and leg presses. Machines can then be used: adductor and abductor machines, leg curls and leg extensions, light rowing and lat pulldowns, and chest presses for some people. On the treadmill, the incline stays at zero.
Can Chiropractic Make a Disc Bulge Worse?
The method matters. Twisting methods that mobilize joints, such as Gonstead and Diversified, suit young people without disc damage. They usually turn the trunk or the head before a quick thrust. I explain where they fit in my Is Chiropractic Safe? 13 Questions Answered video.
With a damaged disc, moderate or severe degeneration or a pinched nerve, chiropractic care should be done without twisting the spine. Suitable choices start with chiropractic manipulation that is non-rotatory using the Activator instrument, then the SOT method, flexion-distraction and the Thompson technique. Anything more than that can create inflammation or even worsen the disc damage already there.
Care is kept within what you can comfortably tolerate. Discomfort during care means it is being done too aggressively, so tell the clinician at once.
X-Ray or MRI: Which Scan Shows a Disc Problem?
Not every patient needs imaging, and it is arranged only after a thorough assessment, when it is indicated. When a disc problem is suspected, I prefer an MRI. It is the gold standard, it uses no radiation, and it shows the bone, joint, muscle, ligament and the space the nerves occupy. An X-ray is cheaper but shows only bone. I never guess a final diagnosis. Anyone who already has a scan should bring the images themselves, on CD or film, as well as the report.
Chiropractor or Physiotherapist for a Bulging Disc?
Both. Don't choose between one or the other: choose both. Holistic means comprehensive, and care cannot be comprehensive if it is a single approach. Some care needs an experienced chiropractor, and physiotherapists bring just as many strengths of their own. That is why I set CSC up in 2006 as one center where chiropractors and physiotherapists work in tandem, with exercise and rehabilitation under one roof.
How Should I Sleep With a Bulging Disc?
Posture and sleep are the two things I consider most critical, and of the two, sleep is the important one. I ask for at least six hours. The order of positions: on the right side first, the left side second, and on the back with a bolster under the knees third. On the side, a pillow keeps the spine straight and a bolster sits between the knees. If lying on the right side brings on heartburn, the left side comes first. An afternoon nap does not make up for a short night.
How to Read This Guide
This guide is educational. It explains disc bulges in general and cannot assess a reader's own situation, so an examination is the way to know what a particular disc bulge means. Where it reports a study, it gives what that study found, in whom and with what limits. Where it gives my own clinical position, it says so in the first person.
References
- Jensen MC, Brant-Zawadzki MN, Obuchowski N, Modic MT, Malkasian D, Ross JS. Magnetic resonance imaging of the lumbar spine in people without back pain. N Engl J Med. 1994;331(2):69-73.
- Wilkens P, Scheel IB, Grundnes O, Hellum C, Storheim K. Effect of glucosamine on pain-related disability in patients with chronic low back pain and degenerative lumbar osteoarthritis: a randomized controlled trial. JAMA. 2010;304(1):45-52.
- Urban JP, Smith S, Fairbank JC. Nutrition of the intervertebral disc. Spine (Phila Pa 1976). 2004;29(23):2700-2709.
These references describe disc bulges, disc changes and their care in general. None of them evaluates care at Chiropractic Specialty Center.
The Author of Disc Bulge: Causes, Symptoms and What It Means
Disc Bulge: Causes, Symptoms and What It Means was written by Yama Zafer, D.C., who has 30+ years in chiropractic and physiotherapy and founded Chiropractic Specialty Center in Kuala Lumpur in 2006.
Last Updated: Disc Bulge: Meaning, Symptoms, Treatment & Can It Be Reversed?
Disc Bulge: Meaning, Symptoms, Treatment & Can It Be Reversed? was last reviewed and updated on October 16, 2026.
Share with others: