

Degenerative Disc Disease: Desiccation, Stages and Treatment
Degenerative disc disease often shows first as disc desiccation on an MRI, yet the scan alone does not show where any pain comes from. A degenerated disc can ache with sitting or bending, or send pain into the buttock and leg, or from the neck into the arm. In my experience, the most common symptom of spinal disc damage is zero. A quiet disc can still be a damaged one.
In my view, daily load is the main cause. Sitting, slouching, bending, twisting and lifting raise the pressure inside a disc, pushing out its water and nutrients. The disc dries, its fibers weaken and tear, and the disc can begin to bulge. Age is one factor, never the only one. I have seen a desiccated disc in a seven-year-old girl, and discs still healthy in people past 80.
Care starts with an interview, an examination and, when a disc problem is suspected, an MRI. It combines gentle, non-rotatory chiropractic methods, physiotherapy, hands-on soft tissue work, cold therapy and, when you are ready, precise exercise. Sitting, sleep and lifting habits change too. The sections below cover every stage up to a fragmented disc, mild desiccation, lost height and the warning signs.
For more information about degenerative disc disease, contact the Bukit Damansara (KL) main center: WhatsApp+60 17 269 1873 Call+603 2093 1000
Degenerative Disc Disease: Key Takeaways
| Question | Short answer |
|---|---|
| Is desiccation the same as degenerative disc disease? | Not quite. Desiccation means the disc's center has lost water; degenerative disc disease also covers weakened fibers and lost height. |
| Is mild desiccation serious? | It can be. "Mild" describes how the scan looks, not how much the finding matters; the examination decides that. |
| Can a dry disc take water back? | Partly. Fluid enters a disc when the pressure inside it drops, mostly while lying down. No supplement taken by mouth rebuilds it. |
| What can follow? | If the load goes on, a bulge, a protrusion, a prolapse, a herniation, an extrusion and finally fragmentation. It can take years or happen fast. |
| Does it mean surgery? | In my view surgery is the last option, apart from severe cases: an infection or a fully fragmented (sequestered) disc. New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours. |
| Which levels are most affected? | L4-L5 in the lower back and C5-C6 in the neck, in a Japanese community study of 975 adults (Teraguchi and colleagues, 2014). |
| Does the scan show where the pain comes from? | Not on its own. Your history and examination, read with the MRI images, show whether the disc explains your symptoms and which care suits it. |
What Causes Degenerative Disc Disease and Desiccation?
In my view, load is the main cause: the pressure that sitting, bending and lifting put on a disc, day after day. A healthy disc is far tougher than most people think. In the research I have read, healthy discs loaded in a laboratory did not herniate under any force met in daily life. In most of those tests, the vertebra failed first. Some degeneration has to come first, and that research describes it as a chain:
- Load raises the pressure inside the disc. Sitting loads it more than standing, and leaning forward over a desk more again.
- High pressure locks out nourishment. An adult disc has almost no blood vessels of its own. Oxygen, sugar, amino acids and water reach it through the vertebra only when the pressure inside is low. Under constant load its cells go hungry and stop making proteoglycans.
- The sponge breaks down. Proteoglycans are the disc's sponge-like molecules. Up to 100 of them join along a strand of hyaluronic acid to form a giant aggregate, the disc's main building block. Sustained pressure breaks these aggregates into small pieces that leach away.
- The fibers lose their bonds. Elastin holds the fibers of the outer ring tightly together. Everyday movement breaks some of these bonds, and a starved disc cannot replace them, so the fibers become easy to injure.
- The disc dries. With fewer proteoglycans, its osmotic pressure, the pull that draws water in, falls, and it holds less water under load. This is desiccation.
- The weak disc gives way. Its fibers buckle or tear, and the center can push out through them. As I show in Bulging Disc vs Herniated Disc: Video Guide, a tear at the back matters far more than one at the front. The back of the disc faces the spinal canal and the openings where nerves leave.
This is why I say what damages a disc is our lifestyle and our poor habits. Poor posture strains the muscles first, then the ligaments and then the joints. In time it reaches deep into the disc, as I show in Poor Posture Spine Video: How Posture Affects the Spine. A review of the research lists genetic inheritance, age, poor nutrient supply to the disc and loading history among the causes of degeneration. It found that tears and other structural damage are not inevitable with age. They relate more closely to pain than any other feature of aging discs (Adams and Roughley, 2006).
Weak spots in the end-plates can start the process as well. In my view, Schmorl's nodes, small hollows where disc tissue has pressed into the vertebra, can lead a disc to degenerate. The Schmorl's node guide explains them in more detail.
Disc Assessment at Two KL Centers
For degenerative disc disease or desiccation named on a scan, a first visit at either Kuala Lumpur center starts with an interview. An examination of movement, nerve function and strength follows, and the MRI images are read after that. Bring the images on CD or film, not only the reports, with a note of what you have already tried. Directions and opening hours are on the contact page.
- Bukit Damansara (KL, main center): Call +603 2093 1000 or WhatsApp +60 17 269 1873 to see the Bukit Damansara / KL center.
- Bandar Sri Damansara (KL): Call +603 6262 5777 or WhatsApp +60 12 455 6939 to see the Bandar Sri Damansara center.
Is Desiccation the Same as Degenerative Disc Disease?
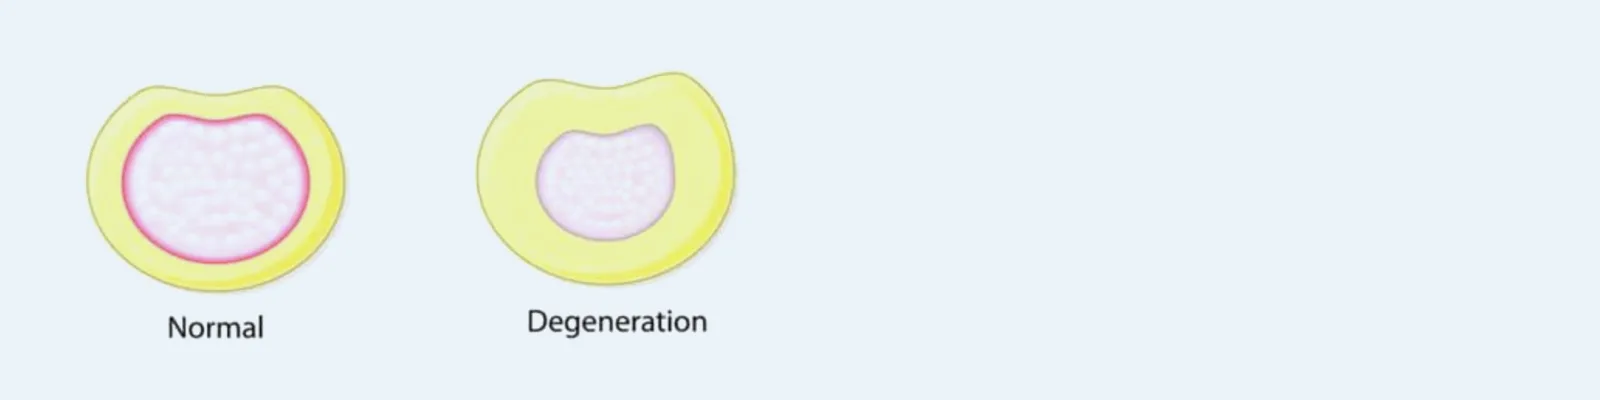
Not quite. Desiccation, also called disc dehydration, is one finding: the center of the disc has lost water. On a T2-weighted MRI, which shows water as bright, it looks dark, and its border with the outer ring fades. Degenerative disc disease is the wider picture of a disc that has dried, weakened and often lost height. One review keeps the name for a degenerated disc that is also painful (Adams and Roughley, 2006).
In my own words, a degenerated disc is malnourished, worn out and dehydrated. Years of load have starved it of the water and nourishment a disc draws in while it rests.
In the research I have read, a disc dries before its fibers give way. A report can therefore name desiccation alone, years before any bulge shows. The bone beside a worn disc can change too, which reports call Modic Type I or Modic Type II changes.
Mild or Moderate Desiccation on a Report
Words such as mild and moderate describe how the scan looks, not how much the finding matters. A mildly narrowed disc can still affect a nerve and bring numbness, weakness, or trouble standing and walking, sometimes with little pain at first. I never judge a disc from the report alone; the examination shows what the finding is doing.
Loss of Disc Height
As a degenerated disc thins, the joints behind it carry more load and can wear and enlarge, a change called facet hypertrophy. The ligamentum flavum, the elastic band at the back of the spinal canal, can buckle into the space the nerves need. The openings where nerves leave the spine narrow too. A thinned disc also tears, bulges and protrudes more easily.
In my view, wear in the spine starts at the disc, and the joints follow. The disc is the spacer between two vertebrae, so once it thins, the surfaces of the facet joints are forced against each other. If the disc is not worn, in my experience its joints and their capsules are not either.
Can a Dry Disc Take Water Back?
Partly. Fluid flows into a disc only while the pressure inside it stays low, above all when you lie down. A disc short of proteoglycans also holds less of it under load. If your work keeps you seated all day, sleep is the disc's main chance to take in water and nutrients.
No compound taken by mouth builds the disc back up, and that includes glucosamine, chondroitin and hyaluronic acid. The disc makes its own: cells at its center build these compounds from the sugar, oxygen, water and amino acids that diffuse in. I explain this in my talk Back Pain to Leg Pain Video: Disc or Sciatica? I expect little from such supplements for the facet joints either, since a joint in the spine is only as healthy as its disc.
Damage that has happened stays to some degree. As I say in the same talk, the most important thing is not the treatment but the lifestyle changes. They decide the load the disc carries from now on.
Stages of Degenerative Disc Disease, From Bulge to Fragmentation
You cannot have a bulging, protruded, prolapsed, herniated or extruded disc without degeneration first. I say so in my talk Back Pain to Leg Pain Video: Disc or Sciatica? Once a disc is damaged, the next stage can come quickly or take years. My short videos on the stages define each one, and the table follows their order:
| Stage | What happens to the disc |
|---|---|
| Degenerated disc | The bonds between the outer fibers weaken and the center dries. This is where desiccation shows. I call it the pre-slip-disc stage: nothing has bulged yet, but every later stage starts here. |
| Bulge | The outer fibers swell beyond their usual size. A true bulge stays contained and leaves the spinal cord and nerves untouched. |
| Protrusion | The center shifts toward the canal or a nerve opening, but the outer fibers still hold it in. |
| Prolapse | Only a few outer fibers are left, holding the center back from the canal. |
| Herniation | The center has broken through the outer fibers. A herniation and a rupture are the same stage. |
| Extrusion | The center has been forced out as far as the rim of the disc. That calls for prompt assessment, which does not automatically mean surgery and can include conservative care. |
| Partial fragmentation | Part of the center breaks off. It may still respond to conservative care, but only after a thorough assessment. That assessment has to find no numbness around the genitals or anus and no bladder or bowel signs. The care must also be highly focused and efficient, and delivered precisely by an experienced clinician. |
| Full fragmentation | The fragment chips off completely and floats free in the spinal canal; this is the sequestered disc. In my view it is the most dangerous stage and a severe case for surgery. |
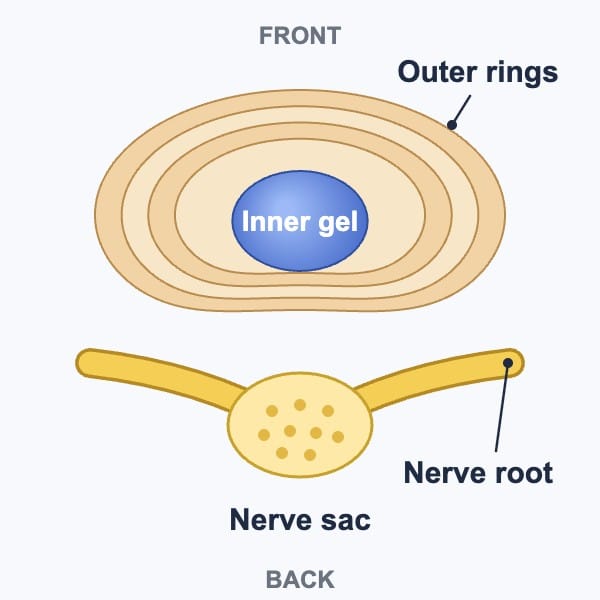
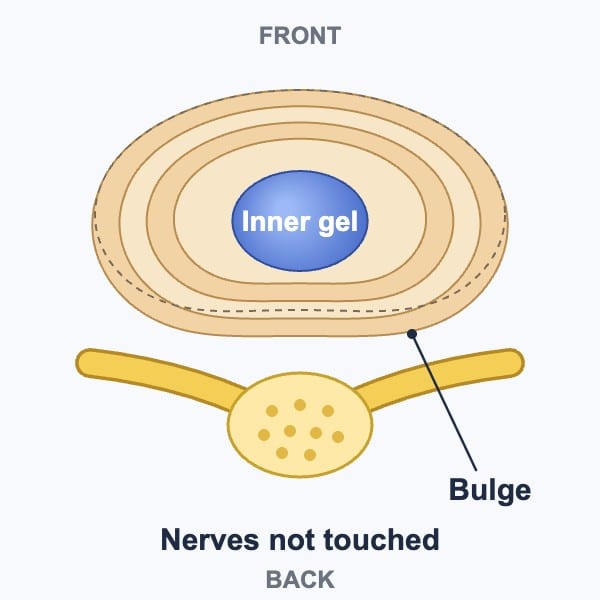
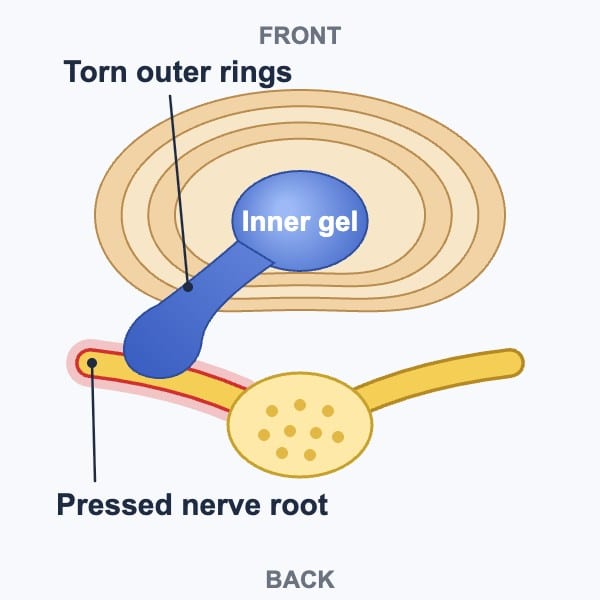
A healthy disc widens slightly under the body's weight, like a balloon pressed from above, and springs back when the load comes off. A dry, worn disc springs back less, because it holds less water and its fibers have weakened. In my view, that is how a bulge begins. The disc bulge guide explains what a bulge that still shows on a lying-down MRI means.
Scan reports often call a later stage a bulge. The border of a degenerated center is hard to see on MRI, so the seven or eight steps cannot always be told apart. That is not a mistake by the radiologist; it is why the examination counts as much as the word on the report. The video below, What Causes a Disc Bulge? Hidden Mechanics Explained, comes from the same channel as my other videos.
Symptoms and Warning Signs of a Damaged Disc
Many damaged discs stay silent for years. When degenerative disc disease does cause symptoms, they follow where the disc sits and what it touches:
- A deep ache in the lower back or neck that builds with sitting, bending or standing still.
- Cramp-like feelings around the lower back or buttock, and in some people pain down the leg like sciatica.
- From a disc in the neck, pain that can travel down the arm.
- With a torn disc, a sharp pain that wakes you as you turn in bed, or a cough like a knife through the back.
- Numbness and tingling, then weakness, when a nerve is pinched, with less and less walking distance.
- Weak legs with little or no back pain, because some damaged discs no longer send pain signals at all.
In the community study described below, low back pain went with degeneration of the lumbar discs (Teraguchi and colleagues, 2014). As I say in my talk Back Pain to Leg Pain Video: Disc or Sciatica? pain is not a bad thing; ignoring pain is bad. Back or neck pain that keeps coming back deserves an assessment.
In my view, the pain of a degenerated disc changes as the damage goes on. Early on, it comes mostly from inflammation inside the disc itself, in the neck as well as in the lower back. In my Back Pain to Leg Pain talk, I place that inflammation among the first events in disc damage. Later, as the disc thins, pain also comes from its neighbors: narrowed nerve openings, a buckled ligamentum flavum and worn facet joints.
With back or leg pain, a new symptom still needs attention even when a scan has already shown disc desiccation or other degenerative disc changes. New or worsening numbness around your genitals, between your genitals and anus, or around your anus needs urgent medical attention: a thorough assessment at a hospital emergency department straight away, within hours. New difficulty passing urine needs the same urgent assessment before bladder or bowel control is lost, and a loss of that control is urgent too. Several causes are possible. Some may call for an invasive procedure, but assessment helps determine the next step and does not automatically mean surgery.
Leg weakness that keeps getting worse should not be ignored. It calls for a careful assessment by a competent provider, and conservative care can continue only while the weakness itself is improving.
Which Levels Are Affected Most? Lumbar, Cervical and Multilevel
In the lower back, L4-L5 is affected most. In my Back Pain to Leg Pain talk I explain that most bending at the waist happens there. That makes it the most common level for a bulge or a herniation. L5-S1 comes second and L3-L4 third. A Japanese community study scanned 975 adults aged 21 to 97. Marked degeneration on MRI was most frequent at L4-L5, at C5-C6 in the neck and at T6-T7 in the mid-back (Teraguchi and colleagues, 2014).
Multilevel degenerative disc disease means the same scan shows degeneration at two or more discs. The pressure of long sitting and repeated lifting falls on every disc below the load, so more than one level can be affected. Each level is still judged on its own, because one can be quiet while the next presses on a nerve.
In my view, tech neck, also called text neck, is the most common cause of degeneration at several neck levels. It means hours with the head bent forward over a phone or a screen.
In the neck, a damaged disc can press on the spinal cord as well as on a nerve root. As I explain in the same talk, symptoms can then reach as far as the legs, with weakness or trouble standing and walking. That needs prompt assessment.
Treatment for Degenerative Disc Disease Without Surgery
Treatment without surgery starts with three steps, in this order:
- A long interview, because muscles, ligaments, the facet joints, the disc and the nerves can all produce the same pain.
- A physical examination: how the spine moves, orthopedic tests, reflexes and sensation, and muscle strength.
- Imaging where it adds something: an MRI whenever a disc problem is suspected, because a final diagnosis should never be a guess.
At CSC, care is then chosen for the tissues involved, by chiropractors and physiotherapists working side by side. As I say in Is Chiropractic Safe? 13 Questions Answered, don't choose between the two; choose both. A plan for a degenerated disc can include:
- Gentle chiropractic methods without twisting, such as flexion-distraction, in which a moving table gently bends and stretches the lower back, and low-force instrument techniques.
- Spinal decompression with the RxDecom® device, a slow, controlled pull on the spine, as one part of the plan. In my view, decompression is only one part of the plan: the tight muscles, weak ligaments and inflamed joints around the disc need care too.
- Physiotherapy methods matched to the tissue: therapeutic ultrasound, electrotherapy, shockwave and high-intensity laser therapy.
- The QMD cryothermal device, used for cold only; its heat setting stays off whenever a disc or facet joint problem is present.
- Trigger point and myofascial work for the muscles around the affected level and the thin sheets of tissue that wrap them.
- Stretching, strengthening, balance and nerve-control exercises, started only when your body is ready, often from the fifth to the seventh session.
- Kegel exercises for the pelvic floor, which need no such wait. With a lower back problem, I ask patients to begin them right away, as in my Neck and Back Self-Help Tips video. Contracting the buttock muscles and side-lying leg raises can begin early too.
At CSC these methods are brought together in one structured program called NSD Therapy®. What is left out matters as much. Even a very experienced chiropractor should never crack or twist a spine that has a damaged disc. I reserve rotary manipulation for a spine I am 100 percent certain has no damaged disc. Aggressive manual therapy, heavy massage on the back and anyone walking on the back are left out too.
Care is kept within what you can comfortably tolerate. Discomfort during care means it is being done too aggressively, so tell the clinician at once, even when it is slight. My motto has always been “No pain, more gain.” Recovery has a better chance when what is beneficial for the disc increases and what is harmful to it decreases. That takes an accurate diagnosis, a proper plan, execution with no flaws or the fewest possible, and changes to posture, habits and daily activity.
Progress is measured by repeating the first visit's tests. If nothing has improved by the fifth session, the plan is reassessed. If there is still no improvement by the tenth, you and your clinician decide together whether to continue.
When Surgery Is Considered
In my view, surgery should be the last option for a damaged disc, once focused conservative care, given properly, has run its course. I say so in Sciatica vs Slipped Disc: Video Explanation. Surgery has its place, and some cases need it sooner, such as an infection or a fully fragmented (sequestered) disc. Outside those cases, I would not choose steroid injections or surgery first. New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours.
What Is the Best Treatment for Disc Desiccation?
No single treatment is best for every desiccated disc. It depends on the examination findings, on whether a nerve is involved and on how long the symptoms have lasted. None of the studies cited here tested a treatment, so these checks come from my clinical experience:
- An examination that finds which tissue is involved, whether muscle, ligament, facet joint, disc or nerve, with the MRI images read against it.
- The findings and the plan explained in plain words.
- Methods that never twist a damaged disc.
- Focused conservative care first, with surgery kept for severe cases such as an infection or a fully fragmented disc.
- Fees stated before care begins.
- Progress measured against the first findings, not only against how you feel.
- Referral to a doctor or a hospital when the signs call for it.
The chiropractic fees and physiotherapy fees pages list the cost of each item. The fee for a plan is explained and agreed before care begins.
Daily Habits and Things to Avoid With a Damaged Disc
A visit fills, at most, two hours of your day. The other 22 hours of sitting, sleeping and lifting decide much of what a degenerated disc carries. These are the rules I give every patient:
- While your back hurts, get up from your seat every 15 to 20 minutes. Walk or move about for 30 seconds to a minute. With no back problem, a break every 30 to 40 minutes is enough.
- If your back pain is acute and intense, keep each drive to about 15 minutes and never beyond 20 to 30 minutes. Stop where it is safe and walk; save any calf stretch for after the acute phase.
- Sleep at least six hours, aiming for seven to eight hours without waking. Lie on your side with the spine in one line and a bolster between the knees, or on your back with support under the knees.
- Avoid lifting. If you must lift, stay under 2 kg, and never lift or carry while bent or twisted.
- Keep bending and twisting at the waist to zero, especially under load.
- For a sore area, use ice two or three times a day. Each session lasts 10 to 15 minutes, with at least two hours between sessions, the pack wrapped in cloth and a timer running.
- Keep hot packs off your back or neck, since their heat adds to the inflammation around a damaged disc.
- Yoga must be avoided with degenerative disc disease, because many of its poses bend and twist the spine deeply.
- Leave out swimming laps, deadlifts, free weights and leg presses.
- Leave out general stretching and side bending, since they can push a damaged disc further. Stretch only as your clinician prescribes, once you are ready.
- Set the screen so your eyes sit just below its top edge, and bring the phone up instead of bending your neck down to it.
- Drop any activity that hurts while you do it, or that makes the pain worse within 72 hours. Inflammation can take that long to appear.
How a Healthy Spinal Disc Stays Strong
A spinal disc has two parts. The nucleus pulposus is the gel-like center. The annulus fibrosus is the ring of fibers around it, which joins one vertebra to the next and keeps the nucleus in place. Because it binds bone to bone, many call the annulus a ligament, the largest between the vertebrae. It is woven from about 15 rings in the neck and about 25 in the lower back.
The disc's most important job is movement: bending and twisting both depend on it. In a healthy disc the fibers are firmly connected and hold the nucleus in the center. Fluid moves in and out as the load changes, a process called imbibition. The discs swell slightly overnight, which is why you are a little taller in the morning.
A disc is fed through the vertebrae above and below it, so the bone matters too. In my Back Pain to Leg Pain talk I explain that you cannot have an osteoporotic (thinned and weakened) bone and a perfectly healthy disc. The short video below, Imbibition Explained: How Spinal Discs Stay Hydrated, covers how a disc takes in fluid.
Share with others:
Common Questions About Damaged Discs
Is disc desiccation normal?
It is common, and I never call it simply a sign of age. In my experience, a degenerated disc is the most common spinal condition at CSC. In my Back Pain to Leg Pain talk I say we all degenerate and regenerate, but some of us degenerate far faster than we regenerate.
Genetics, daily habits, posture and earlier injuries can bring desiccation on much earlier than most people expect. A desiccated disc may give no pain for years, yet it is a weaker disc, more easily injured by sitting, bending and lifting. That is why I see it as a reason to change what the disc carries, not as something to ignore.
Does sitting make degenerative disc disease worse?
Long, unbroken sitting can, because sitting loads a disc more than standing does. In Back Pain to Leg Pain Video: Disc or Sciatica? I give the pressure inside a lumbar disc as about 25 millimeters of mercury lying down, 100 standing and 250 sitting. Leaning forward over a desk takes it to 400 or more. The higher the pressure, the less water and nourishment the disc can draw in, so long sitting keeps a degenerated disc drier and weaker. Choose a chair that supports the lower back, with the knees level with the hips or just below them and the feet under the knees.
Is walking good for degenerative disc disease?
Yes, within comfort. In Sciatica vs Slipped Disc: Video Explanation I explain that walking moves every joint and takes pressure off them, and that mobility is good. On a treadmill, keep the incline at zero, since a slope adds load to the lower back discs. Walking in water is gentler again, and I prefer it to swimming laps. Shorten or stop a walk that brings on leg pain, numbness or tingling. Mention it at your next visit, since those symptoms can mean a nerve is involved.
Can degenerative disc disease be reversed?
Not completely. A damaged disc can change, but neither care nor surgery returns it to its original state, and some damage always remains. What shapes the years ahead is what you keep doing. That means mindful daily habits, maintenance care, and the exercises and stretches given at the end of an active care plan. At CSC the active plan ends at maximum medical improvement, when another two or three weeks of care no longer change the retested findings.
Can a damaged disc cause leg weakness without back pain?
Yes. As I explain in my Back Pain to Leg Pain talk, some damaged discs stop sending pain signals. The pain-sensing fibers in their outer layers no longer work. Yet the disc can still press on a nerve root. A narrowed disc can do the same by crowding the openings where nerves leave the spine. The result can be weak legs or numbness with little or no back pain, which is easy to put down to tiredness. Leg weakness that keeps getting worse should not be ignored. It calls for a careful assessment by a competent provider, and conservative care can continue only while the weakness itself is improving.
Can young people have damaged spinal discs?
Yes. I have seen damaged discs in children as young as seven. Genetics, earlier injuries, posture and long hours of sitting all play a part, even in a young spine. In my Back Pain to Leg Pain talk I also warn about tech neck: hours spent looking down at a phone. A child or teenager whose back or neck pain keeps returning deserves the same careful assessment as an adult.
When is a disc problem urgent?
New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours. Most other disc symptoms call for an assessment, not an emergency. Worsening leg weakness needs prompt assessment too. Pain that keeps returning, spreads into a leg or an arm, or wakes you at night should be checked by a competent provider. Bring the scan images along.
How to Read This Guide
My own positions are written in the first person, and where a view comes from one of my videos or talks, the video is named. Studies appear by first author and year, and the list below links each one to its free PubMed record. A study describes groups of people, not what one disc will do. This guide explains degenerative disc disease in general; only an examination can judge your own disc.
Peer-Reviewed References
- Adams MA, Roughley PJ. What is intervertebral disc degeneration, and what causes it? Spine (Phila Pa 1976). 2006;31(18):2151-2161.
- Teraguchi M, Yoshimura N, Hashizume H, et al. Prevalence and distribution of intervertebral disc degeneration over the entire spine in a population-based cohort: the Wakayama Spine Study. Osteoarthritis Cartilage. 2014;22(1):104-110.
Each of these studies looks at disc degeneration in general, not at the care given at Chiropractic Specialty Center.
The Author of Degenerative Disc Disease: Desiccation, Causes & Care
Degenerative Disc Disease: Desiccation, Causes & Care was written by Yama Zafer, D.C., who has 30+ years in chiropractic and physiotherapy and founded Chiropractic Specialty Center in Kuala Lumpur in 2006.
Last Updated: Degenerative Disc Disease: Desiccation, Stages and Treatment
Degenerative Disc Disease: Desiccation, Stages and Treatment was last reviewed and updated on October 16, 2026.