

L3-L4 Spine Care in Kuala Lumpur
L3-L4 is the third and fourth lumbar vertebrae and the disc between them, in the middle of the lower back. The L3 nerve root exits at this level and the L4 root passes just behind the disc, so symptoms here are usually felt in the front of the thigh, around the knee and sometimes along the inner shin rather than in the calf or foot, and weakness shows as difficulty straightening the knee or climbing stairs.
Position often carries more information than the report. Where leaning forward eases symptoms and standing upright worsens them, narrowing at the back of the spine is likely involved; where sitting is the harder position, the disc is the more likely source.
Many L3-L4 problems settle with conservative care, and surgery is kept for cases where that care has not produced results or the problem is severe. At Chiropractic Specialty Center, care starts with a detailed interview and examination, and an X-ray or MRI is added only when the result will change the plan. Chiropractors and physiotherapists then work together with gentle, non-rotatory methods, such as spinal decompression and flexion-distraction, aimed at taking load off the disc and the irritated nerve, and exercise is added once the back has settled.
This guide to the L3-L4 segment, its nerves, MRI terms and conservative care, is published by Chiropractic Specialty Center, Bukit Damansara (KL) main center: WhatsApp+60 17 269 1873 Call+603 2093 1000
L3-L4: Key Takeaways
| Point | What to know |
|---|---|
| Where it is | The third and fourth lumbar vertebrae and the disc between them, in the middle of the lower back. |
| Nerves | The L3 root exits at this level and the L4 root passes behind the disc; both help form the femoral nerve to the front of the thigh and the knee (Refai et al., 2023). |
| Typical symptoms | Lower back pain or stiffness, with pain, tingling or numbness in the front of the thigh, the inner side of the knee or the inner shin. |
| Position clue | Narrowing tends to hurt more with standing or arching back; a disc that is the main source tends to hurt more with long sitting. |
| How common | Among adults aged 25 to 55, more than 95% of lumbar disc herniations occur at L4-L5 or L5-S1, so L3-L4 is a less common level (Pojskic et al., 2024). |
| Assessment | A detailed interview and examination come first; an X-ray or an MRI, rarely both, is added when the result will change the plan. |
| Care at CSC | Gentle, non-rotatory chiropractic and physiotherapy with spinal decompression, no bending or twisting, and exercise once the back is stable, usually from the 5th to 7th session. |
L3-L4: Page Guide & Key Sections
- Where Is L3-L4 on the Spine?
- L3-L4 Nerves and Symptoms: Thigh, Knee and Lower Back
- Arranging an L3-L4 Assessment in KL
- How an L3-L4 Problem Is Assessed at CSC
- L3-L4 Disc Bulge, Protrusion and Herniation: What the Terms Mean
- Other L3-L4 Findings on MRI and X-Ray
- Why L3-L4 Wears: Load, Posture and Injury
- How L3-L4 Problems Are Cared For at CSC
- Daily Habits That Take Load Off L3-L4
- Older and Younger Adults: How the Plan Differs
- How Progress Is Measured and When Surgery Is Considered
- Related Lumbar Level and Disc Guides
- Frequently Asked Questions About L3-L4 Disc, Joint, and Nerve Care
- References
Where Is L3-L4 on the Spine?
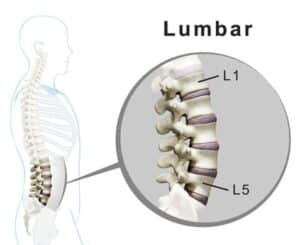
The lumbar spine has five vertebrae, numbered L1 to L5 from the top down, and L3-L4 is the segment between the third and the fourth. It sits in the middle of the lower back. The tops of the hip bones give a rough guide to its level: in a study of 75 adults, a line felt by hand across the tops of the hip bones pointed to L3 or the L3-L4 space in 77% of cases, while the same line drawn on imaging crossed L4 or the L4-L5 space in 87% (Chakraverty et al., 2007).
Between the two vertebrae sits the L3-L4 disc, a cushion that shares load as the spine bends forward and straightens. Behind it, two small facet joints act as hinges that guide movement and limit twisting. Ligaments, including the elastic ligamentum flavum, and the deep back muscles, the multifidus and erector spinae, hold the segment steady.
Two nerve corridors run through the segment. The foramen is an opening at the side where the L3 nerve root leaves the spine. The lateral recess is a short channel beside the back of the disc where the L4 root passes on its way to exit one level lower. When the disc loses height, the facet joints enlarge or the ligamentum flavum thickens, these corridors and the central canal can narrow.
L3-L4 also shares the work of the lower back with the levels around it. Stiffness at L1-L2 or L2-L3 can make it work harder, and when L3-L4 itself stiffens, L4-L5 and L5-S1 below can take up the extra movement. Over time, this sharing of load can lead to disc and facet changes at more than one level on an MRI.
L3-L4 Nerves and Symptoms: Thigh, Knee and Lower Back
Two nerve roots pass through L3-L4. The L3 root leaves through the foramen at this level, and the L4 root runs just behind the disc before leaving one level lower. Both help form the femoral nerve, which works the hip flexors and the muscles that straighten the knee, and carries feeling from the front and inner thigh and the inner side of the lower leg (Refai et al., 2023).
Which Nerve Root Is Affected: Exiting L3 or Traversing L4
The direction of a disc change decides which root it reaches. A change toward the back and slightly to one side narrows the lateral recess and tends to press on the traversing L4 root. A change out to the side, into or beyond the foramen, is called a foraminal or far-lateral herniation, and it tends to press on the exiting L3 root instead.
Where the symptoms are felt is often a useful clue. In a study of 58 people with herniations out to the side at L2-L3, L3-L4 or L4-L5, 80% of those with an L3-L4 herniation felt pain or numbness on the inner side of the knee. The authors found that this pattern strongly suggested the L3 root, and that strength and reflex tests alone could not reliably identify the level (Kido et al., 2016).
Common L3-L4 Symptoms
L3-L4 problems vary from person to person. Common signs include:
- Lower back pain or stiffness, often worse after standing for a while
- Pain into the buttock, hip or thigh, most often the front or outer side of the thigh, sometimes the back of it
- Pain, tingling or numbness on the inner side of the knee or along the inner shin
- A knee that feels less steady on stairs, on slopes or when rising from a chair
- A weaker knee-jerk reflex when the knee is tapped during an examination
Some people have a clear pattern, and others have only a vague ache in the middle of the lower back with no leg symptoms. An MRI finding does not always match how someone feels day to day, so symptoms, examination and imaging are read together.
Arranging an L3-L4 Assessment in KL
Pain from L3-L4 can feel like a hip or knee problem, and a lower lumbar level can produce a similar pattern, so the first visit sorts these apart. It covers a detailed history, lumbar and hip movement, hip and knee strength, the knee-jerk reflex, feeling along the front of the thigh and the inner shin, and a femoral nerve stretch test done lying face down. Any X-ray or MRI is read against those findings before care options are discussed. Either Kuala Lumpur center can arrange it:
- Bukit Damansara (KL, main center): Call +603 2093 1000 or WhatsApp +60 17 269 1873 to see the Bukit Damansara / KL center.
- Bandar Sri Damansara (KL): Call +603 6262 5777 or WhatsApp +60 12 455 6939 to see the Bandar Sri Damansara center.
How an L3-L4 Problem Is Assessed at CSC
Lower back pain is one of the most common problems seen at Chiropractic Specialty Center, and from L3-L4 it often spreads into the buttock and thigh. Because the same pain can come from many structures, the first visit begins with a long interview. Its questions narrow down the likely source, which may be:
- a strained muscle or ligament
- facet joints pressing together (facet imbrication) or enlarging (facet hypertrophy)
- disc degeneration, or a disc bulge, protrusion, prolapse, herniation, extrusion or fragmentation
- segmental instability, where the level moves more than it should
- a slipped vertebra: spondylolisthesis, with or without a stress defect in a small bridge of bone at the back of the vertebra (spondylolysis), anterolisthesis or retrolisthesis
- a thickened ligamentum flavum, or narrowing of the spinal canal (spinal stenosis) or of the foramen (foraminal stenosis)
- pressure on the exiting L3 root or the traversing L4 root
The Examination at L3-L4
The examination comes next: range of motion, orthopedic tests, a neurological check of sensation, reflexes and strength, and muscle testing. At L3-L4 it pays close attention to the knee-jerk reflex, the strength of the hip flexors and the quadriceps, feeling on the inner side of the knee and shin, and the femoral nerve stretch test, in which the knee is bent while the person lies face down. In the study of herniations out to the side mentioned above, this test was positive in 91% to 95% of each group (Kido et al., 2016). Pressing along the bony points down the middle of the back, the spinous processes, also checks for a step, which can mean one vertebra has slipped on the next.
X-Ray or MRI: Choosing the Scan
Imaging is added only when it will be useful, and usually one test is enough: an X-ray or an MRI, rarely both. When the history and examination point to alignment, the soft tissues or the facet joints, as in facet joint syndrome, an X-ray may answer the question. When they point to a disc problem, from a bulge to a fragment, an MRI is used, because a disc diagnosis is confirmed on imaging rather than guessed. When a step is felt at the spinous processes, suggesting a slip such as a grade 1 or 2 spondylolisthesis with a pars defect, both an X-ray and an MRI are used.
Any scan is read alongside the examination. Disc changes are common in people with no back pain at all: in a review of 33 studies covering 3,110 people without symptoms, disc bulges were seen in 30% of 20-year-olds and 84% of 80-year-olds (Brinjikji et al., 2015).
Spondylolisthesis at L3-L4: Extra X-Ray Views
In Yama Zafer, D.C.'s experience, a slipped vertebra is uncommon at L3-L4 and seen more often at L4-L5 and L5-S1. A slip can still happen at any level of the spine, and a vertebra can move forward (anterolisthesis), backward (retrolisthesis) or to the side (Margetis and Gillis, 2025). In his experience, a slip in the lower back often comes with disc and joint wear, facet hypertrophy, a thickened ligamentum flavum, and narrowing of the canal and the foramina.
When an X-ray shows a slip, CSC may add three side-view (lateral) X-rays of the lower back: one standing upright, one bending forward (flexion) and one leaning back (extension). Comparing them shows whether the slipped level moves, which tells whether it is stable. An MRI may follow to show how the slip affects the discs, joints, ligaments, foramina, the spinal canal and the sac around the nerves, called the thecal sac.
L3-L4 Disc Bulge, Protrusion and Herniation: What the Terms Mean
Disc problems are less common at L3-L4 than at the two levels below it: in adults aged 25 to 55, more than 95% of lumbar disc herniations occur at L4-L5 or L5-S1 (Pojskic et al., 2024). When they do occur here, the labels on an MRI report describe how far disc material has moved.
At CSC, the stages are explained by what the disc is doing to the structures around it. In Yama Zafer, D.C.'s clinical terms, a disc bulge is a swelling of the disc's outer fibers that has not yet pressed on or pushed aside the thecal sac or the nerves. A protrusion or prolapse is the next step, where the outward bulge has grown enough to press on the thecal sac, the nerves or both.
Radiology reports use a related scale based on shape (Fardon et al., 2014). A bulge extends past the disc's normal edge around more than a quarter of its circumference. A herniation is more localized: in a protrusion, the displaced material is narrower than its base; in an extrusion, it is wider than its base in at least one direction; and a piece that has separated completely is called a sequestration. The nomenclature also notes that these terms describe shape and do not by themselves imply symptoms or the need for a particular treatment.
L3-L4 Disc Bulge
An L3-L4 disc bulge spreads past the disc's usual edge over a wide arc while its outer wall stays intact. On its own, or together with loss of disc height or enlarged facet joints, it can reduce the room in the foramen or the lateral recess. A bulge toward the back and side can reach the traversing L4 root, and one out to the side can reach the exiting L3 root. The short CSC video above explains a bulging disc in about 20 seconds, and the guide to a disc bulge covers its causes and care.
L3-L4 Disc Protrusion
A protrusion is a more focal bump of disc material that the outer ring still holds in. A central or back-and-side protrusion can crowd the traversing L4 root, and a far-lateral one the exiting L3 root. A protrusion can follow repeated loading, such as long sitting or lifting, or a degeneration that began as a bulge. The CSC video above covers what a protruded disc is, and the guide to disc protrusion explains it in more depth.
L3-L4 Disc Prolapse and Extrusion
A prolapse means disc material has moved beyond its normal boundary further than in a bulge or protrusion, and an extrusion is the stage in which material pushes past the outer wall. Either can tighten the space for the exiting L3 or the traversing L4 root, more so when an annular tear, facet hypertrophy or a thickened ligamentum flavum is also present. The CSC video above gives a simple explanation of a prolapsed disc.
Fragmented and Sequestered Disc at L3-L4
In a fragmented disc, pieces of disc material have broken away near the canal. In a sequestered disc, a piece has separated completely and may move a short distance within the canal or the lateral recess. Fragments toward the back and side more often reach the traversing L4 root, and fragments out to the side the exiting L3 root. The CSC video above explains fragmented discs.
Other L3-L4 Findings on MRI and X-Ray
An L3-L4 report often lists more than one finding. Each is read the same way: by its type, its exact place and whether it matches the examination. The table gives a quick reference, followed by the findings that most often need explaining.
| Term | What it describes at L3-L4 |
|---|---|
| Disc desiccation or degeneration | The disc has lost water and height with age and load; very common. |
| Disc space narrowing | The disc is thinner than it was, so more load passes to the facet joints behind it. |
| Disc bulge | The disc extends past its usual edge over a broad arc; the outer wall stays intact. |
| Protrusion or herniation | A more focal displacement of disc material; it may or may not touch a nerve. |
| Annular tear (fissure) | A split in the outer ring of the disc; common, and not always painful. |
| Modic changes | Signal changes in the bone beside the disc's endplates, often seen with disc wear. |
| Facet hypertrophy | Enlarged facet joints that can narrow the nerve corridors. |
| Ligamentum flavum hypertrophy | A thickened ligament inside the canal that can buckle inward and narrow it. |
| Foraminal narrowing | Less room in the side opening where the L3 root exits. |
| Spondylolisthesis | One vertebra sitting forward of, or behind, the one below; less common at this level than at L4-L5 and L5-S1. |
| Synovial cyst | A fluid-filled sac growing from a facet joint; most often found at L4-L5. |
| Tarlov cyst | A fluid-filled sac on a nerve-root sleeve, usually in the sacrum below this level. |
Disc Space Narrowing and Loss of Disc Height
Reports often describe mild disc space narrowing or loss of disc height at L3-L4. The word mild describes how the disc looks on the scan, not how much the finding matters. A narrowed disc passes more load to the facet joints behind it, which can lead to arthritis and enlargement of those joints (facet hypertrophy). It lets the ligamentum flavum buckle into the canal and narrow it, and the disc itself becomes more prone to tears, bulges and protrusions.
In an MRI study comparing the discs and facet joints, facet joint arthritis was not found at any level without disc degeneration, and most of it appeared where disc degeneration was advanced, which supports the view that the disc changes first (Fujiwara et al., 1999). Narrowing can also affect the nerves before it causes much back pain, with numbness or weakness in the leg and difficulty standing or walking for long.
Facet Hypertrophy and a Thickened Ligamentum Flavum
With years of load, the cartilage of the facet joints can thin, and the joint edges and capsule thicken in response. Morning stiffness, a tight feeling when arching back, and tiring with standing or walking are common descriptions. At L3-L4, enlarged facets can narrow the lateral recess and the foramen.
The ligamentum flavum lines the back of the spinal canal. In an MRI study of 308 of these ligaments in 77 people, the ligament thickened with age, and the increase was larger at L3-L4 and L4-L5 than at L2-L3 and L5-S1. The thickening came mainly from scar-like tissue (fibrosis) linked with mechanical stress that builds up over the years (Sairyo et al., 2005).
Annular Tears at L3-L4
An annular tear, also called an annular fissure, is a split in the outer ring of the disc. It is also found in people without back pain: in the same review of 3,110 people without symptoms, annular fissures were seen in 19% of 20-year-olds and 29% of 80-year-olds (Brinjikji et al., 2015). Lifting with a rounded back or a sudden bend adds strain to the ring, which is why both are avoided while a tear settles.
Synovial and Tarlov Cysts
A synovial cyst is a fluid-filled sac that grows from a facet joint. These cysts are found in fewer than 1 in 200 people with back symptoms, most often at L4-L5, the most mobile level, and some cause no symptoms at all (Khan and Girardi, 2006).
A Tarlov cyst forms on the sleeve of a nerve root, usually in the sacrum below L3-L4, and can show up on a lumbar MRI. Most are found by chance, are typically benign and cause no symptoms, and can simply be monitored (Lucantoni et al., 2011).
Why L3-L4 Wears: Load, Posture and Injury
Long sitting with a rounded posture, repeated bending and lifting with the load held away from the body, weak trunk muscles, tight hips, past back injuries, high-load sport and long drives all add load to L3-L4. Over months and years, that load can speed up drying of the disc, thickening of the facet joints and buckling of the ligamentum flavum. A single event, such as a fall or an awkward lift, can then aggravate a segment that was already changing.
Research describes two broad patterns of disc wear. One starts with damage to the disc's endplates, mostly affects the upper lumbar and thoracic spine, often begins before age 30, runs strongly in families and is linked with compressive injuries such as a fall onto the buttocks. The other starts with a tear or prolapse in the outer ring, mostly affects the lower lumbar spine, develops after age 30 and is linked with repeated bending and lifting (Adams and Dolan, 2012). L3-L4 sits in the middle of the lumbar spine, between these two regions, so both a history of falls and years of bending and lifting are discussed at the first visit.
How L3-L4 Problems Are Cared For at CSC
At Chiropractic Specialty Center, chiropractors and physiotherapists work as one team, and each method is chosen for the tissue that needs it: the disc, a facet joint, a nerve root or the muscles that support the segment. Depending on the assessment, an L3-L4 plan may draw on:
- spinal decompression therapy, used with the aim of reducing load on the disc, which at CSC forms part of NSD Therapy®
- flexion-distraction (the Cox technique), a gentle, rhythmic method on a table that bends and gently stretches the lower back
- ultrasound and electrotherapy
- shockwave therapy
- high-intensity laser therapy
- cold and heat therapy with the QMD cryothermal device
- trigger point therapy and myofascial therapy for tight, irritated muscles
- stretching and strengthening, once the back is ready
- balance and neuromuscular exercises
- pain management with therapeutic devices
The center's motto, "No pain, more gain", sums up the approach. Care is planned to be pain free, and patients are asked to speak up the moment anything feels uncomfortable during a session, since what hurts during care can show up later as more inflammation and pain.
What Is Avoided With an L3-L4 Disc Problem
While the disc is irritable, the plan leaves out bending and twisting movements, and any rotational or aggressive physiotherapy, manual therapy or chiropractic manipulation, because twisting can aggravate a disc problem. Stretching and exercise are held back in the early stage. The same thinking applies outside the center:
- no lifting with a rounded back and no sudden jerking movements
- no aggressive traction such as the Y-Strap or the Ring Dinger®
- no exercise routine copied from elsewhere that ignores the findings at this level
When Exercise Starts and Which Exercises Come First
Exercise starts only when the back is stable and ready, usually from the 5th to the 7th session and for some people from the 3rd. The first exercises are chosen by the severity of the problem and may include:
- Kegel exercises, when the pelvic floor muscles are weak
- wall-assisted squats, which train the quadriceps that the L3 and L4 roots supply
- cat and camel, a gentle movement of the spine done on hands and knees
- strengthening for the glutes, hamstrings, calves and quadriceps
- core canister exercises for the deep muscles that wrap around the trunk: the diaphragm, the pelvic floor, the deep abdominal muscles and the multifidus
A Cochrane review of 249 trials found moderate-certainty evidence that exercise probably reduces chronic low back pain compared with no treatment, usual care or placebo (Hayden et al., 2021). The guide to the physiotherapy gym in KL explains how supervised exercise differs from a regular gym.
Gym Training With an L3-L4 Problem
The gym is discouraged at first, and free weights stay out for 2 to 6 months. Once the back is stable, free weights, deadlifts and leg presses still stay out, while some machines can be used: hip adductor and abductor machines, leg curls and leg extensions, light rowing, lat pulldowns and, for some people, the chest press. Treadmill walking stays at zero incline to keep extra load off the lumbar discs.
Daily Habits That Take Load Off L3-L4
Daily habits decide how much load the segment carries between sessions. While an L3-L4 disc is irritable, the advice at CSC is:
| Habit | Advice |
|---|---|
| Sitting | Sit for no more than 45 minutes at a time, stand up and walk every 30 to 45 minutes, and avoid slouching over a desktop or laptop. |
| Bending and twisting | Keep bending and twisting at the waist to zero. |
| Lifting | Avoid lifting; if it cannot be avoided, keep the load under 2 kg. |
| Stretching | No stretching routine in the early, irritable stage, and no stretch that bends or twists the spine deeply until the disc has settled. |
| Yoga | Must be avoided with an L3-L4 disc problem, at every stage of care, not only while the disc is irritable. |
| Driving and travel | Avoid long road trips. When one is needed, ride as the front-seat passenger with the seat reclined; when driving, stop every 45 to 60 minutes to get out, walk and stretch the calves. |
| Sleep | Sleep in the least painful position, and aim for 6 to 8 hours a night to support healing. |
| Ice | Ice the area 2 to 3 times a day, at least 2 hours apart, for 10 to 15 minutes each time, with the ice pack wrapped in a cloth and a timer set. |
| Sport | Return after recovery. Leave out any activity that hurts at the time or raises pain within the next 72 hours, since inflammation can take up to 72 hours to show. |
Each of these steps follows one principle: increase what helps the disc settle and decrease what keeps loading it.
Older and Younger Adults: How the Plan Differs
Age changes what L3-L4 usually shows. In an MRI study, facet joint arthritis was minimal under age 40 and seen to varying degrees over 60 (Fujiwara et al., 1999), and in a Japanese population study of 1,009 adults with an average age of 66, about 1 in 10 had symptomatic lumbar spinal stenosis (Ishimoto et al., 2012).
For an older adult with stenosis or arthritis at L3-L4, the plan is gentler: more change to daily habits, stretching delayed, more neuromuscular stability work, such as the rocker board, wobble board, balance on a gym ball and Kegel exercises, lighter and shorter decompression sessions, and gentler manual and myofascial care. A younger adult with a disc bulge usually follows the progression described above, from settling the irritated tissue to strengthening.
Teenagers who play sport or carry heavy school bags sometimes have low back pain, and the guide to chiropractic care for children explains how L3-L4 and the rest of a growing lower back are assessed.
How Progress Is Measured and When Surgery Is Considered
Progress is checked against the first visit. The same tests are repeated, pain is scored on a 0 to 10 visual analog scale (VAS), and the patient's own account of daily life is part of every review, so the plan can be adjusted early.
There is good reason for patience. Herniated disc material can shrink on its own: across 11 studies, this happened in about two in three people with a lumbar disc herniation who were managed conservatively (Zhong et al., 2017). Herniations out to the side, which at L3-L4 press on the exiting L3 root, have also settled with conservative care: in one series, 12 of 17 resolved without surgery, with complete resolution of the radiating pain (Rust and Olivero, 1999).
When Surgery Is Considered
Surgery is considered only when the conservative plan is not producing results, or in severe cases, such as a sequestered disc, an infection, or the nerve signs described below. Thigh weakness that keeps getting worse, such as a knee that feels less and less steady on stairs, calls for a careful assessment by a competent provider, and conservative care can still be a reasonable route for as long as it keeps producing results.
With back, buttock or thigh pain from an L3-L4 disc problem, numbness that develops or worsens around the genitals, between the genitals and anus, or around the anus needs urgent medical attention: a thorough assessment by a competent clinician the same day. New difficulty passing urine needs the same urgent assessment; loss of bladder or bowel control does not have to occur first, and if it does occur, it is urgent too. These symptoms have several possible causes. Some may call for an invasive procedure, but the assessment determines what care is appropriate, rather than assuming surgery is necessary.
Current fees are published on the chiropractic price in Kuala Lumpur and physiotherapy fees in Kuala Lumpur pages.
Frequently Asked Questions About L3-L4 Disc, Joint, and Nerve Care
Can an L3-L4 disc problem recover fully?
It is the question patients ask most often at CSC, and the research gives reason for hope: across 11 studies, herniated disc material shrank on its own in about two in three people managed conservatively (Zhong et al., 2017). How fully each person recovers still varies, because everyone heals differently. In Yama Zafer, D.C.'s experience, people who left the problem untreated for a long time are more likely to have some lasting symptoms or flare-ups after recovery. Progress is measured at each review, so the plan can change early if it is not working.
What nerves does L3-L4 affect?
Two nerve roots pass through L3-L4. The L3 root exits through the foramen at this level, and the L4 root passes behind the disc to exit one level lower. Both help form the femoral nerve, which works the hip flexors and the muscles that straighten the knee, and carries feeling from the front and inner thigh and the inner side of the lower leg (Refai et al., 2023). A disc change out to the side tends to affect the L3 root and one toward the back and side the L4 root, which is why the direction noted on an MRI report matters.
What are the symptoms of an L3-L4 disc bulge?
An L3-L4 bulge often brings lower back pain or stiffness, especially after standing, with pain, tingling or numbness that can spread into the buttock, the front of the thigh, the inner side of the knee or the inner shin. Some people notice that a knee feels less steady on stairs or when rising from a chair, or a weaker knee-jerk reflex shows up during an examination. Many bulges cause no symptoms at all, since bulges are found in 30% of 20-year-olds without back pain (Brinjikji et al., 2015), so a bulge is matched to the examination before it is treated as the cause.
Is an L3-L4 disc bulge serious?
Often it is not. A bulge is an early stage of disc change, and many are found by chance in people without pain. Whether one matters depends on its size, its direction and whether it is pressing on the L3 or L4 root, which the examination shows. A mild bulge with back stiffness is usually cared for with gentle, conservative methods and changes to daily habits, such as shorter spells of sitting and no bending or twisting at the waist. The signs that call for prompt assessment are set out in the section on when surgery is considered.
Can L3-L4 cause sciatica?
It can cause leg pain, though usually not the classic sciatica pattern. Sciatica runs down the back of the leg along the sciatic nerve, which forms from the lower lumbar and sacral roots (L4 to S3), and it most often comes from L4-L5 or L5-S1. An L3-L4 problem more often sends pain down the front of the thigh toward the knee and the inner shin, along the femoral nerve that the L3 and L4 roots help form. Because the L4 root also contributes to the sciatic nerve, the two patterns can overlap, and the examination sorts out which nerve is involved. The guide to sciatica explains the lower pattern.
What does mild disc space narrowing at L3-L4 mean?
It means the L3-L4 disc is thinner than it was, usually because it has lost water and height with age and load. Mild describes how it looks on the scan, not how much it matters. A narrowed disc passes more load to the facet joints, which can enlarge them, lets the ligamentum flavum buckle into the canal, and makes tears and bulges more likely. It can also affect the nerves, with numbness, weakness or difficulty standing or walking, sometimes before much back pain is felt, so it is always read together with the examination.
Which exercises are avoided with an L3-L4 disc problem?
In the early, irritable stage no exercise is given at all, and twisting, deep bending, free weights, deadlifts and leg presses all stay out; treadmill walking stays at zero incline. At CSC, exercise starts once the back is stable, usually from the 5th to the 7th session, with gentle choices such as wall-assisted squats, cat and camel, Kegel exercises and core canister work, followed by strengthening for the glutes, hamstrings, calves and quadriceps as the problem allows.
How long can someone sit or drive with an L3-L4 disc problem?
While the disc is irritable, the advice at CSC is to sit for no more than 45 minutes at a time, to stand up and walk every 30 to 45 minutes, and to avoid slouching over a desk or laptop. Long road trips are avoided where possible. When one is needed, the advice is to travel in the front passenger seat with it reclined, and a driver stops every 45 to 60 minutes to get out, walk and stretch the calves. Lifting is avoided too, and anything that cannot wait is kept under 2 kg.
Does an L3-L4 problem always need an MRI?
Imaging is added only when its result will change the plan, so many L3-L4 problems are assessed first by interview and examination alone. When those point to alignment, the soft tissues or the facet joints, an X-ray may be enough; when they point to a disc problem, an MRI shows the disc and nerves, so the diagnosis is confirmed rather than guessed. Both are used when a step felt along the spine suggests a slipped vertebra. Because disc changes are common in people without pain, every scan is read together with the examination (Brinjikji et al., 2015).
This guide describes L3-L4 problems and their care in general. It cannot assess any one person's back; that takes a history and an examination.
References
- Adams MA, Dolan P. Intervertebral disc degeneration: evidence for two distinct phenotypes. J Anat. 2012;221(6):497-506.
- Brinjikji W, Luetmer PH, Comstock B, et al. Systematic literature review of imaging features of spinal degeneration in asymptomatic populations. AJNR Am J Neuroradiol. 2015;36(4):811-816.
- Chakraverty R, Pynsent P, Isaacs K. Which spinal levels are identified by palpation of the iliac crests and the posterior superior iliac spines? J Anat. 2007;210(2):232-236.
- Fardon DF, Williams AL, Dohring EJ, Murtagh FR, Gabriel Rothman SL, Sze GK. Lumbar disc nomenclature: version 2.0: Recommendations of the combined task forces of the North American Spine Society, the American Society of Spine Radiology and the American Society of Neuroradiology. Spine J. 2014;14(11):2525-2545.
- Fujiwara A, Tamai K, Yamato M, et al. The relationship between facet joint osteoarthritis and disc degeneration of the lumbar spine: an MRI study. Eur Spine J. 1999;8(5):396-401.
- Hayden JA, Ellis J, Ogilvie R, Malmivaara A, van Tulder MW. Exercise therapy for chronic low back pain. Cochrane Database Syst Rev. 2021;9(9):CD009790.
- Ishimoto Y, Yoshimura N, Muraki S, et al. Prevalence of symptomatic lumbar spinal stenosis and its association with physical performance in a population-based cohort in Japan: the Wakayama Spine Study. Osteoarthritis Cartilage. 2012;20(10):1103-1108.
- Khan AM, Girardi F. Spinal lumbar synovial cysts. Diagnosis and management challenge. Eur Spine J. 2006;15(8):1176-1182.
- Kido T, Okuyama K, Chiba M, et al. Clinical diagnosis of upper lumbar disc herniation: Pain and/or numbness distribution are more useful for appropriate level diagnosis. J Orthop Sci. 2016;21(4):419-424.
- Lucantoni C, Than KD, Wang AC, et al. Tarlov cysts: a controversial lesion of the sacral spine. Neurosurg Focus. 2011;31(6):E14.
- Margetis K, Gillis CC. Spondylolisthesis. StatPearls. Treasure Island (FL): StatPearls Publishing; 2025.
- Pojskic M, Bisson E, Oertel J, et al. Lumbar disc herniation: Epidemiology, clinical and radiologic diagnosis WFNS spine committee recommendations. World Neurosurg X. 2024;22:100279.
- Refai NA, Black AC, Tadi P. Anatomy, Bony Pelvis and Lower Limb: Thigh Femoral Nerve. StatPearls. Treasure Island (FL): StatPearls Publishing; 2023.
- Rust MS, Olivero WC. Far-lateral disc herniations: the results of conservative management. J Spinal Disord. 1999;12(2):138-140.
- Sairyo K, Biyani A, Goel V, et al. Pathomechanism of ligamentum flavum hypertrophy: a multidisciplinary investigation based on clinical, biomechanical, histologic, and biologic assessments. Spine (Phila Pa 1976). 2005;30(23):2649-2656.
- Zhong M, Liu JT, Jiang H, et al. Incidence of Spontaneous Resorption of Lumbar Disc Herniation: A Meta-Analysis. Pain Physician. 2017;20(1):E45-E52.
These references describe the lumbar spine, L3-L4 problems and their care in general. None of them evaluates care at Chiropractic Specialty Center.
The Author of L3-L4 Spine Care Kuala Lumpur | Non-Invasive Joint & Disc
L3-L4 Spine Care Kuala Lumpur | Non-Invasive Joint & Disc was written by Yama Zafer, D.C., who has 30+ years in chiropractic and physiotherapy and founded Chiropractic Specialty Center in Kuala Lumpur in 2006.
Last Updated: L3-L4 Spine Care in Kuala Lumpur
L3-L4 Spine Care in Kuala Lumpur was last reviewed and updated on October 3, 2026.