


C2-C3 Segment Dysfunction: Spine, Nerves and Neck Pain
C2-C3 nerve compression symptoms tend to start high in the neck. The usual pattern is a one-sided headache at the back of the head, a stiff upper neck and, at times, a tingling scalp. C2-C3 is the joint between the second and third neck bones, where the turning upper neck meets the rest of the cervical spine.
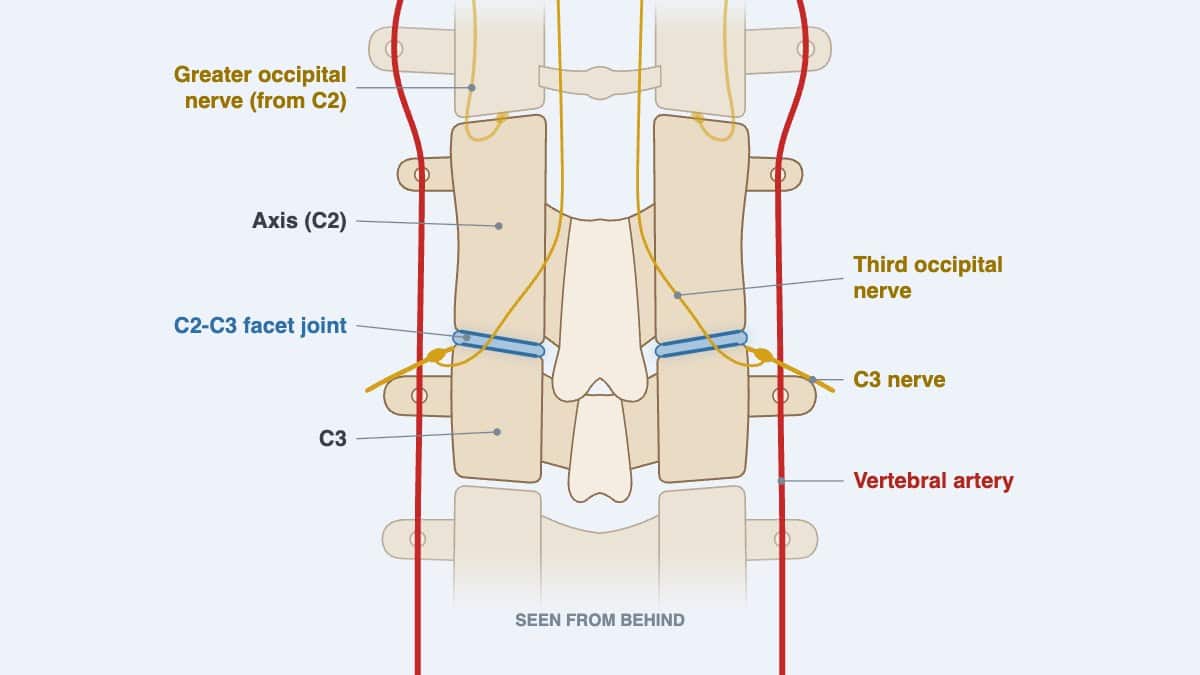
The third occipital nerve, a branch of the C3 nerve, curves around the back of the C2-C3 facet joint. When that joint is irritated, the pain is often felt in the head rather than the neck, so the source is easily missed. Long hours looking down, an old whiplash injury and wear of the first disc of the neck are common contributors.
I treat this level without twisting, kept within what you can comfortably tolerate, with physiotherapy and exercises in the same plan. Below are the nerve and facet joint symptoms, the hospital warning signs and where C2-C3 sits on the spine. Then come the muscles under the skull, my method and home exercises to check with your provider first.
For more information about the C2-C3 level, contact the Bukit Damansara (KL) main center: WhatsApp+60 17 269 1873 Call+603 2093 1000
C2-C3 Symptoms and Care: Key Takeaways
| Question | Short answer |
|---|---|
| Where is C2-C3 on the spine? | It is the facet joint level between the second neck vertebra, the axis, and the third. Here the turning upper neck meets the lower cervical spine, the five vertebrae from C3 to C7 (Kaiser and colleagues, 2023). |
| Is there a disc at C2-C3? | Yes, the highest disc in the spine, since none lies between the skull and C1 or between C1 and C2. A worn disc or bony spur here can narrow the opening the C3 nerve leaves through. |
| Why can C2-C3 feel like a headache? | The third occipital nerve crosses the back of this joint. Irritation here is often felt as headache at the back of the head rather than as neck pain (Djavaherian and Guthmiller, 2023). |
| How is C2-C3 confirmed as the source? | The symptom pattern and the examination point to this level. In research, two numbing blocks of the third occipital nerve confirm it, since no history or examination finding settles it alone (Lord and colleagues, 1994). |
| What does nerve compression here feel like? | Pain at the back of the head and upper neck, with a tender spot over the joint. At times there is tingling, numbness or stabbing pain over the scalp. Arm weakness or clumsy hands point lower down. |
| Which care has been studied for headache from this level? | Gentle mobilization and exercise for the deep neck muscles, tried before injection-based procedures. In 200 people with headache from the neck, manipulative therapy and exercise each lowered headache frequency for 12 months. |
| How do I treat C2-C3? | Without twisting or force. My methods include chiropractic manipulation that is non-rotatory using the Activator instrument. Care is kept within what you can comfortably tolerate, with physiotherapy in the same plan. |
| Which signs need a hospital first? | Call 999 at once for sudden stroke signs, and do not drive yourself. A suspected spine injury needs 999 too, with the person kept still. Both lists are under Warning Signs That Need a Hospital. |
| Do the muscles under the skull matter here? | Yes. Two of the four suboccipital muscles start on C2, and tissue bridges tie them to the spinal cord's covering. In my view, the upper neck relates to headaches, migraines, dizziness and vertigo; this is rare, but it can happen. |
C2-C3 Guide: Sections at a Glance
- C2-C3 Nerve Compression Symptoms
- Having the Upper Neck Assessed in Kuala Lumpur
- Where Is C2-C3 on the Spine? Vertebrae, Disc and Joints
- C2-C3 Stability, Motion and Pain Referral Patterns
- Suboccipital Muscles and Myodural Bridges Anchored on C2
- How Upper Cervical Dysfunction Affects Movement and Neurology
- Cranial Nerves and Eagle-Like Symptoms From the Upper Neck
- Jaw (TMJ) Problems and the Upper Neck
- What Causes C2-C3 Problems?
- C2-C3 Treatment Without Twisting or Force
- Self-Guided Support for C2 and C3 Function
- Other Cervical Spine Segments: How Each Works
- How Common Are Issues in the Cervical Spine?
- Summary Table: C2 and C3 Segment Insights
- Frequently Asked Questions (FAQ)
C2-C3 Nerve Compression Symptoms
Three nerve pathways run through this level, and each brings its own pattern. The third occipital nerve serves the C2-C3 facet joint. The C3 nerve root leaves the spine through the opening between C2 and C3. The greater occipital nerve, from C2, passes just above on its way to the scalp.
Third Occipital Nerve and Headache
The third occipital nerve comes from the rear branch of the C3 nerve. It curves around the back and side of the C2-C3 joint, then runs up along the semispinalis capitis muscle (Djavaherian and Guthmiller, 2023). When the joint is irritated, this nerve carries the pain to the back of the head.
Bogduk and Marsland (1986) blocked this nerve in ten people with suspected headache from the neck. In seven, the headache came from the C2-C3 joint through the third occipital nerve. They noted that such headache can look just like tension-type headache.
- A dull, one-sided headache at the back of the head, often with neck stiffness.
- Pain brought on by long, fixed positions, such as reading, screen work or driving.
- Tenderness over the C2-C3 joint, which was more common in people whose headache came from it (Lord and colleagues, 1994).
- Pain on looking up or turning, as the joint is loaded.
C2-C3 Facet Joint Symptoms
In volunteers, stretching the C2-C3 facet joint by injection brought pain to the upper neck and the back of the head (Dwyer and colleagues, 1990). Each neck joint gave its own pattern, which helps place the level. Facet arthritis is a common cause of mechanical neck pain (Kaiser and colleagues, 2023).
Lord and colleagues (1994) studied 100 people with neck pain lasting over three months after whiplash. The third occipital nerve and the C2-C3 joint explained the headache in 27 of them. Among those whose main complaint was headache, the share was 53 percent.
C3 Nerve Root Compression
When a nerve root is pressed, pain and symptoms spread beyond the neck, with possible tingling, numbness and muscle weakness (Margetis and colleagues, 2025). In younger adults, a disc injury or herniation is the usual cause. With age, worn discs and arthritic joints narrow the opening.
The C3 root does not supply the arm, so its symptoms usually stay in the neck and around the back of the head. Numbness, weakness or clumsiness in an arm or hand points to a lower level or to the spinal cord, and needs prompt assessment.
Where weakness is present, conservative care can continue only while the weakness itself is improving.
More than 85 percent of acute cervical radiculopathy settles within 8 to 12 weeks without specific treatment (Margetis and colleagues, 2025). Scan findings do not always match the symptoms, so the examination decides how much they mean.
Occipital Neuralgia
Occipital neuralgia is a stabbing, shooting pain over the back of the scalp that lasts seconds to minutes. Tenderness, altered skin sensation or pain from a light touch over the area is part of the diagnosis. The greater occipital nerve causes about 90 percent of cases; the third occipital nerve is rarely the one involved (Djavaherian and Guthmiller, 2023).
The third occipital nerve also sends many small branches to the greater and lesser occipital nerves. That overlap can make its symptoms hard to separate from theirs.
Warning Signs That Need a Hospital
The stroke signs below come from the US Centers for Disease Control and Prevention. If any appear, call 999 at once, and do not drive yourself:
- Sudden numbness or weakness of the face, arm or leg, especially on one side of the body.
- Sudden confusion, trouble speaking or difficulty understanding speech.
- Sudden trouble seeing in one or both eyes.
- Sudden trouble walking, dizziness, loss of balance or lack of coordination.
- Sudden severe headache with no known cause.
Mayo Clinic's first-aid advice is to suspect a spine injury in any of these situations. Call 999, keep the person still and do not move the head or neck:
- A head injury followed by a continuing change in how alert the person is.
- Severe pain in the neck or back.
- An injury that put heavy force on the back or the head.
- Weakness, numbness or paralysis, or poor control of the arms, legs, bladder or bowels.
- A neck or body twisted or held in an odd position.
Having the Upper Neck Assessed in Kuala Lumpur
The C2-C3 segment is examined as part of an upper neck assessment at both centers of Chiropractic Specialty Center. There, head posture, neck movement and the headache pattern are reviewed together. Travel details are on the Bukit Damansara contact page and the Bandar Sri Damansara contact page, and the contact page lists both centers' hours.
The assessment looks at the jaw joints and the whole neck, from the skull down, as well as the upper back. Bring any neck X-rays or MRI images with their reports. Mention recent injuries, dizziness, changes in vision, and any numbness or weakness.
- Bukit Damansara (KL, main center): Call +603 2093 1000 or WhatsApp +60 17 269 1873 to see the Bukit Damansara / KL center.
- Bandar Sri Damansara (KL): Call +603 6262 5777 or WhatsApp +60 12 455 6939 to see the Bandar Sri Damansara center.
Where Is C2-C3 on the Spine? Vertebrae, Disc and Joints
C2 and C3 are the second and third vertebrae of the neck. C2, the axis, carries the dens, a peg of bone that C1 turns around, and it is the main weight-bearing bone of the upper neck. C3 is the first of the five subaxial vertebrae, C3 to C7, which share much the same shape (Kaiser and colleagues, 2023).
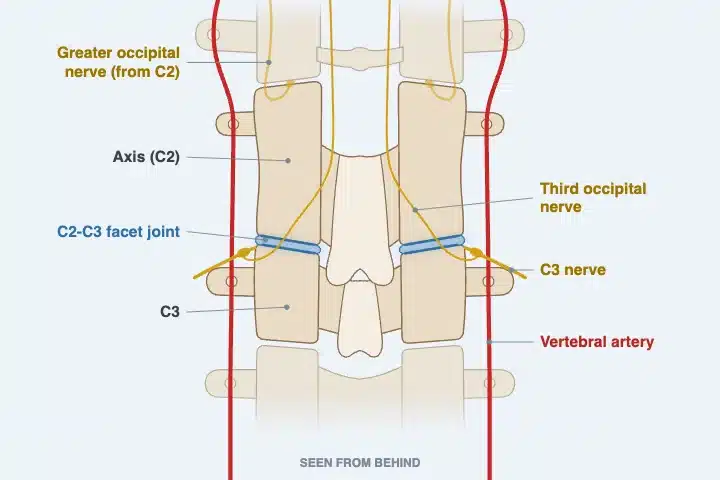
The two bones meet at the disc in front, at small uncovertebral joints beside it and at a facet joint on each side behind. Above C2 there is no disc, so the C2-C3 disc is the first one in the spine. The uncovertebral joints form where bony lips on the top of C3, the uncinate processes, meet C2. They serve to keep one vertebra from slipping on the next (Kaiser and colleagues, 2023).
Both C2 and C3 have a split spinous process at the back, the bump you can feel along the neck. The vertebral arteries climb through openings in their side processes on the way to the skull. Near the front, the common carotid artery divides at about the level of C3 (Kaiser and colleagues, 2023).

The C2-C3 joint links the upper cervical spine to the mid-neck and contributes to extension, side bending and rotation. The third occipital nerve, a branch of the C3 nerve, crosses the back of the joint. It carries sensation from the upper neck and the back of the head.
When C2-C3 becomes stiff or irritated, the result can be headache at the back of the head, neck stiffness or fatigue with sustained postures. Because of these nerve connections, symptoms often show up during reading, screen use or driving.
C2-C3 Stability, Motion and Pain Referral Patterns
The C2-C3 segment connects the more mobile atlas-axis (C1-C2) complex with the lower cervical spine. It acts as a transition zone for load and for head and neck coordination.
When the C2-C3 joint was stimulated in volunteers, the pain was felt in the upper neck and the back of the head. Irritation at this level can also refer toward the side of the head or behind the ear. That is the area of the lesser occipital nerve, which shares branches with the third. When motion here is restricted, muscles from the suboccipital region down to the shoulders can take on extra strain.
At CSC, gentle mobilization and targeted muscle activation are used at this level without high-force adjustments. The main center in Bukit Damansara has more information on how upper neck care is organized.
For a child with neck stiffness or headaches, assessment of the upper neck, C2-C3 included, is described in the guide to chiropractic care for children. Age guidance is set out in the guide to neck manipulation in children.
Suboccipital Muscles and Myodural Bridges Anchored on C2
Four small muscles lie between the base of the skull and the top two neck bones. Together they hold the head's posture and steer its small nodding and turning movements. The suboccipital nerve, the rear branch of C1, supplies all four (George and Tadi, 2023).
Two of the four start on the spinous process of C2, so C2 is their anchor below:
| Muscle | Lower attachment | Upper attachment | Main action |
|---|---|---|---|
| Rectus capitis posterior major | C2 spinous process | Skull, at the inferior nuchal line | Head tilted back and turned to the same side |
| Obliquus capitis inferior | C2 spinous process | Transverse process of C1 | Head turned to the same side |
| Rectus capitis posterior minor | Posterior tubercle of C1 | Skull, at the inferior nuchal line | Head tilted back |
| Obliquus capitis superior | Transverse process of C1 | Skull, between the nuchal lines | Head tilted back and bent sideways |
Three of them frame the suboccipital triangle, where the vertebral artery and the suboccipital nerve lie (George and Tadi, 2023). The greater occipital nerve, from C2, crosses the same triangle.
Myodural Bridges: Muscle Linked to the Spinal Cord's Covering
Strands of connective tissue, called myodural bridges, cross the space behind the spinal cord. They join the deep muscles here to the dura, the tough sheath around the cord. Bridges have been traced from both rectus capitis posterior muscles (Enix and colleagues, 2014).
In a dissection study of 12 obliquus capitis inferior muscles, every one sent visible tissue strands to the dura (Pontell and colleagues, 2013). That muscle runs from C2 to C1, right above the C2-C3 level.
The bridges may anchor the cord and keep the dura from folding as the head moves. A sudden whiplash-type movement can pull on the dura through them (Enix and colleagues, 2014). Zhang and colleagues (2026) review evidence connecting changes in these bridges with cervicogenic headache, cervicogenic dizziness and Chiari malformation type I.
Symptoms Linked to the Suboccipital Muscles
- Headache from the neck: tension in these muscles may pull on the dura through the bridges. This remains a hypothesis (George and Tadi, 2023).
- Tension-type headache: of 20 people with chronic tension-type headache, 13 had active trigger points in these muscles. Their headaches were stronger and more frequent than in those with latent ones (Fernández-de-las-Peñas and colleagues, 2006).
- Pinched nerves: overtight suboccipital muscles, trapezius or splenius capitis can press on the C1 to C3 nerves leaving the spine (Kaprive and Das, 2023).
- Scalp pain: the greater occipital nerve can be pinched at the lower edge of the obliquus capitis inferior (Djavaherian and Guthmiller, 2023).
- Balance: a pilot study of seven people with chronic neck pain found these muscles wasted and fatty. Their standing balance was poorer (McPartland and colleagues, 1997).
- Whiplash: these muscles can strain and go into spasm. Lasting pain can come from the spasm or from damage to the suboccipital nerve (George and Tadi, 2023).
In my view, headaches, migraines, dizziness and vertigo all relate to the upper cervical segments, C2-C3 among them. Mental fog can come with them. These symptoms are rare, but they can happen, so the inner ear, blood pressure and other causes are checked first.
Posterior Brain Circulation and Neck Arteries
Each vertebral artery climbs through the openings in the side processes from C6 upward, passing C3 and C2 on the way (Kaiser and colleagues, 2023). Inside the skull, the two arteries merge into the basilar artery, which feeds the brainstem directly (Kaprive and Das, 2023).
The same posterior circulation supplies the thalamus, the cerebellum and the occipital lobes (Benjamin and Lui, 2025). Branches of the C1 to C3 nerves travel beside the artery above C3. In monkeys, electrical stimulation of the nerves around it barely changed the artery's flow (Bogduk and colleagues, 1981).
Muscle can matter more than nerve here. With marked atherosclerosis, contracting suboccipital muscles may squeeze the artery slightly, lowering its flow and bringing light-headedness or dizziness (George and Tadi, 2023).
How Upper Cervical Dysfunction Affects Movement and Neurology
Upper cervical dysfunction, particularly at the C2-C3 segment, can influence more than local muscles and ligaments. When the facet joint between C2 and C3 becomes stiff, irritated or inflamed, it can sensitize the third occipital nerve. That nerve supplies the back of the head and upper neck.
The result can be headache referral, persistent neck tension or fatigue with sustained postures. Common contributors include joint capsule stiffness, previous whiplash and long periods with the head held forward.
Research findings include:
- Stimulating the C2-C3 facet joint in volunteers reproduces pain in the upper neck and the back of the head.
- Third occipital headache was found in 27 of 100 people with chronic neck pain after whiplash. Among those whose main complaint was headache, it was 53 percent.
- The third occipital nerve crosses the back of the C2-C3 joint, which is why this joint can produce headache rather than neck pain.
- Of headaches that start in the neck, roughly seven in ten involve the C2-C3 joint (Al Khalili and colleagues, 2022).
Pain signals from the C1 to C3 nerves reach the trigeminocervical nucleus in the brainstem. The trigeminal nerve, which serves the face and head, feeds the same nucleus (Al Khalili and colleagues, 2022). That shared relay is why the head can hurt when the source sits in the neck.
Changed signals from the neck's joint and muscle receptors can affect balance and eye control. People with neck disorders then report dizziness or unsteadiness (Treleaven, 2008). Neck-related dizziness is diagnosed only once other causes are excluded (Reiley and colleagues, 2017).
Cranial Nerves and Eagle-Like Symptoms From the Upper Neck
Eagle syndrome comes from a long or angled styloid process, a thin spike of bone below the ear. It can press on nearby cranial nerves or arteries, most often the glossopharyngeal nerve, bringing throat and neck pain (Dua and Mohseni, 2026).
The nerves named in that pain are the trigeminal (V), facial (VII), vestibulocochlear (VIII), glossopharyngeal (IX) and vagus (X) (Dua and Mohseni, 2026). In my experience these five are the usual ones, and the hypoglossal (XII) can make a sixth.
In my view, Eagle syndrome can be mimicked by a problem anywhere between the skull base and C3, since those same nerves pass close by. An upper cervical disorder can also add to Eagle-like symptoms that are already present. The Eagle syndrome guide and the C1-C2 guide describe these nerves in detail.
Brief stroke-like episodes, vertigo or fainting can follow when the styloid presses on an artery. Such warning signs need urgent medical assessment (Dua and Mohseni, 2026).
Jaw (TMJ) Problems and the Upper Neck
People with jaw joint disorders turned the top of the neck less far than people without them (Grondin and colleagues, 2015). In my experience, a long-standing upper neck problem can lead to jaw trouble, and the reverse happens too. That is why my assessment covers the jaw joints along with C1, C2 and C3.
These pages cover the jaw in detail:
- TMJ Disorders: Jaw Clicking, Stiffness and Assessment
- Jaw Chiropractor in KL: TMJ Care Guide
- TMJ Treatment in Malaysia: How Options Are Decided
- Jaw and TMD in Malaysia: Non-Invasive Care Options
- Temporomandibular Joint Dysfunction Care By Jaw Experts
- Causes of TMJ Pain: Jaw Concerns You Should Know
- Jaw Pain and TMD: What the Symptoms Can Mean
- Slipped Disc in the Jaw: TMJ Displacement, Causes & Care Options
What Causes C2-C3 Problems?
These are common contributors to C2-C3 strain or nerve irritation:
- Long hours with the head bent forward over a phone, laptop or desk, which raises the load on the upper neck.
- A whiplash injury, the setting of the third occipital headache studies above.
- Wear of the disc and facet joints with age, which can narrow the C3 nerve opening (Margetis and colleagues, 2025).
- Muscle tension left untreated for months. In Neck Trigger Points and Exercises, I explain how muscle trouble left too long goes on to involve the joints.
- Forceful cracking or pulling of the neck, which I warn against in my video Neck Cracks Are Dangerous.
- A jaw problem, which can load the upper neck on the same side.
In my experience, age plays a part in neck wear, but it is never the only factor. Posture, habits, past injuries and genetics all count.
None of these structures works alone. In my view, the upper neck, the jaw and the styloid behave like a kinematic chain: when one goes, the others follow. Stability in the middle and lower neck matters to the top of it as well.
When the middle or lower neck has instability, or a nerve or the spinal cord is compressed there, the upper neck can suffer as well. That is why my examination covers the whole neck, not one level alone.
C2-C3 Treatment Without Twisting or Force
Care for the C2-C3 segment at CSC is non-invasive and may include:
- Gentle joint mobilization, aimed at restoring glide and lessening stiffness at the segment.
- Myofascial work around the trapezius, levator scapulae and semispinalis muscles.
- Activation exercises for the deep neck flexors and the suboccipital muscles.
- Posture retraining and workstation advice for everyday support.
Upper neck chiropractic care at CSC uses non-rotatory chiropractic methods to avoid excessive stress on the facet joint and nearby nerves. Where an instrument suits, I use chiropractic manipulation that is non-rotatory using the Activator instrument. Each plan is based on the person's history, sensitivity and symptom pattern.
In Neck Cracks Are Dangerous, I put it plainly: “Aggressive neck care is never good and should always be avoided.” Should anyone try to yank or pull your neck, that video's advice is to “ask them to stop.”
Upper Cervical Chiropractic Care With Physiotherapy in KL
For the upper neck, combining careful chiropractic care with focused physiotherapy lets the hands-on work and the loading work support each other. At Chiropractic Specialty Center in Kuala Lumpur, upper neck care avoids forceful twisting. The chiropractors and physiotherapists work from one plan that covers both the joint and the surrounding soft tissues.
- Chiropractic adjustment: non-rotatory mobilization and gentle, segment-specific methods to restore movement at the C2-C3 joint.
- Physiotherapy: soft-tissue release, trigger point work, posture correction and deep neck stabilizing exercises.
A randomized trial in 200 people with cervicogenic headache tested manipulative therapy and specific neck exercise, each on its own or combined. Compared with no specific care, all three lowered headache frequency and intensity, and the effects held at 12 months (Jull and colleagues, 2002).
This combined approach is commonly used for:
- Neck problems that start with poor posture or repetitive strain.
- Cervicogenic headaches linked to the C2-C3 joint or the third occipital nerve.
- Stiffness or fatigue that worsens with screen time.
- Recovery after whiplash, chronic neck tension or disc-related neck problems.
Every plan starts with an assessment of how your neck moves, how the muscles respond and how the nerves function. Each step of care is kept within what you can comfortably tolerate. Should anything feel uncomfortable, tell the clinician at once so it can be made gentler; my motto is “No pain, more gain.”
On chiropractic or physiotherapy, my answer in Is Chiropractic Safe? 13 Questions Answered stays the same: “Don't choose between one or the other. Choose both.” That video also sets two checkpoints. If nothing has improved by the fifth session, I review why. If the tenth brings no change, continuing becomes a joint decision.
Yoga is not part of that plan. My Back Pain to Leg Pain talk is clear that people with a spinal disc problem should not do yoga at all. Many of its poses twist or load the upper neck.
Surgery has its place, but for disc problems I treat it as the last option. In Sciatica vs Slipped Disc: Video Explanation, I say: “Surgery should be the last option. Exhaust conservative route.”
By conservative care I mean focused care, planned from what your imaging and examination show. It targets the causes those findings document, takes in the whole neck and must do no harm. Run-of-the-mill neck treatment is something else, and many forms of conservative care are of no use. If focused care has been done properly and has not worked, surgery becomes an option.
The possible effects and risks are explained before care begins. The fee for a plan is explained and agreed before care begins.
Self-Guided Support for C2 and C3 Function
These gentle exercises can support the C2-C3 segment day to day. Check with a qualified clinician first, especially with a history of neck problems or dizziness. Stop if any exercise increases pain or stiffness or causes unusual symptoms.
- Chin tucks: gently draw the chin straight back, then return. Repeat 6 to 8 times, a few times a day, within a comfortable range.
- Soft-tissue release: apply light fingertip pressure where the neck meets the shoulder, over the levator scapulae.
- Posture awareness: sit with your ears over your shoulders and break up long periods of looking down.
- Relaxed breathing: lie with a small towel under your neck and take slow, full breaths to let the neck muscles relax.
In Neck Trigger Points and Exercises, I ask that each exercise first be checked with a doctor or other healthcare provider. I also say there: “Do not get someone else to push on you.” Numbness, tingling or discomfort means the neck is not ready, so stop.
If neck stiffness persists despite these steps, an assessment can identify which level is involved.
Other Cervical Spine Segments: How Each Works
- Occiput-C1 (Atlanto-Occipital Joint): This joint connects the skull to the spine and controls nodding, such as looking up and down. Its movement is closely coordinated with C1-C2.
- C1-C2 (Atlanto-Axial Joint): Provides about half of the head's rotation. Too much stress or instability here can strain the surrounding ligaments, especially after whiplash or with ligament laxity.
- C3-C4: Works with nearby levels to guide side bending and maintain neck posture. Problems here can strain muscles like the scalenes and contribute to shoulder or upper back tension.
- C4-C5: A transition point between the upper and middle neck. The C5 nerve root that exits here supplies shoulder muscles, and the C3 to C5 roots together form the phrenic nerve to the diaphragm.
- C5-C6: One of the most mobile and most loaded neck levels, protecting nerve roots that supply the arm and wrist. It is a common site of disc wear.
- C6-C7: Bridges neck movement into the upper back. Problems here can affect grip strength and hand coordination.
- C7-T1: The base of the neck, where the cervical spine meets the thoracic spine. It influences shoulder and upper back posture, especially in people who sit for long hours.
The upper cervical guide brings C0-C1, C1-C2 and C2-C3 together, with my method at the top of the neck.
How Common Are Issues in the Cervical Spine?

- Neck pain affected about 203 million people worldwide in 2020. The number is projected to reach about 269 million by 2050 (GBD 2021 Neck Pain Collaborators, 2024).
- Tilting the head forward increases the load on the neck. One model put the effective load at about 27 kg (60 pounds) at 60 degrees of bending, against about 5 kg upright (Hansraj, 2014).
- In 100 people with chronic neck pain after whiplash, about a quarter had headache from the C2-C3 joint (Lord and colleagues, 1994).
Summary Table: C2 and C3 Segment Insights
| Aspect | Details |
|---|---|
| Anatomy | Facet joint between C2 and C3, crossed by the third occipital nerve |
| Disc | The highest disc in the spine; wear here can narrow the C3 nerve opening |
| Function | Supports extension, some rotation and side bending, and head posture |
| Dysfunction may cause | Headache at the back of the head, neck stiffness, fatigue with sustained postures |
| Neurological link | Third occipital nerve, a common source of headache after whiplash |
| Muscles | Two suboccipital muscles start on C2 and connect to the dura through myodural bridges |
| Common symptoms | One-sided headache at the back of the head, upper neck tenderness, limited movement |
| CSC care model | Gentle mobilization, muscle activation, posture retraining |
| At-home guidance | Chin tucks, light soft-tissue release, posture breaks |
| Caution | Stop if dizziness, increasing pain or new symptoms occur |
| Hospital first | Stroke signs or a suspected spine injury: call 999 |
Every fee is published in advance. See the chiropractic price in Kuala Lumpur list and the physiotherapy fees in Kuala Lumpur list.
Still have questions? You may find our pages on headaches and migraines helpful too.
Frequently Asked Questions (FAQ)
What makes C2-C3 different from other cervical joints?
C2-C3 is the bridge between the rotation-focused upper neck and the lower cervical spine. Unlike C1-C2, which drives head turning, C2-C3 mainly supports extension and small neck movements, and it sits directly beneath the third occipital nerve. It also holds the first disc of the spine, since there is none above C2. That makes it the highest level where disc wear can narrow a nerve opening.
How can C2-C3 lead to cervicogenic headaches?
Irritation at the C2-C3 facet joint can sensitize the third occipital nerve, which supplies the back of the head and upper neck. The brain then reads the signal as headache rather than neck pain. The C1 to C3 nerves share a brainstem relay with the trigeminal nerve, which serves the face and head (Al Khalili and colleagues, 2022). Of headaches from the neck, this joint is the most frequent source.
Can chiropractic care for C2-C3 be given without rotation?
Non-rotatory mobilization is one of the options used for upper neck problems. A randomized trial found that manipulative therapy and specific exercise both reduced cervicogenic headache frequency (Jull and colleagues, 2002). At Chiropractic Specialty Center, non-rotatory methods are the standard approach at this level, and suitability is decided after assessment. Care is kept within what you can comfortably tolerate.
Is home care enough, or should I seek in-clinic support?
Home exercises suit many people, but persistent or recurring symptoms are worth an assessment to confirm the source and guide care. A sudden, severe headache, or headache with numbness, weakness, or speech or vision changes, needs prompt medical assessment. For sudden stroke signs, call 999 at once. The full lists are under Warning Signs That Need a Hospital, above.
Is this approach suitable for seniors or those with chronic neck issues?
Gentle, low-force methods are generally suited to older adults and to people with long-standing neck problems. Each upper cervical plan is adapted to age, bone health and sensitivity, and is decided after assessment. Bring a list of medicines, including blood thinners and steroids, and mention osteoporosis, rheumatoid arthritis or past neck surgery, since each changes what is suitable.
Does C2-C3 nerve compression need surgery?
Rarely at first. More than 85 percent of acute cervical radiculopathy settles within 8 to 12 weeks without specific treatment (Margetis and colleagues, 2025). Surgery is considered when imaging confirms the cause and symptoms persist after 6 to 12 weeks of focused conservative care. Disabling pain or worsening weakness can bring that forward. In my view, surgery has its place, but for disc problems only after focused care, built on the scans and examination, has not worked.
Can C2-C3 problems cause dizziness?
They can contribute. The neck's receptors feed balance and eye control, and people with neck disorders report dizziness and unsteadiness (Treleaven, 2008). Dizziness from the neck is diagnosed only once the inner ear and other causes are excluded (Reiley and colleagues, 2017). In my view, dizziness and vertigo can relate to the upper cervical segments; it is rare, but it can happen. Sudden dizziness with other stroke signs needs 999.
Do I need an X-ray or MRI for C2-C3?
Usually not at first. My rule, given in Is Chiropractic Safe? 13 Questions Answered: an X-ray comes only after a thorough assessment, and only when indicated. An X-ray shows bone. An MRI also shows the disc, ligaments and the space the nerves occupy, with no radiation. Scan findings do not always explain symptoms, so the examination guides what they mean (Margetis and colleagues, 2025).
How to Read This Guide
Lines in the first person give my own clinical positions, taken from my videos, talks or written answers. The video is named where it is the source. Research is cited by author and year and listed in full below. Where a study is small or an idea is still a hypothesis, the text says so. Only an examination in person can say what is behind your own symptoms.
References for Understanding C2 and C3 Segment Dysfunction
- Al Khalili Y, Ly NK, Murphy PB. Cervicogenic headache. StatPearls. Treasure Island (FL): StatPearls Publishing; 2022.
- Benjamin R, Lui F. Vertebrobasilar insufficiency. StatPearls. Treasure Island (FL): StatPearls Publishing; 2025.
- Bogduk N, Lambert GA, Duckworth JW. The anatomy and physiology of the vertebral nerve in relation to cervical migraine. Cephalalgia. 1981;1(1):11-24.
- Bogduk N, Marsland A. On the concept of third occipital headache. J Neurol Neurosurg Psychiatry. 1986;49(7):775-780.
- Centers for Disease Control and Prevention. Signs and symptoms of stroke. CDC; 2026.
- Djavaherian DM, Guthmiller KB. Occipital neuralgia. StatPearls. Treasure Island (FL): StatPearls Publishing; 2023.
- Dua A, Mohseni M. Eagle syndrome. StatPearls. Treasure Island (FL): StatPearls Publishing; 2026.
- Dwyer A, Aprill C, Bogduk N. Cervical zygapophyseal joint pain patterns. I: A study in normal volunteers. Spine (Phila Pa 1976). 1990;15(6):453-457.
- Enix DE, Scali F, Pontell ME. The cervical myodural bridge, a review of literature and clinical implications. J Can Chiropr Assoc. 2014;58(2):184-192.
- Fernández-de-las-Peñas C, Alonso-Blanco C, Cuadrado ML, Gerwin RD, Pareja JA. Trigger points in the suboccipital muscles and forward head posture in tension-type headache. Headache. 2006;46(3):454-460.
- GBD 2021 Neck Pain Collaborators. Global, regional, and national burden of neck pain, 1990-2020, and projections to 2050: a systematic analysis of the Global Burden of Disease Study 2021. Lancet Rheumatol. 2024;6(3):e142-e155.
- George T, Tadi P. Anatomy, head and neck, suboccipital muscles. StatPearls. Treasure Island (FL): StatPearls Publishing; 2023.
- Grondin F, Hall T, Laurentjoye M, Ella B. Upper cervical range of motion is impaired in patients with temporomandibular disorders. Cranio. 2015;33(2):91-99.
- Hansraj KK. Assessment of stresses in the cervical spine caused by posture and position of the head. Surg Technol Int. 2014;25:277-279.
- Jull G, Trott P, Potter H, et al. A randomized controlled trial of exercise and manipulative therapy for cervicogenic headache. Spine (Phila Pa 1976). 2002;27(17):1835-1843.
- Kaiser JT, Reddy V, Launico MV, Lugo-Pico JG. Anatomy, head and neck: cervical vertebrae. StatPearls. Treasure Island (FL): StatPearls Publishing; 2023.
- Kaprive JF, Das JM. Anatomy, head and neck: atlantoaxial joint. StatPearls. Treasure Island (FL): StatPearls Publishing; 2023.
- Lord SM, Barnsley L, Wallis BJ, Bogduk N. Third occipital nerve headache: a prevalence study. J Neurol Neurosurg Psychiatry. 1994;57(10):1187-1190.
- Margetis K, Magnus W, Mesfin FB. Cervical radiculopathy. StatPearls. Treasure Island (FL): StatPearls Publishing; 2025.
- Mayo Clinic Staff. Spinal injury: first aid. Mayo Clinic; 2023.
- McPartland JM, Brodeur RR, Hallgren RC. Chronic neck pain, standing balance, and suboccipital muscle atrophy: a pilot study. J Manipulative Physiol Ther. 1997;20(1):24-29.
- Pontell ME, Scali F, Enix DE, Battaglia PJ, Marshall E. Histological examination of the human obliquus capitis inferior myodural bridge. Ann Anat. 2013;195(6):522-526.
- Reiley AS, Vickory FM, Funderburg SE, Cesario RA, Clendaniel RA. How to diagnose cervicogenic dizziness. Arch Physiother. 2017;7:12.
- Treleaven J. Sensorimotor disturbances in neck disorders affecting postural stability, head and eye movement control. Man Ther. 2008;13(1):2-11.
- Zhang L, Song X, Chen C, et al. The myodural bridge complex: a comprehensive review of morphology, physiology, developmental biology and pathology. Front Med (Lausanne). 2026;13:1790220.
These references describe C2-C3 anatomy, third occipital headache, nerve root compression, the suboccipital muscles, neck pain prevalence and the conservative care of cervicogenic headache. None of them tested care given at Chiropractic Specialty Center.
The Author of C2-C3 Nerve Compression & Facet Joint Symptoms: Care in KL
C2-C3 Nerve Compression & Facet Joint Symptoms: Care in KL was written by Yama Zafer, D.C., who has 30+ years in chiropractic and physiotherapy and founded Chiropractic Specialty Center in Kuala Lumpur in 2006.
Last Updated: C2-C3 Segment Dysfunction: Spine, Nerves and Neck Pain
C2-C3 Segment Dysfunction: Spine, Nerves and Neck Pain was last reviewed and updated on October 12, 2026.
Baca halaman ini dalam Bahasa Malaysia: Disfungsi C2-C3: Tulang Belakang, Saraf dan Sakit Leher