
Jaw Pain Treatment in Kuala Lumpur: TMJ and TMD Care
Jaw pain treatment in Kuala Lumpur starts by finding where the problem sits: the jaw muscles, the disc inside the joint, or the upper neck. TMJ means the jaw joint, and TMD its disorders; common signs are an ache after chewing, a click, or a jaw that catches or locks. Clenching, grinding, chin resting, old injuries and long dental work are common causes, and some people hear ringing in the ears.
For more information about jaw pain, contact either Kuala Lumpur center:

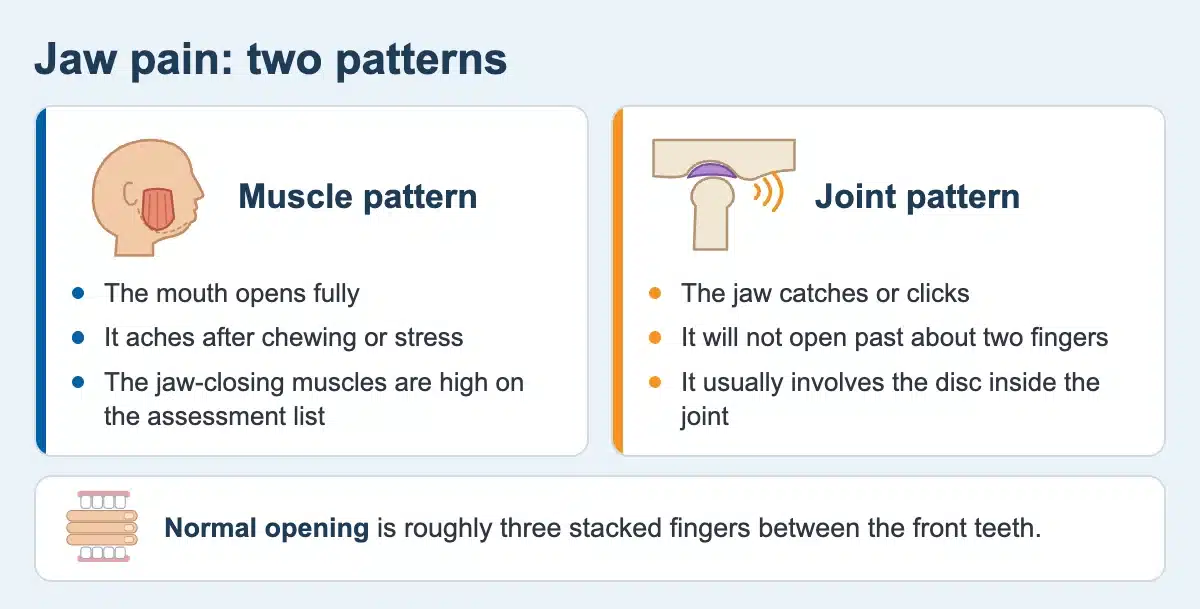
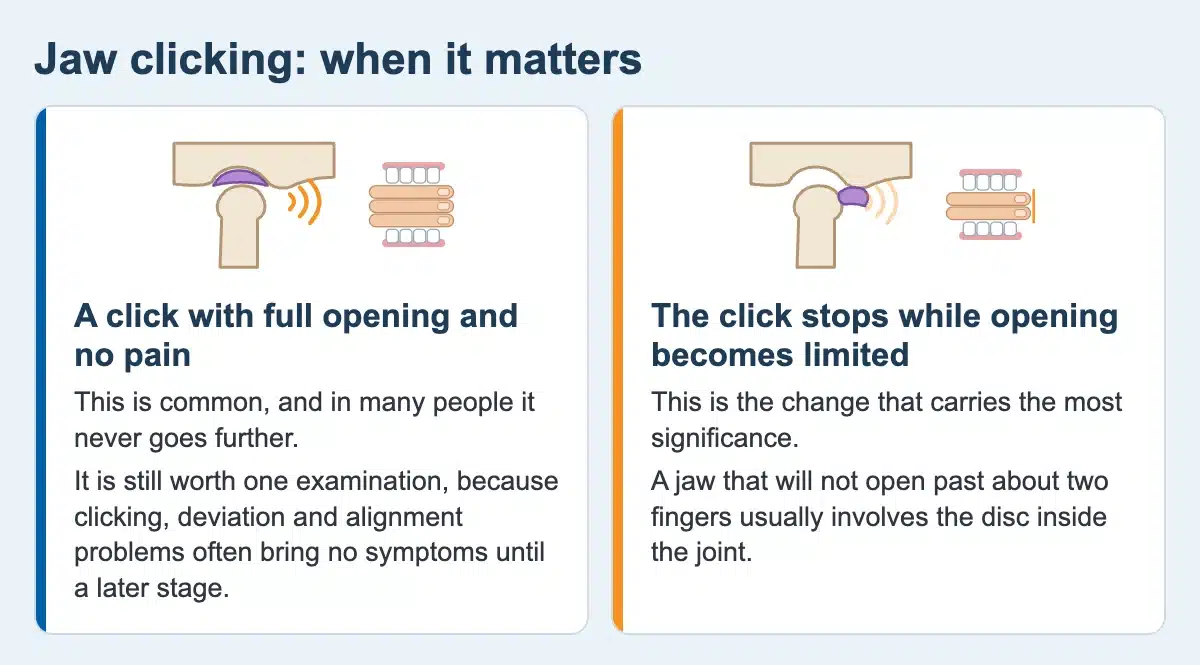
Jaw pain divides into two patterns that behave differently and call for different approaches. When the mouth still opens fully but aches after chewing or stress, the jaw-closing muscles are commonly high on the assessment list. A jaw that catches, clicks, or will not open past about two fingers usually points to the disc inside the joint. A click that stops while opening becomes limited is the change that carries the most significance. At CSC, upper cervical care at C1, the top neck bone, comes first, alongside gentle chiropractic care of the jaw, TMJ physiotherapy and jaw exercises. Home care, warning signs and fees are covered too.
Jaw Pain Treatment: Key Takeaways
| Topic | What to know |
|---|---|
| Upper neck and jaw | Yama Zafer, D.C., our founder, often finds jaw pain at its worst when C1, the top neck bone, has a problem on the same side. |
| Without surgery | Jaw pain is usually cared for without surgery; in our founder's view, surgery is for fractured jaws. |
| TMJ physiotherapy | Ultrasound, laser, electrotherapy and jaw exercises are used on the jaw joint, chewing muscles and upper neck, in one plan with the chiropractor. |
| Chin on one hand | Resting the chin on one hand turns the jaw joint into a weight-bearing joint, so this habit is asked about at the first visit. |
| Manual therapy research | A review of eight randomized trials found manual therapy of the chewing muscles, or of the upper neck, did better than control in TMD. |
| Night guards | A dentist makes and fits a night guard. It protects the teeth and lessens the strain on the jaw joints. |
| Clenching or grinding | Clenching holds the teeth together under load, while grinding slides them under load. Both are forms of bruxism, which a 2023 review linked with 2.25 times the odds of TMD. |
| Checked early | Symptoms are easier to read early, and a plan built on your own findings gives care a fair chance. |
| Progress | Progress is reviewed after 3 to 5 sessions, because the way the jaw responds is the clearest guide. |
Jaw Pain Research: Manual Therapy and the Upper Neck
Studies tie TMD to the upper neck, and hands-on care of the neck has lowered jaw pain in trials. Research highlights the interconnected nature of TMJ function and cervical spine stability, reinforcing the importance of a comprehensive care approach. The studies below look at structured, research-supported approaches to jaw pain treatment and jaw mobility care.
- Liberato and colleagues (2023) reviewed five randomized trials, 213 adults in all, in which therapists treated the neck in TMD. Compared with placebo or no care, face and jaw pain dropped by close to two points out of ten. Jaw function got better too, at least over the short term.
- La Touche and colleagues (2009) gave 19 people with muscle-related TMD 10 sessions of neck mobilization and exercise over 5 weeks. Pain fell, pain-free mouth opening increased, and the chewing muscles became less tender to pressure, after care and at 12 weeks. The study had no control group, and the authors concluded that care aimed at the neck may be beneficial.
- Grondin and colleagues (2015) tested turning at the top of the neck with the flexion-rotation test. All 37 people with TMD pain were restricted, while none of 20 people without symptoms were. The restriction was greater in those who also had headaches, and the authors advised examining the upper neck in TMD.
- Silveira and colleagues (2015) found that jaw disability and neck disability rose together (a correlation of 0.915, where 1 is perfect) in 40 women. They concluded that the neck should be considered when TMD is evaluated and treated.
- Armijo-Olivo and Magee (2013) tested 154 people and found a strong link between neck and jaw disability (a correlation of 0.82). People with TMD also had weaker endurance in the muscles that bend and straighten the neck.
Jaw Pain Treatment at Two Kuala Lumpur Centers
If jaw pain is affecting your quality of life, you deserve a thorough examination and personalized care. Appointment times for a jaw and upper neck assessment are available at both CSC centers in Kuala Lumpur:
- Bukit Damansara (KL, main center): Call +603 2093 1000 or WhatsApp +60 17 269 1873 to see the Bukit Damansara / KL center.
- Bandar Sri Damansara (KL): Call +603 6262 5777 or WhatsApp +60 12 455 6939 to see the Bandar Sri Damansara center.
Contact us to ask about a jaw assessment and appointment times; the contact page also lists the opening hours of both centers. For the first visit, please bring the X-rays and scans themselves, not only the reports, and any dental reports of the jaw or neck.
Jaw Pain Symptoms: TMD Signs to Notice
Jaw pain is a common problem that can affect how you chew, speak, or even smile. At Chiropractic Specialty Center, we understand how frustrating and limiting jaw pain can be. Jaw function involves coordinated movement between muscles, ligaments, and joint structures. Temporomandibular dysfunction (TMD) may arise when structural or muscular imbalances influence jaw mobility and alignment.
Symptoms such as jaw clicking, restricted movement, or pain while chewing may indicate changes in articular disc positioning or muscular function. A normal mouth opening fits about three stacked fingers between the front teeth. That simple measure can be recorded and compared later.
Signs That May Indicate Jaw Mobility Concerns (TMD)
- Grinding or clenching of teeth.
- Jaw stiffness upon waking.
- Frequent headaches or neck pain.
- Increased sensitivity when clenching the jaw.
- Clenching and jaw pain that get worse under stress.
- Clicking, popping, or catching sensations in the jaw joint.
- Difficulty fully opening the mouth.
- Locking sensation when attempting to open the jaw.
- Pain while chewing or yawning.
- Past injuries to the jaw, neck, or head.
- Problems such as arthritis in other joints.
- Changes in dental alignment or bite position, or teeth that no longer touch when you bite.
- Difficulty using front teeth for biting or tearing food.
- Teeth that are sensitive, loose, broken or worn.
Individuals experiencing multiple signs of jaw function changes may benefit from structured, non-invasive jaw mobility support. The figure below shows how the two patterns differ.
Causes of Jaw Pain: Habits, Injury and Dental Work
Jaw pain and limited jaw movement, including TMD, can result from structural changes in the TMJ, muscular imbalances, or influences from the neck. Jaw-related mobility concerns may arise due to localized or referred influences, including:
- Structural changes within the TMJ.
- Ligament changes around the joint.
- Neck mobility changes influencing jaw function, as in neck and upper back problems.
- Postural influences affecting jaw mobility.
- Soft tissue sensitivity related to past injuries or procedural positioning.
Habits load the jaw more than most people expect. These are the ones asked about most often:
- Clenching or grinding the teeth, which often gets worse with stress.
- Resting the chin on one hand, which forces the jaw joint to bear weight.
- Biting hard nuts, almonds, candy or chocolate.
- Opening the mouth very wide to yawn.
- Slouching over a phone or tablet, which strains the neck as well as the jaw.
Jaw Mobility Concerns Following Medical or Dental Procedures
Jaw-related changes may develop after extended mouth positioning, particularly during:
- Dental procedures requiring prolonged mouth opening.
- Medical interventions involving endoscopic or airway positioning.
A study by Huang and Rue (2006) followed 34,491 young people through dental insurance records. The risk of TMD was 1.6 times higher after wisdom tooth (third molar) removal. The authors concluded that the extraction appears to be a risk factor for TMD.
After a procedure, jaw mobility changes may be addressed through structured movement strategies that support long-term function.
Old Injuries and Whiplash
Jaw pain today can be the result of an old injury, such as a fall or a punch that damaged the jaw joint. A whiplash injury is an acceleration and deceleration injury that can damage, tear or irritate the ligaments of the neck and jaw. A fresh jaw injury where the jaw may be broken goes to a hospital emergency department first.
After whiplash, people often describe tenderness along the neck and pain with movement. Many also feel a heavy head and neck, and discomfort around the forehead and temples. The usual findings are less movement and tenderness over the side of C1 (its lateral mass) and over the jaw joints. The soft tissues of the upper, middle and lower neck are checked at the front, back and sides, from the mastoid behind the ear downward.
Jaw Pain and Cervical Spine Function
The neck and the jaw are closely linked: neck problems can lead to jaw pain, and a jaw problem can lead to neck pain. Jaw pain may also be influenced by cervical spine mobility changes, including:
- Spinal disc function changes, such as a slipped disc in the neck.
- A bulging disc.
- A herniated disc, or degenerated discs.
- Cervical spondylosis affecting joint movement.
- Postural influences from mobile device use.
Since the jaw and cervical spine are interconnected, changes in spinal movement patterns may influence jaw mobility. Maintaining cervical spinal mobility may assist in jaw function support. In our founder's view, the upper neck also depends on a stable middle and lower neck.
Jaw Problems in Children
Jaw pain in a child often comes with headaches, a stiff neck or teeth grinding at night, and exam stress can make it worse. Because a child's jaw joint keeps developing as the face grows, heavy grinding during these years deserves attention. A dentist can fit a night guard that lessens its impact. The guide to chiropractic care for children shows how a child's jaw is assessed and how care is kept gentle.
Jaw Clicking and Locking: What the Disc Is Doing
Understanding Jaw Function and the TMJ
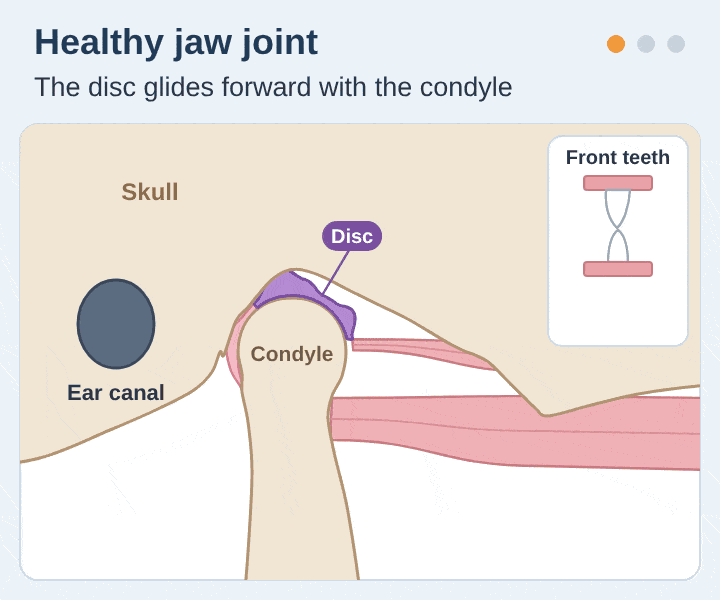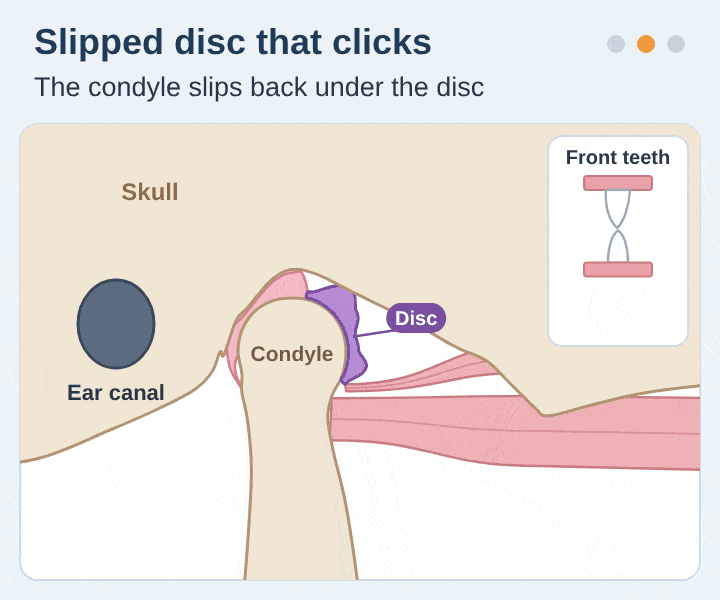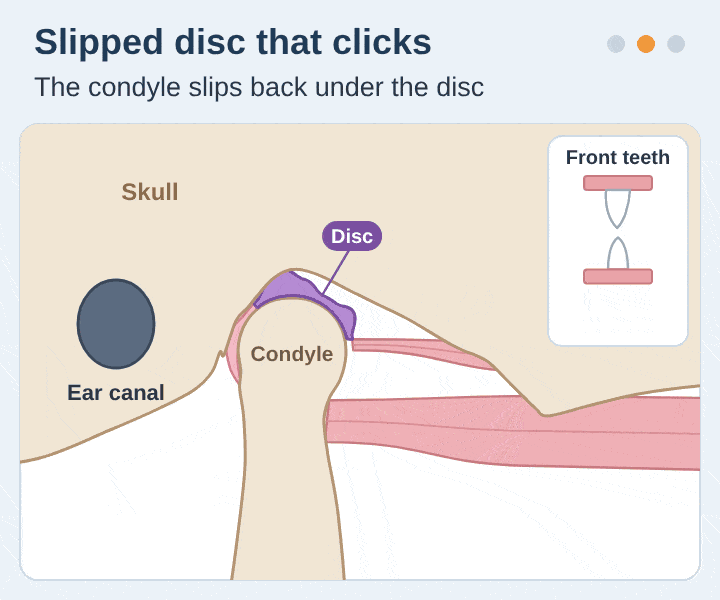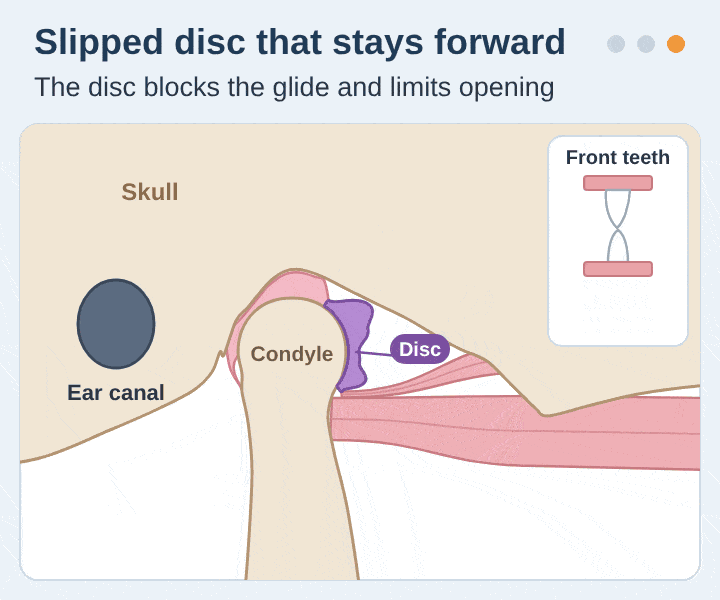
The temporomandibular joint (TMJ) is a complex structure located in front of the ears, connecting the jaw to the skull. It plays a crucial role in chewing, speaking, and overall jaw movement. The rounded top of the lower jaw, the condyle, sits in a hollow of the skull called the mandibular fossa.
A fibrous joint capsule wraps around the joint, and a ligament on its outer side strengthens it. The joint has its own pain-sensing nerves, mainly from the auriculotemporal and masseteric branches of the trigeminal nerve. Inside, the articular disc, sometimes called the jaw's meniscus, divides the joint into an upper and a lower space. This joint is supported by:
- Ligaments stabilizing joint movement.
- Muscles assisting and coordinating jaw mobility. The masseter, temporalis and medial pterygoid close the jaw; the lateral pterygoid moves it forward and, with the digastric, helps open it.
- An articular disc cushioning joint function.
Changes in any of these structures may contribute to jaw mobility concerns. The articular disc, a pad of dense, cartilage-like tissue, functions as a protective, shock-absorbing cushion, allowing for smooth jaw movement. If the disc experiences positional or structural changes, individuals may report:
- Jaw mobility imbalances when opening or closing the jaw.
- Clicking or shifting sensations during movement.
- Difficulty fully opening or closing the jaw.
Structured, non-invasive, chiropractic-assisted movement strategies may support the disc's position, mobility and stability.
Is Jaw Clicking Considered Normal?
A click with full opening and no pain is common, and in many people it never goes further. It is still worth one examination, because clicking, deviation and alignment problems in the jaw joint often bring no symptoms until a later stage.
Clicking or popping sounds when opening or closing the jaw may indicate functional adaptations in the temporomandibular joint and chewing muscles. They may also reflect changes in muscular coordination. Jaw clicking is often felt on one side only, on the side where the disc has shifted.
If jaw clicking is accompanied by jaw mobility restrictions, it may suggest:
- Soft tissue sensitivity affecting movement.
- Changes in ligament or disc function and positioning.
- Muscular imbalances influencing jaw alignment and coordination.
When jaw clicking does progress, the disc inside the joint usually slips further, and a mild slip can become moderate and then severe. Locking can follow without any warning. In other people, warning signs come first, such as stiffness, neck pain, headaches, a sore jaw or discomfort when chewing.
A two-year study by Kalaykova and colleagues (2010) followed 55 people whose disc clicked back into place on opening. Without episodes of locking, the click stayed stable. With intermittent locking, the disc returned later in opening, and in seven people the click disappeared as the disc no longer fully returned.
The authors concluded that intermittent locking may signal a disc that no longer returns to its place. They added that this loss only rarely brings a jaw that stays locked. Some patients at CSC describe the same pattern: a click they used to hear went quiet once the pain began.
For jaw clicking, TMJ physiotherapy at both Kuala Lumpur centers works on the joint and the chewing muscles around it, alongside upper cervical care.
When the Jaw Feels Out of Place
A jaw that feels out of place, often on one side, usually comes from the joint rather than the bone. The disc may have slipped forward, or the joint may be loose and slide too far when the mouth opens wide.
A loose jaw joint is called hypermobility. A 30-year follow-up of 13 people with loose jaw joints by Dijkstra and colleagues (1993) found more wear on X-rays than in 13 people without. The groups did not differ in symptoms or jaw function. The authors concluded that a loose joint is a secondary factor in jaw joint arthritis.
In a partial dislocation (subluxation), the jaw slips out of its track and returns by itself, often with a clunk. In a full dislocation, the jaw is stuck open and will not close. A review of jaw dislocation by Akinbami (2011) found trauma behind 60% of cases. MedlinePlus says a broken or dislocated jaw needs medical attention right away. A jaw stuck open is a reason to go to a hospital emergency department straight away.
Early evaluation and a targeted, movement-based approach may assist in maintaining jaw function and mobility. How a displaced disc is assessed is set out on the page about a slipped disc in the jaw.
Teeth Grinding (Bruxism): Sleep, Stress and the Jaw
Bruxism is repeated activity of the jaw muscles: clenching or grinding the teeth, or bracing or thrusting the lower jaw. An international consensus by Lobbezoo and colleagues (2018) separates sleep bruxism from awake bruxism. In otherwise healthy people, it treats bruxism as a behavior rather than a disorder.
Roughly one adult in ten has bruxism (Castrillon and colleagues, 2016).
Not everyone with bruxism needs care, as a review by Castrillon and colleagues (2016) points out.
Sleep Grinding and the Autonomic Nervous System
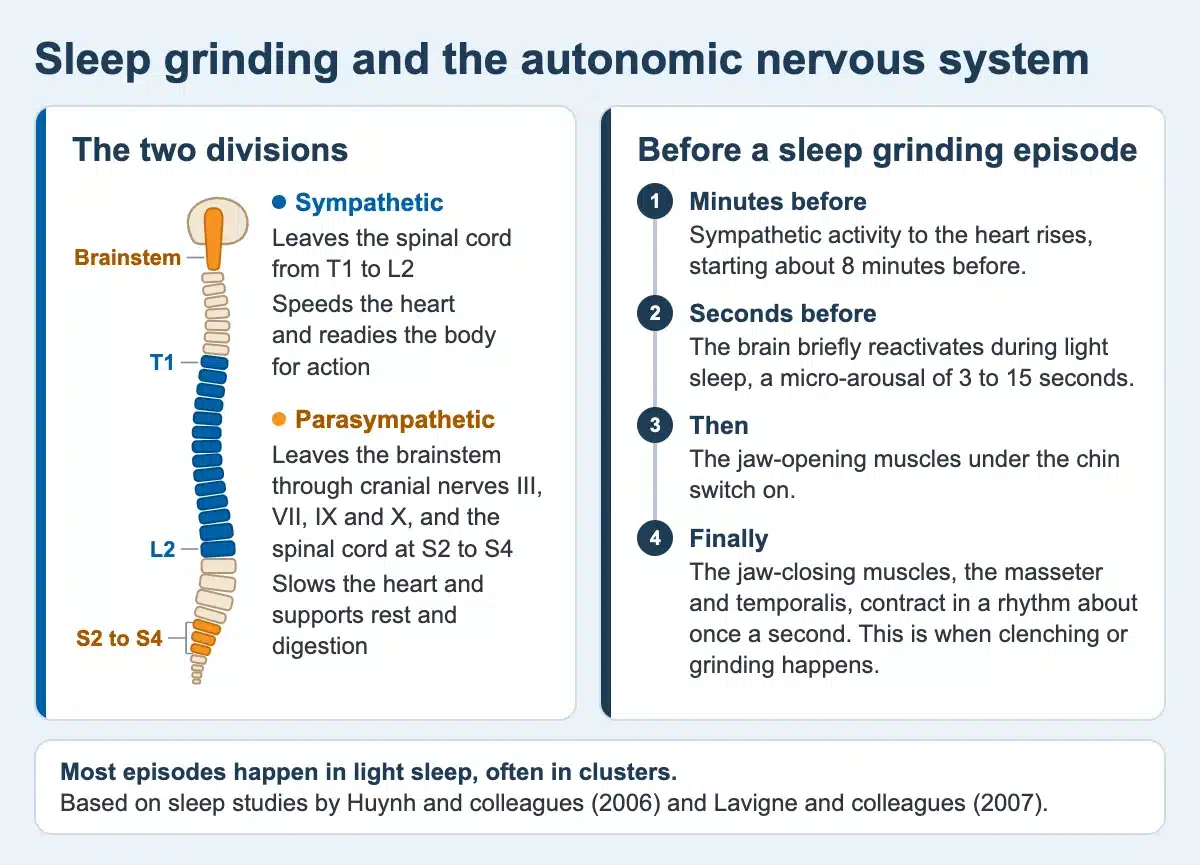
Sleep bruxism is closely tied to the autonomic nervous system. This is the part of the nervous system that runs the heart and other organs without conscious effort. Most episodes come in light sleep, often in clusters, during micro-arousals of 3 to 15 seconds.
Sleep studies by Lavigne and colleagues (2007) show a set order. The heart is activated first, minutes before. The brain follows in the seconds before. Then the jaw-opening muscles under the chin switch on, and finally the masseter and temporalis contract about once a second.
Huynh and colleagues (2006) studied people who grind moderately to heavily. Sympathetic activity to the heart, the nerve signals that speed it up, began rising 8 minutes before an episode. The sympathetic nerves do not move the jaw muscles themselves. The same arousal speeds the heart and switches on the jaw muscles through the trigeminal nerve, which works the chewing muscles.
The sympathetic nerves leave the spinal cord from T1 to L2, from the upper back to the top of the lower back. The parasympathetic nerves leave the brainstem and the base of the spine at S2 to S4. For this reason, our founder's examination of a person with bruxism includes the upper neck, the upper back and the base of the spine.
Stress matters too. A review by Kato and colleagues (2001) describes sleep bruxism as a microarousal event. It notes that the added effect of psychosocial stress cannot be overlooked.
Clenching or Grinding: How Each Loads the Joint
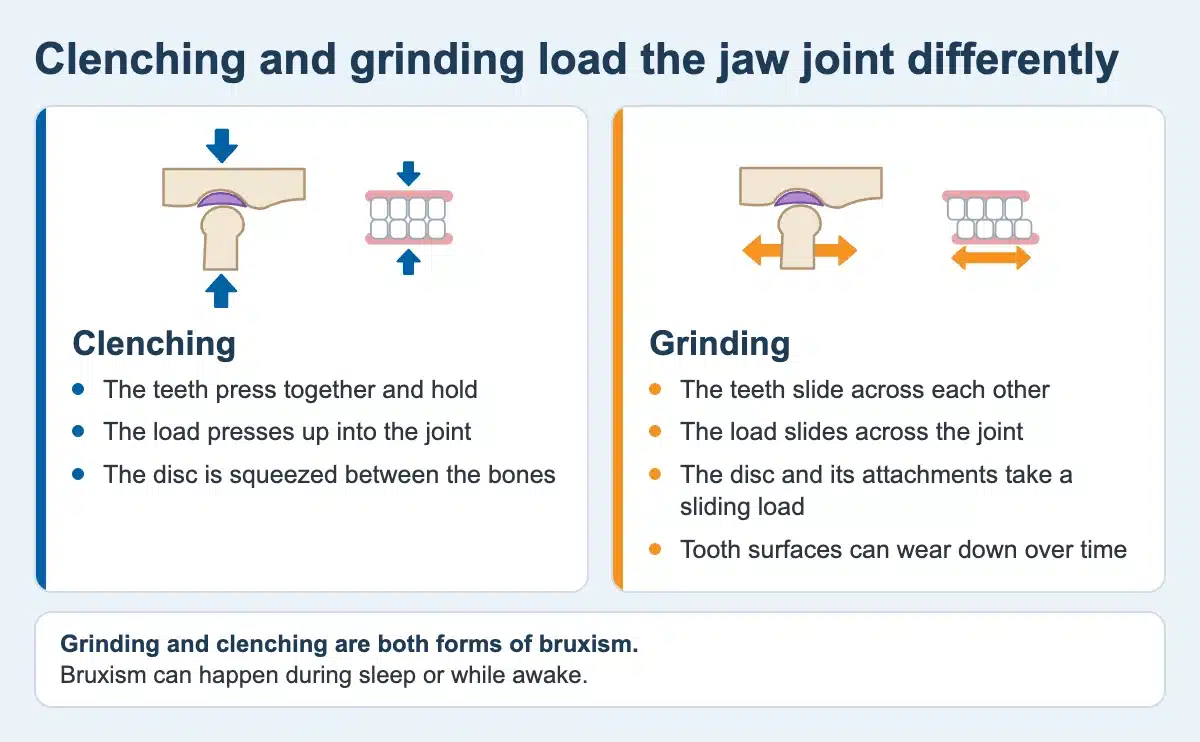
Clenching presses the teeth together and holds the load, so the disc is squeezed between the bones. Grinding slides the teeth across each other under load, so the disc and its attachments take a sliding load. Over time, grinding can also wear down the tooth surfaces. Both are forms of bruxism, and both can happen during sleep or while awake.
A 2023 review of 20 studies by Mortazavi and colleagues found that bruxism raised the odds of TMD 2.25 times. The odds were 2.51 times for awake bruxism and 2.06 times for sleep bruxism.
Night Guards: What They Do and Where They Fit
A night guard is often the first step for bruxism, and a dentist makes it. It fits over the teeth and keeps them apart during sleep. It protects the teeth and lessens the stress on the jaw joints. Kato and colleagues (2001) likewise describe oral splints as useful to protect the teeth.
A dentist makes and fits the guard, and our founder discourages guards bought online. An anterior, forward-positioned guard may aid disc repositioning. A guard worn 24 hours a day is avoided unless there is a severe acute injury, such as a fractured jaw. Wearing a guard all day may further complicate recovery. A guard is never the only part of care.
For bruxism, TMJ physiotherapy at both Kuala Lumpur centers works on the masseter and temporalis, the muscles that clench and grind.
Jaw & Ear: Ringing, Fullness and Proposed Links
People with jaw problems often notice ear symptoms: ringing (tinnitus), a blocked or full feeling, or an ache in the ear. A 2025 review of 32 studies by De La Torre Canales and colleagues found tinnitus in 57.5% of people with TMD. It also found TMD in 92.9% of people with tinnitus.
The authors called the link strong, but said more research is needed to explain it. Effat (2016) studied 104 people with TMD and found that many had several ear symptoms. The author proposed a change in pressure balance between the middle and inner ear as a cause.
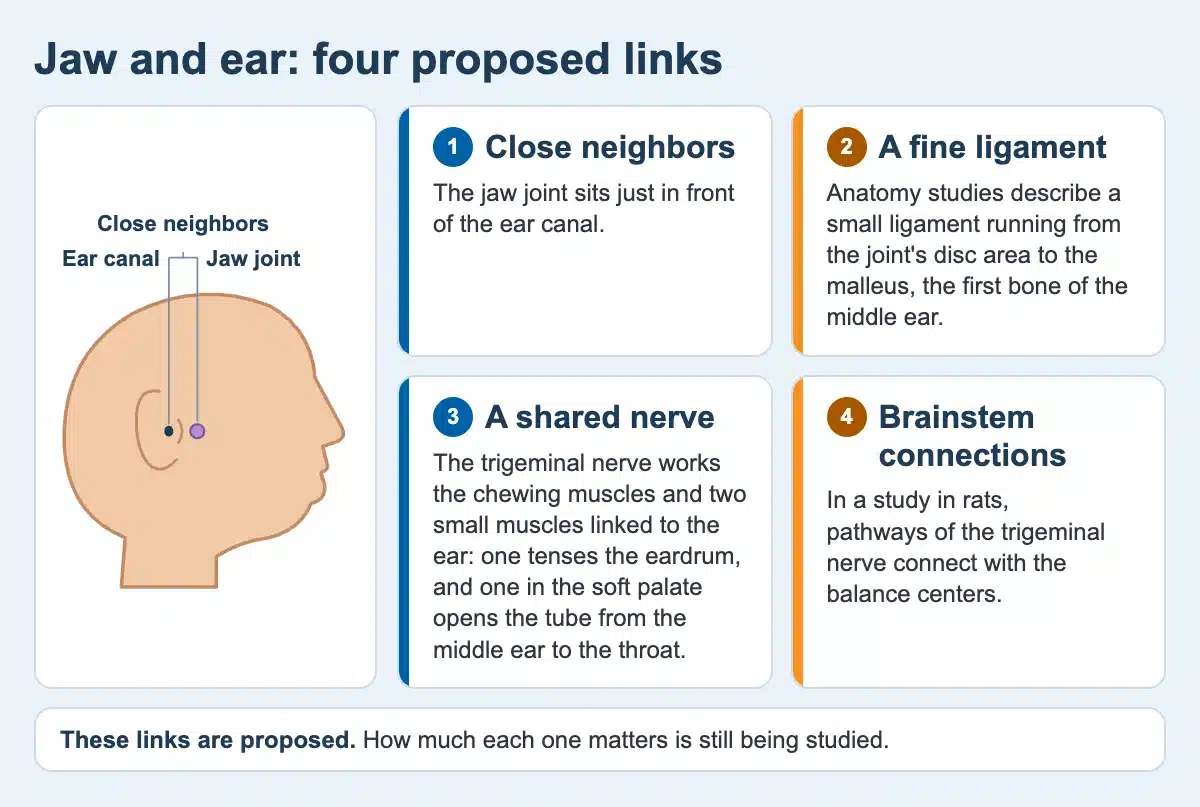
Four links between the jaw and the ear have been proposed:
- Close neighbors: the jaw joint lies just in front of the ear canal.
- A fine ligament: an anatomy study by Anastasi and colleagues (2020) traced a small ligament from the joint's disc area to the malleus. The malleus is the first bone of the middle ear. The authors proposed that tension from a jaw problem could reach the eardrum.
- A shared nerve: the trigeminal nerve works the chewing muscles and two small muscles linked to the ear. One tenses the eardrum, and the other, in the soft palate, opens the tube from the middle ear to the throat.
- Brainstem connections: in rats, Buisseret-Delmas and colleagues (1999) traced pathways between the trigeminal nerve centers and the balance centers. Those balance centers also receive signals from the neck.
At CSC, the jaw and neck are assessed in people who also have tinnitus. The assessment covers the jaw and the neck. Ear problems are for a doctor or an audiologist to diagnose and treat. The page on ear ringing and when to get checked lists the signs that need a doctor first.
TMD Assessment: What the First Visit Covers
There are many different forms of jaw or TMJ disorder, and the first thing the examination does is work out which type is present. At the first visit, the questions cover everything that loads the jaw and the neck:
- Neck stiffness or neck pain.
- Grinding or clenching the teeth, and whether a partner or family member has noticed it.
- Resting the chin on one hand: a critical question.
- Hard foods and very wide yawns.
- Any ringing or fullness in the ears, dizziness, headaches or migraines, and any eye problems.
- What makes the jaw worse, and what makes it better.
The examination then follows the chain from the jaw to the chest:
- Jaw movement: opening, closing, side to side, clicking and drift to one side.
- Muscles and ligaments by touch: the temporalis, the masseter, the muscles under the skull and the sternocleidomastoid (SCM).
- The whole neck: C1 to C3, then the middle and lower neck.
- The upper chest and shoulder: the collarbone and rib joints at the breastbone, and the subclavius muscle under the collarbone.
- Scans and reports: reviewed, with imaging advised where it is needed.
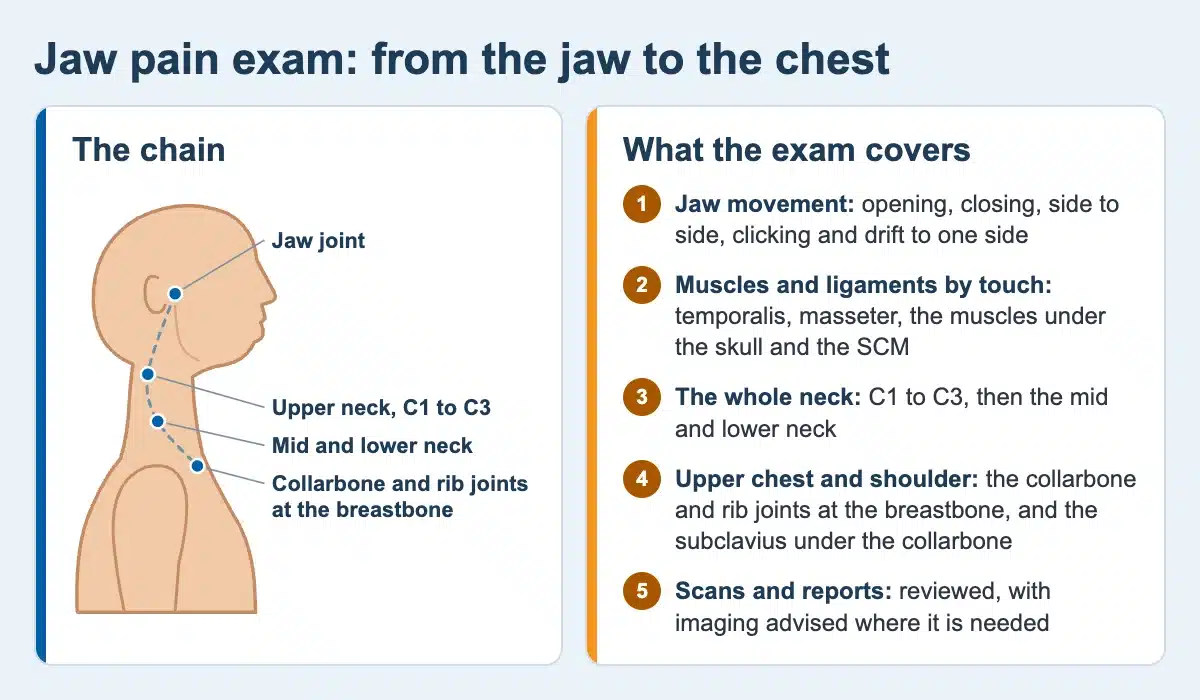
Our founder, Yama Zafer, D.C., describes the upper neck and the jaw in his own words: "None of these things are a standalone. When one goes, the other goes, much like a kinematic chain." A chronic upper neck problem can lead to jaw problems, and the reverse is true too.
The assessment covers the neck, jaw mechanics and alignment, habits, posture and muscle balance. Jaw pain treatment then targets the causes found, not only the symptoms. Whatever the cause of the pain, the examination findings are what shape the plan. Chewing, speaking, and jaw opening are tracked as the plan is reviewed.
How Jaw Pain Is Treated: Upper Neck First
Jaw pain treatment at CSC puts the upper neck first, with chiropractic and physiotherapy methods for joint alignment, soft tissue mobility and muscle coordination. Jaw pain and TMJ-related mobility concerns may be addressed through structured, non-invasive care. At Chiropractic Specialty Center (CSC), our clinical teams integrate both approaches to support jaw mobility and function. Our structured approach focuses on:
- Joint function and alignment support.
- Soft tissue mobility strategies.
- Non-invasive movement-based care.
Our approach is tailored to your needs, focusing on precision and on how the jaw actually moves. Through a combination of chiropractic care, physiotherapy, and targeted rehabilitation, we work on muscle tension, jaw alignment and long-term function.
Upper Cervical Care at C1 Comes First
In the care plan, upper cervical care at C1 comes first in importance. Our founder, Yama Zafer, D.C., often sees the jaw problem peak together with a C1 problem on the same side. For that reason, the top of the neck is cared for alongside chiropractic, physiotherapy and jaw exercises.
C1 is adjusted with a non-force contact on its lateral mass, using the slightest pressure at an angle set by each person's needs. Care stays within what the person can comfortably tolerate, with just a gentle pressure along the atlas. Alongside C1, the jaw, the lower neck and the rib joints at the spine and breastbone are adjusted where needed.
An Activator, a small hand-held adjusting instrument, may be used at its lowest setting, level one, cushioned, when the neck is stable. It is used on the soft tissues near the lateral mass, not on the lateral mass itself. If the neck proves unstable, the next choice is the non-force method.
TMJ and Jaw Pain Treatment by the Chiropractor
For individuals seeking non-surgical approaches for jaw mobility concerns, a combination of chiropractic and physiotherapy-based methods may provide support. Targeted chiropractic techniques that prioritize non-rotational, controlled movements may help support TMJ function and stability.
- Chiropractic care focuses on joint function and alignment, with movement support from a Doctor of Chiropractic.
- Physiotherapy-based strategies target muscular coordination and soft tissue mobility.
- Targeted soft tissue mobility strategies support both.
Putting a slipped jaw disc back in place is a complex process. The ligaments around the joint that hold the disc are weak as well. Many things must be in place, including a custom night guard from a dentist. Care adds therapeutic ultrasound, myofascial release and very specific manual work on the jaw joint. Over time, these are used to support the disc's position.
The jaw joint is a difficult joint to reach. Its outer edges, part of its back and, to a small degree, its front are easier to work on than its inner side. When the damage lies mainly on the inner side, full or even partial recovery may not be possible.
Each case is judged on its own, and the response to care is often the clearest indicator. Progress is reviewed after three to five sessions, and the advice that follows depends on how the jaw responds. At CSC, our team utilizes structured, research-based movement strategies to assist in jaw function support and recovery.
At CSC, people are referred to a dentist only when a night guard is needed.
TMJ and Jaw Pain Physiotherapy
TMJ physiotherapy works on the muscles and soft tissues around the jaw joint and the upper neck. Physiotherapy-based strategies, including soft tissue mobility support and neuromuscular re-education, further aid in optimizing jaw movement patterns. Our physiotherapists work with the chiropractors on one plan. Methods of TMJ physiotherapy may include:
- Therapeutic ultrasound over both jaw joints, the SCM and the upper neck.
- Laser over the upper neck.
- Shockwave for the trapezius.
- Electrotherapy, such as interferential current (IFC) or TENS (mild pulses through pads on the skin).
- Jaw exercises and posture work.
A structured, non-invasive approach focusing on joint mechanics, postural alignment, and neuromuscular rehabilitation can assist jaw movement without an invasive procedure. For individuals experiencing jaw mobility concerns, a collaborative movement strategy may assist in long-term function support.
By integrating chiropractic and physiotherapy-based methods, individuals can pursue non-invasive strategies to support TMJ function and improve mobility, with surgery kept as a last resort. For our founder, conservative care means focused care, planned from the imaging and examination findings, with every method aimed at what was found.
The most important thing for a person with jaw pain is patience: care takes time, and there are no magic bullets. CSC does not prescribe medicine, so a GP is the person to ask about it.
Signs That Need Medical Care First
Some jaw symptoms need a hospital or a doctor before any other care:
- A jaw stuck open that will not close: go to a hospital emergency department straight away.
- A jaw injury after a fall, a punch or an accident, where the jaw may be fractured: go to a hospital emergency department first.
- Jaw pain with signs of a heart attack: call 999 straight away.
- Jaw pain that comes on with chewing or talking, a sudden headache at the temples, or any change in vision: see a doctor immediately.
According to the NHS (reviewed March 2026), the signs of a heart attack are:
- Chest pain that may feel like crushing or squeezing, which may spread to the arm, neck and jaw.
- Feeling short of breath.
- Feeling sick (nausea) or being sick (vomiting).
- Feeling like you have indigestion, with a burning feeling in the chest, or feeling full or bloated.
- Sweating.
- Pale, blue or gray skin; on black or brown skin, this may be easier to see on the palms of the hands.
The NHS says to call 999 for any of these:
- Chest pain that feels tight or like squeezing.
- Chest pain that spreads to the arms, neck or jaw.
- Severe difficulty breathing.
- Lips or skin that look pale, blue or gray.
- Someone who has passed out and is not responding normally.
In a 2020 paper, Kreiner and colleagues report that 4 in 10 people with reduced heart blood flow feel face or jaw pain. In up to 4% of heart attacks, pain was felt only in the face or jaw, in women more often than men. Jaw pain with any of these heart attack signs needs a call to 999 straight away.
Giant cell arteritis (GCA) has three main signs. They are jaw pain with chewing or talking, a sudden headache at the front or side of the head, and vision problems. Vision problems include reduced or lost vision in one or both eyes, or double vision. NHS-based guidance from nidirect says GCA needs urgent treatment. Its other signs are a mild fever of 37 to 38°C, extreme tiredness, loss of appetite, weight loss and depression. For any of the three main signs, nidirect advises contacting a doctor immediately.
How Much Does Jaw Pain Treatment Cost in KL?
At CSC, the examination is RM100 for a new or returning patient (CSC quotation dated June 25, 2026). A chiropractic adjustment is RM150, or from RM110 when physiotherapy is part of the same visit. A physiotherapy unit is RM57 to RM180, or RM27 to RM150 when chiropractic is part of the same visit.
What the assessment finds, which methods are used and the number of visits in the plan decide the total. Payment can be made by cash, credit card, bank transfer, on-line deposits or guarantee letters.
The fee for a plan is explained and agreed before care begins. The chiropractic fees are listed item by item on the chiropractic prices in Kuala Lumpur page, and the physiotherapy fees on the physiotherapy prices in Kuala Lumpur page.
Further Reading: Clicking, Disorders and the Upper Neck
If you would like to keep reading, several topics are closely related. They include TMJ disorders and jaw clicking, temporomandibular joint dysfunction, what a jaw chiropractor assesses and the joints of the upper neck. Jaw problems in children have their own section on this page.
Jaw Joint Guides
- TMJ Disorders: Jaw Clicking, Stiffness and Assessment
- Temporomandibular Joint Dysfunction Care By Jaw Experts
- Slipped Disc in the Jaw: TMJ Displacement, Causes & Care Options
- Jaw Chiropractor in KL: TMJ Care Guide
- TMJ Treatment in Malaysia: How Options Are Decided
- Jaw and TMD in Malaysia: Non-Invasive Care Options
- Causes of TMJ Pain: Jaw Concerns You Should Know
Questions About Jaw Pain Treatment
What is the difference between TMJ and TMD?
Should I see a dentist or a chiropractor for jaw pain?
What can I do at home for jaw pain?
Does jaw treatment hurt?
Is jaw surgery ever needed?
Are Botox or steroid injections used for jaw pain?
What is jaw pain called in Malay?
Can jaw pain cause headaches?
Why get jaw pain checked early?
What is jaw claudication?
Can a chiropractor help with TMJ problems?
This page is general information and does not replace an examination by a qualified practitioner.
Medical References
- Fernández-de-las-Peñas C, Simons D, Cuadrado ML, Pareja J. The role of myofascial trigger points in musculoskeletal pain syndromes of the head and neck. Curr Pain Headache Rep. 2007;11(5):365-372.
- American Academy of Orofacial Pain; Klasser GD, Romero-Reyes M, eds. Orofacial Pain: Guidelines for Assessment, Diagnosis, and Management. 7th ed. Batavia, IL: Quintessence Publishing; 2023.
- McCarty WL, Lankford CD. Chiropractic management of temporomandibular disorders. J Manipulative Physiol Ther. 2001;24(1):30-37.
- Wright EF. Manual therapy for temporomandibular disorders. J Man Manip Ther. 2007;15(1):27-37.
- Dijkstra PU, de Bont LG, de Leeuw R, Stegenga B, Boering G. Temporomandibular joint osteoarthrosis and temporomandibular joint hypermobility. Cranio. 1993;11(4):268-275.
- Liberato FM, da Silva TV, Santuzzi CH, Ferreira Fachini de Oliveira N, Nascimento LR. Manual therapy applied to the cervical joint reduces pain and improves jaw function in individuals with temporomandibular disorders: a systematic review on manual therapy for orofacial disorders. J Oral Facial Pain Headache. 2023;37(2):101-111.
- La Touche R, Fernández-de-las-Peñas C, Fernández-Carnero J, et al. The effects of manual therapy and exercise directed at the cervical spine on pain and pressure pain sensitivity in patients with myofascial temporomandibular disorders. J Oral Rehabil. 2009;36(9):644-652.
- Grondin F, Hall T, Laurentjoye M, Ella B. Upper cervical range of motion is impaired in patients with temporomandibular disorders. Cranio. 2015;33(2):91-99.
- Silveira A, Gadotti IC, Armijo-Olivo S, Biasotto-Gonzalez DA, Magee D. Jaw dysfunction is associated with neck disability and muscle tenderness in subjects with and without chronic temporomandibular disorders. Biomed Res Int. 2015;2015:512792.
- Armijo-Olivo S, Magee D. Cervical musculoskeletal impairments and temporomandibular disorders. J Oral Maxillofac Res. 2013;3(4):e4.
- Huang GJ, Rue TC. Third-molar extraction as a risk factor for temporomandibular disorder. J Am Dent Assoc. 2006;137(11):1547-1554.
- Kalaykova S, Lobbezoo F, Naeije M. Two-year natural course of anterior disc displacement with reduction. J Orofac Pain. 2010;24(4):373-378.
- Lobbezoo F, Ahlberg J, Raphael KG, et al. International consensus on the assessment of bruxism: report of a work in progress. J Oral Rehabil. 2018;45(11):837-844.
- Castrillon EE, Ou KL, Wang K, Zhang J, Zhou X, Svensson P. Sleep bruxism: an updated review of an old problem. Acta Odontol Scand. 2016;74(5):328-334.
- Lavigne GJ, Huynh N, Kato T, et al. Genesis of sleep bruxism: motor and autonomic-cardiac interactions. Arch Oral Biol. 2007;52(4):381-384.
- Huynh N, Kato T, Rompré PH, et al. Sleep bruxism is associated to micro-arousals and an increase in cardiac sympathetic activity. J Sleep Res. 2006;15(3):339-346.
- Kato T, Thie NM, Montplaisir JY, Lavigne GJ. Bruxism and orofacial movements during sleep. Dent Clin North Am. 2001;45(4):657-684.
- Mortazavi N, Tabatabaei AH, Mohammadi M, Rajabi A. Is bruxism associated with temporomandibular joint disorders? A systematic review and meta-analysis. Evid Based Dent. 2023;24(3):144.
- De La Torre Canales G, Christidis N, Grigoriadis A, et al. Associations between temporomandibular disorders and tinnitus - a systematic review. Cranio. 2025;43(6):969-985.
- Effat KG. Otological symptoms and audiometric findings in patients with temporomandibular disorders: Costen's syndrome revisited. J Laryngol Otol. 2016;130(12):1137-1141.
- Anastasi MR, Rizzo G, Nicita F, et al. Microscopic reconstruction and immunohistochemical analysis of discomalleolar ligament. Heliyon. 2020;6(8):e04651.
- Buisseret-Delmas C, Compoint C, Delfini C, Buisseret P. Organisation of reciprocal connections between trigeminal and vestibular nuclei in the rat. J Comp Neurol. 1999;409(1):153-168.
- Kreiner M, Okeson J, Tanco V, Waldenström A, Isberg A. Orofacial pain and toothache as the sole symptom of an acute myocardial infarction entails a major risk of misdiagnosis and death. J Oral Facial Pain Headache. 2020;34(1):53-60.
- NHS. Heart attack: symptoms. Reviewed March 31, 2026.
- nidirect (adapted from NHS content). Giant cell arteritis.
- Ameer MA, Vaqar S, Savadkar A, Khazaeni B. Giant cell arteritis (temporal arteritis). StatPearls. Treasure Island, FL: StatPearls Publishing; 2024. NBK459376.
- MedlinePlus Medical Encyclopedia. Broken or dislocated jaw. Reviewed April 3, 2025.
- Schiffman EL, Look JO, Hodges JS, et al. Randomized effectiveness study of four therapeutic strategies for TMJ closed lock. J Dent Res. 2007;86(1):58-63.
- Raphael KG, Tadinada A, Bradshaw JM, et al. Osteopenic consequences of botulinum toxin injections in the masticatory muscles: a pilot study. J Oral Rehabil. 2014;41(8):555-563.
These references describe jaw and TMJ problems and their care in general. None of them evaluates care at Chiropractic Specialty Center.
The Author of Jaw Pain Treatment in KL: TMJ Signs, Symptoms, Causes
Jaw Pain Treatment in KL: TMJ Signs, Symptoms, Causes was written by Yama Zafer, D.C., who has 30+ years in chiropractic and physiotherapy and founded Chiropractic Specialty Center in Kuala Lumpur in 2006.
Last Updated: Jaw Pain Treatment in Kuala Lumpur: TMJ and TMD Care
Jaw Pain Treatment in Kuala Lumpur: TMJ and TMD Care was last reviewed and updated on October 25, 2026.