


Slip Disc Treatment in Kuala Lumpur, Matched to Each Stage
The right slip disc treatment for you depends on three things: the stage the disc has reached, the level it sits at, and you. A bulge at L4-L5 in a 30-year-old office worker is called a slipped disc. So is a fragment at C5-C6 in a 70-year-old, yet the two need very different plans.
Treatment is used when a damaged disc causes neck or back pain, or pain or numbness that spreads into an arm or a leg. The aim is to lower the pressure inside the disc and calm the tissues around it, then rebuild the muscles that support the spine. I combine non-rotatory chiropractic care, flexion-distraction, spinal decompression and high-intensity laser to do it. It suits people of any age, and the plan is made lighter for an older spine. The sections below cover laser, physiotherapy and exercise, daily habits, each spinal level, when surgery fits and how to choose a provider.
For more information about slip disc treatment, contact the Bukit Damansara (KL) main center: WhatsApp+60 17 269 1873 Call+603 2093 1000
Slip Disc Treatment: Key Takeaways
| Question | My short answer |
|---|---|
| Do I need an X-ray or an MRI? | An examination comes first, and not everyone needs a scan. When the findings point to a disc, an MRI shows its stage and the nerves. X-rays show bone alone, so I keep them for alignment, a slipped vertebra or a possible fracture. |
| Can it be treated without surgery? | In my view, every stage short of a sequestered disc can be cared for with focused conservative care. A partly fragmented disc qualifies only after a thorough assessment and with no warning signs. |
| Is physiotherapy part of the plan? | Yes, from the start. Physiotherapy begins with gentle care for the disc and the tissues around it. Strengthening follows once the spine is stable, and the program is reviewed every three to six months. |
| Does the spinal level change the care? | Yes. A neck disc can press on the spinal cord, so I test the legs as well as the arms. A mid-back disc often needs a scan of the neck or the lower back too. |
| What do I leave out? | Twisting manipulation, forceful neck or back pulls, stretching and exercise in the early stage, heat on the spine, and yoga. Each of these can irritate a damaged disc further. |
| Is laser treatment surgery? | Not the kind I use. High-intensity laser works through the skin and should feel only mildly warm. Laser disc decompression is a separate, invasive procedure carried out inside the disc. |
| When does exercise begin? | Once the spine is stable, usually two to six weeks into care. For a disc in the lower back, Kegel exercises can start at once, and every other exercise is chosen for the person. |
| When is surgery considered? | After focused care has been given properly without success, or in severe cases such as a sequestered disc. New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours. |
| What does it cost? | At CSC, the examination is RM100. Each chiropractic adjustment costs RM150, or RM110 in a visit that also includes physiotherapy (CSC quotation dated June 25, 2026). |
Why Slipped Disc Treatment Is Not Routine Back Care
Slip disc treatment differs from routine neck or back care because a damaged disc is rarely the only problem. In my experience, a disc that slips has a history behind it. The muscles, ligaments and joints around it were strained first, and the nerves beside it are often irritated. The disc is usually the last part to show its damage. Treating only the sore muscle, or only the stiff joint, leaves the rest of that history in place.
Depth matters as well. A spinal disc lies 6 to 10 centimeters beneath the skin, a fact my video Is Chiropractic Safe? 13 Questions Answered stresses. So I do not expect a manipulation alone to take care of it. That is why I combine methods. Nothing I do pushes a disc back into place, and I plan care with that in mind.
By conservative care I mean something specific. It is care built on what the examination and the scans document, directed at the causes they reveal. It covers the whole spine, and it is never harmful. Routine neck or back treatment is not that, and many forms of it achieve little for a damaged disc. I consider surgery only after this kind of focused care has been carried out properly without success.
My guide to what a slip disc is and its eight stages explains the condition itself; this page is about treating it. The methods below come together in NSD Therapy®, the program I first created in 2006, the year I founded Chiropractic Specialty Center. There, chiropractors and physiotherapists work side by side, and both Kuala Lumpur centers carry the full range of equipment these methods need.
X-Ray or MRI Before Slipped Disc Treatment?
For a suspected slip disc, an MRI is the scan I rely on, and an X-ray answers only certain questions about the bones. Neither comes first, though. I start with your history and an examination: how the spine moves, orthopedic tests, and the strength, sensation and reflexes of your arms or legs. Not everyone needs imaging, and I order it only when the findings call for it.
An MRI shows what an X-ray cannot: the disc, the nerves and the space they have, along with the bones, joints, muscles and ligaments. It uses no radiation. When a disc is suspected, it is my first choice, because it shows the stage, and the stage decides which methods suit you. My page on what an MRI scan involves and how to prepare covers the scan itself.
An X-ray shows only bone. I use one when the question is about alignment, a vertebra that has slipped forward (spondylolisthesis), facet joint wear or a possible compression fracture. Where a vertebra has slipped, X-rays taken bending forward and backward show whether the segment is stable. After that, an MRI shows what it is doing to the discs and nerves. Full-spine X-rays I keep for scoliosis.
I read the images themselves, not only the report. On a degenerated disc, the scan cannot separate the center from the outer rings. The report then often falls back on the disc's outline and calls it a bulge. The scan is also taken lying flat, usually after the disc has rested. Upright and loaded, the same disc can push further out, which I describe as a bulge in transition.
No single finding settles where pain comes from. A 2007 review of the tests used to find it showed that some MRI features make the disc a more likely source. So does pain that retreats toward the spine during testing, called centralization. Yet each shifts the odds only modestly (Hancock and colleagues, 2007). So I weigh the images with the examination. If you already have scans, bring the images on CD or film together with their reports.
Arranging a Disc Assessment at a KL Center
The first visit checks how your spine moves and how the nerves to your arms or legs work, and reads any scans you bring. Either Kuala Lumpur center can arrange it before a slip disc treatment plan is set:
- Bukit Damansara (KL, main center): Call +603 2093 1000 or WhatsApp +60 17 269 1873 to see the Bukit Damansara / KL center.
- Bandar Sri Damansara (KL): Call +603 6262 5777 or WhatsApp +60 12 455 6939 to see the Bandar Sri Damansara center.
You will find directions and opening hours on the contact page or the pages of the Bukit Damansara and Bandar Sri Damansara centers. The two centers serve readers in and around Bukit Damansara, Damansara Heights, Bangsar, Mont Kiara, TTDI, Bandar Sri Damansara, Kepong, Desa ParkCity and Sungai Buloh.
Slip Disc Treatment by Stage
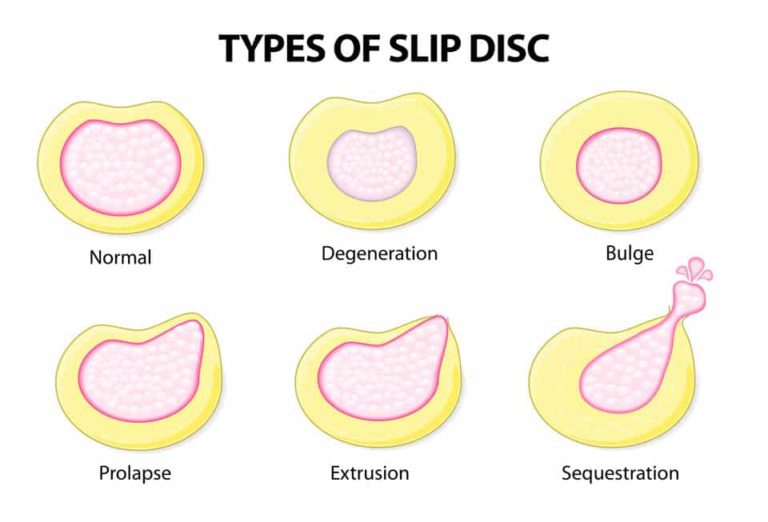
The stage a disc has reached changes what I do more than anything else. I describe the damage as eight stages, each a step on from the one before, and the table shows how treatment shifts along the way. Damage can move through the stages in days or over years, and a report can understate the stage. So the examination counts as much as the label. How the damage begins, from long sitting to lifting, is on my page on the causes of a herniated disc.
| Stage | How I set treatment |
|---|---|
| Degenerated disc | The disc has dried and weakened but has not moved. Care centers on load: sitting, sleep and lifting habits, and gentle decompression to lower the pressure inside the disc. The facet joints are checked too, since a thinning disc overloads them. |
| Bulge | The fibers have swollen, but no nerve is touched. I am never aggressive, even with the slightest bulge, and start with gentle, non-rotatory methods aimed at the disc, manual or machine-based. Symptoms after sitting or driving make me look for a bulge in transition. |
| Protrusion | The center has shifted toward the spinal canal but is still held. Decompression and flexion-distraction come in, stretching stays out, and sitting time is cut down. |
| Prolapse | The center has pushed almost through, held back by only a few outer fibers, and the nerves may now be reached. The same gentle methods continue, with closer checks of nerve strength and sensation at each review. |
| Herniation, or rupture | The outer rings have torn, and the disc is no longer contained. Twisting is ruled out, stretching waits, and with an acutely inflamed disc I start no exercise program sooner than three weeks. |
| Extrusion | A large herniation, with the center pushed to the edge of the disc and beyond. It calls for a prompt assessment, yet surgery is not automatic, and focused conservative care can still be the plan. |
| Partial fragment | Part of the center has broken off. Focused conservative care is possible only after a thorough assessment, and an experienced clinician must deliver it precisely. It also requires no change in bladder or bowel control and no numbness in the genital or anal area. |
| Sequestration | The fragment has torn away completely and lies free in the spinal canal. A sequestered disc, sometimes called a fully fragmented disc, is a severe case in which surgery is considered, and I discuss referral with you. |
Which Slipped Discs Can Be Treated Without Surgery?
In my view, every stage of slip disc up to a partly fragmented disc can be cared for without surgery. That holds as long as the care is focused and the warning signs described further down are absent. The exception is a sequestered disc, where the fragment has torn free and an operation has to be weighed. Within that rule, how a disc behaves depends a great deal on what came with it.
A slipped disc seldom comes alone. These are the conditions I most often find beside it, and they are cared for at the same time as the disc:
- thickening of the ligamentum flavum, the elastic ligament inside the spinal canal
- facet hypertrophy, enlarged facet joints at the same levels
- spondylosis, the wider wear explained in how a slipped disc and spondylosis differ
- spondylolisthesis, a vertebra that has slipped forward
- arthritis and bone spurs
- degenerated discs at other levels
- moderate to severe scoliosis
- spinal stenosis, a narrowed canal
Each one changes the slip disc treatment plan. An older spine with stenosis or arthritis gets a gentler approach. Decompression is shorter and lighter, hands-on work is gentler, stretching is held back for longer, and balance and stability training increases. With spondylolisthesis, the psoas stretch is left out altogether.
Video: Why Spinal Discs Get Damaged
In this two-minute video I show how a healthy disc holds its center in place and how daily load wears its fibers down. I also show how a bulge goes on to become a herniation. Seeing that path explains why slip disc treatment changes from one stage to the next.
Key moments and an edited transcript of this video are on our Why Spinal Discs Get Damaged video page.
Key Moments of the video:
- 00:00 Structure of a healthy spinal disc
- 00:17 How daily loading affects disc pressure
- 00:28 Early changes as disc fibers weaken
- 01:19 How bulges and herniations develop
- 01:35 Visual explanation of disc progression
- 01:46 Why disc changes may continue over time
Understanding how disc changes develop step by step helps explain why everyday movement and posture play an important role in spinal health.
Non-Rotatory Chiropractic Care for a Slipped Disc
Chiropractic care for a slip disc, as I practice it, avoids twisting. For a damaged disc, my method is chiropractic manipulation that is non-rotatory using the Activator instrument. It gives a light, precise impulse to a vertebra without turning the spine. Other chiropractic methods that suit a damaged disc are the sacro-occipital technique (SOT), the Thompson technique and flexion-distraction.
Rotary manipulation, the kind that twists the neck or the lower back until it cracks, has little place in my work with discs. I keep it for a spine I am 100% sure has no damaged disc. How rarely does that happen? Almost never, and I say so openly in my Back Pain to Leg Pain talk. A torn disc and a twisting thrust do not belong together.
Flexion-Distraction
Flexion-distraction is done on a table that bends the lower back gently forward while easing the segments apart. It moves in a slow rhythm, not a thrust. It aims to take load off an irritated disc and the nerve beside it, and with an older or narrowed spine I keep it lighter. The page on how flexion-distraction is performed shows the table and the technique.
In chronic low back pain generally, a review of 51 trials found moderate-quality evidence that manipulation and mobilization likely reduce pain and improve function. It also found that both appear safe (Coulter and colleagues, 2018). That review did not single out damaged discs, which is why, with a disc, I keep to the methods above. My guide on what a chiropractor checks and avoids with a slipped disc covers this side in depth. The pages on chiropractic adjustment and how the Activator instrument is used show the methods themselves.
Spinal Decompression: What It Aims to Do
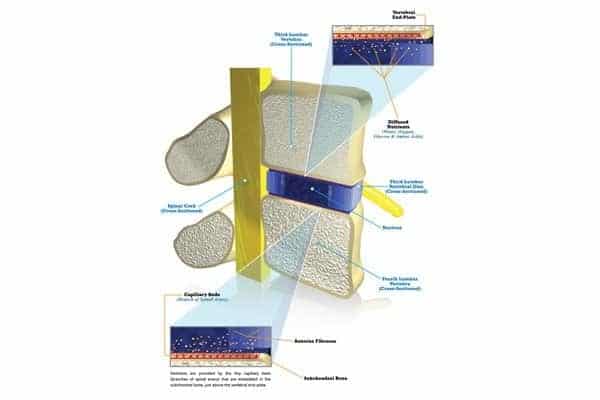
Spinal decompression is done on a motorized table that draws the spine gently apart and then lets it settle. This runs in cycles, at angles set for the level being treated. Its aim is to lower the pressure inside the disc. A disc has no blood supply of its own. It draws water and nutrients from the bone above and below it, most easily when the pressure inside it is low. That process is called imbibition.
Research on decompression is limited, and I would rather say so. In 1997, a small randomized study by the neurosurgeon Norman Shealy set a decompression table against standard traction in 39 people with low back pain. Among those with a ruptured disc on MRI, more rated their result good or excellent after decompression. The authors called their findings preliminary (Shealy and Borgmeyer, 1997).
A later study looked back at 30 people with a lumbar disc herniation who had six weeks of decompression. On CT scans, the average height of the disc rose from 7.5 to 8.8 mm, and pain scores fell. It had no comparison group, and its authors called for a randomized trial to confirm the result (Apfel and colleagues, 2010).
No table pushes a disc back into place. I use decompression as one part of slip disc treatment, often in the same visit as flexion-distraction and high-intensity laser. Sessions are lighter and shorter for older spines and narrowed canals. The page on what a spinal decompression session involves describes a session from start to finish.
Slip Disc Laser Treatment: HILT or an Operation?
Laser treatment for a slip disc can mean two very different things. The one I use is high-intensity laser therapy (HILT), a strong beam of light applied through the skin, with no needle and no incision. The other, laser disc decompression, is an invasive procedure in which laser energy is delivered inside the disc through the skin. It belongs with the surgical options.
Laser is not the same as a hot pack, and my Back Pain to Leg Pain talk explains why. A hot pack warms only the surface, and heat can feed inflammation. Laser light reaches deep into the tissue, and the warmth arises inside it. It should feel mildly warm, never hot. I use it on the disc area and the soft tissues around it, often in the same visit as decompression.
Two trials show what HILT has been measured to do around a lumbar disc. In one, 63 people with a lumbar disc protrusion had spinal decompression, with or without laser. After two weeks, the laser group had improved more in disability scores, forward bending and straight-leg raising. Pain scores did not differ significantly (Chen and colleagues, 2018).
In a 2026 trial, 40 adults aged 30 to 45 with an L4-L5 or L5-S1 herniation followed the same six-week exercise program. One group had real laser and the other a sham. The real laser group showed larger reductions in pain and disability scores and in the herniation's measurements on MRI (Mohammed and colleagues, 2026). Both trials were small, and a 2026 review of laser treatments judged the evidence on disc size still limited (Kamath and colleagues, 2026).
Laser disc decompression has been tested against standard surgery. In a trial of 115 surgical candidates with sciatica, outcomes after two years did not differ meaningfully. But 52% of the laser group needed a further operation, against 21% after microdiscectomy (Brouwer and colleagues, 2017). It is not something I offer; that decision belongs with a spine surgeon. The page on what a high-intensity laser session involves covers HILT in full.
Shockwave, Ultrasound and Other Methods Around the Disc
A damaged disc draws the muscles, ligaments and joints around it into the problem, and those tissues get their own care. In slip disc treatment, these methods support the work on the disc rather than replace it:
- Shockwave therapy, used only when needed, for muscles that tighten around a lower back disc, such as the piriformis. It also suits the soft tissues at the back of the pelvis.
- Therapeutic ultrasound, for scar tissue and adhesions in the ligaments around the facet joints. In my experience, these are common once a neck or back problem has lasted.
- Electrotherapy such as interferential current, used for pain management.
- Cold therapy. The cryotherapy machine I use can also heat, but with a damaged disc or an irritated facet joint, only its cold setting touches the spine.
- Trigger point and myofascial work, always gentle, since tensing against pressure works against it. Pressing hard on the spine itself is left out while the disc is irritated.
None of these should go beyond what you can comfortably tolerate, so tell the clinician straight away if anything hurts. As my motto goes, no pain, more gain. At home, cold plays the same part. Wrap a cold pack in cloth and hold it in place 10 to 15 minutes at a time, twice or three times daily. Leave at least two hours in between.
Physiotherapy and Exercise for a Slip Disc
Physiotherapy is half of slip disc treatment, not an extra, and in every plan I set, the two professions work side by side. Physiotherapy for a disc has to be specific, though. General stretching and strengthening started too early can tear an injured disc further, so the timing matters as much as the exercises.
Exercise begins only when the spine is stable enough to take it. For most people that is two to six weeks into care, three to five on average. With an acutely inflamed herniated disc, I wait at least three weeks. Kegel exercises are the exception. For anyone with a lower back problem, herniations included, they can start at once. In my view, they put neither the disc nor its stability at risk.
The first exercises are the ones that load the disc least:
- Kegel exercises, which strengthen the pelvic floor
- tightening and relaxing the buttock muscles
- leg raises lying on the side, moving the leg out, in and forward
- core canister breathing
Once the spine is stable, wall-assisted squats, cat and camel, and strengthening of the buttocks, hamstrings, calves and thighs follow, matched to the severity. Research backs the timing. A Cochrane review of 61 trials found exercise slightly effective for chronic low back pain. In acute low back pain, it was no more effective than no treatment or other conservative care (Hayden and colleagues, 2005).
Later, rehabilitation on the Spinercise® exercise system trains the deep muscles that steady the spine through guided ranges of movement. Every three to six months the program is reviewed and changed. Nothing is a standard procedure: a herniated disc almost always comes with other conditions, and each program is built around them.
The gym waits. I discourage it at first and advise against free weights for two to six months. Deadlifts and leg presses stay out even after that. Machines such as leg curls and extensions, adductor and abductor machines, light rowing and lat pulldowns can return once the spine is stable. On a treadmill, walk at zero incline. My article on why free weights and deadlifts strain a disc explains the reasons. Yoga I leave out entirely, because with a slip disc it must be avoided.
Daily Habits While the Disc Is Being Treated
Slip disc treatment fills a small part of your day. My time with you runs from 30 minutes to two hours. In my Back Pain to Leg Pain talk I ask people about the other 22 hours, because those hours decide a great deal. While a disc is being treated, these habits matter most:
- Sitting: with back pain, rise for a short walk, 30 seconds to a minute long, every 15 to 20 minutes. Without back pain, once every 30 to 40 minutes will do.
- Driving: with acute, intense back pain, keep each stretch at the wheel to about 15 minutes, never beyond 20 to 30 minutes without stopping. Stop only where it is safe.
- Lifting: none while the disc is active, and under 2 kg when it cannot be avoided.
- Bending and twisting at the waist: as close to none as you can manage.
- Sleep: at least six hours, ideally seven to eight unbroken. Sleep on your side with the spine kept in one line, or on your back with a bolster beneath the knees.
- Heat: no hot packs on the spine; use cold instead.
Habits are what people most often drop once they feel better. The time to change them is while you are hurting, a point I make in my Neck and Back Self-Help Tips video. The first video below shows the sitting, sleeping and standing positions, and the second explains how posture loads the spine. My page on the home measures that help a slipped disc and those that set it back goes further.
The chapters and an edited transcript of this video are on the Neck and Back Self-Help Tips video page.
Key Moments of the video:
- 00:00 Why sitting habits affect the body
- 00:30 Sitting posture and breathing space
- 01:35 Slouching and pressure on the stomach and diaphragm
- 02:29 A better sitting setup for hips, knees, feet and screen
- 03:57 Sleep positions and spinal alignment
- 05:28 Standing and walking posture
- 09:37 Core exercises such as the dead bug
- 12:07 Daily habits and lifestyle changes
Daily sitting and movement habits influence how spinal discs respond to repeated loading over time.
These patterns are often seen in individuals with prolonged sitting, which may influence how spinal discs and surrounding structures adapt to daily stress.
Key Moments of the video:
- 00:00 Why posture matters
- 00:11 Lumbar spine, sacrum, and pelvic support
- 00:46 Muscles and ligaments in stability
- 02:20 How joints and discs respond to posture
- 02:54 Spinal motion segment explained
- 03:19 Disc structure during movement
- 05:02 Effects of poor posture on spinal structures
- 05:19 Long-term structural changes
- 06:20 Influence on nerve pathways
- 07:24 Posture during daily activities
Posture plays a continuous role in how the spine adapts to daily movement and loading patterns. These patterns are often seen in individuals with prolonged sitting or repetitive spinal loading during daily routines.
Slipped Disc Treatment at Each Spinal Level
The level of a slipped disc changes which methods fit and what I watch for. The spine holds 23 discs: 6 in the neck (cervical), 12 in the upper and middle back (thoracic) and 5 in the lower back (lumbar). My page on how each spinal disc is built and how it changes explains their structure.
Neck (Cervical) Discs
In the neck, I see the C5-C6 level most often, then C6-C7. A neck disc can send pain to the shoulder blade, down the arm and into the fingers. One that presses on the spinal cord can even weaken the legs, so I test the arms and the legs. Slipped disc treatment in the neck stays non-rotatory: the Activator, cervical decompression, soft tissue work, and later exercises such as isometrics against your own hand.
Forceful pulls with a towel or a strap, and any neck crack, stay out. For the wider neck picture, see:
- neck pain treatment in KL
- neck pain that reaches into the upper back
- care for a stiff neck
- low-force care from a neck chiropractor in KL
Mid-Back (Thoracic) Discs
A slip disc in the mid-back is rare. When I do see one, an old compression fracture often sits beside it, so the neck and lower back are checked as well. When someone brings an MRI of the mid-back alone, I often ask for another scan. For an upper thoracic disc that means the neck, for a lower one the lower back, and sometimes both. Care follows the same principles, adjusted to the region. A recent compression fracture is outside my care, and I encourage the person to see a spine surgeon.
Lower Back (Lumbar) Discs
In the lower back, the disc I see damaged most often is an L4-L5 disc, then L5-S1 and L3-L4. Most forward bending happens at these levels. Here, slipped disc treatment leans on flexion-distraction and lumbar decompression, and Kegel exercises start at once. The buttock and leg muscles that tighten with sciatica get their own care.
When the pain runs down the leg, my page on what the first weeks of sciatica treatment involve covers that side. The nerve's part is explained in why nerve pain happens and how it is assessed. For the wider lower back picture, see:
When Surgery or Injections Come Into the Plan
Surgery has a place in slip disc treatment, and there are times I cannot help. I raise it when focused conservative care, properly given, has brought no change. I also raise it for severe cases, among them a sequestered disc or an infection. Numbness around the genitals or anus and changes in bladder or bowel control need the urgent assessment described below. Even with a herniation, I see surgery as the last option rather than the first, and I feel the same about steroid injections.
The operations offered for a slipped disc include discectomy and microdiscectomy, laminectomy, foraminotomy and fusion. Success rates of 90 or 95 percent are often quoted for them. My Back Pain to Leg Pain talk asks what success means there. By most definitions it means any measured improvement. A pain score that falls from 10 to 9.99 counts, yet it would not feel like success to you.
My personal opinion: I do not recommend steroid injections into the spine as a first step, and in my view nucleoplasty has no value. If an invasive procedure becomes necessary, the choice belongs with a spine surgeon, and I would rather it came after focused care than before it. My page on weighing conservative care against an operation compares the two routes in more depth.
When considering slip disc treatment without surgery for back or leg pain, get urgent medical attention, a thorough assessment at a hospital emergency department straight away, within hours, if you develop new or worsening numbness around your genitals, between your genitals and anus, or around your anus. New difficulty passing urine, or any loss of bladder or bowel control, needs the same urgent assessment. These symptoms can have several causes. Some may call for an invasive procedure, but assessment helps determine which care options are appropriate and does not automatically mean you need surgery.
Leg weakness that keeps getting worse should not be ignored. It calls for a careful assessment by a competent provider, and conservative care can continue only while the weakness itself is improving.
Video: My Talk on Discs and Sciatica
This is my full talk on discs and sciatica. It starts with how a disc is built and why it gets damaged. It then covers how pain travels into the leg and what to avoid with a damaged disc. Near the end, I weigh conservative slip disc treatment against surgery. The chapter list lets you jump to the part you need.
Key Moments of the video:
- 00:00 Back and leg symptom patterns
- 06:22 Spinal disc structure explained
- 18:30 Healthy vs degenerated disc comparison
- 28:49 Stages of disc changes
- 38:00 Sitting and disc pressure
- 45:12 Disc pressure in different positions
- 57:13 Movements to avoid with disc issues
- 1:12:46 Sciatica and nerve involvement
- 1:33:12 Non-surgical vs surgical considerations
Understanding how spinal discs relate to nerve symptoms helps explain why pain may travel beyond the lower back into the leg.
This type of symptom pattern is often associated with spinal disc changes that influence nearby nerve pathways.
Searching for the Best Slip Disc Treatment in KL? What to Check
No single slip disc treatment is best for everyone, and no provider suits every disc. A good choice is one whose examination and methods fit what your disc and spine show, and these are the things you can check:
- Registration: in Malaysia, chiropractors must register with the T&CM Council under the Traditional and Complementary Medicine Act 2016, and that registration can be checked online.
- The qualification of the person who will treat you.
- An examination before any treatment, with your scans read as images, not only as a report.
- Findings and the plan explained in plain words, including the stage and the level of the disc.
- Gentle, non-rotatory methods for a damaged disc, with no twisting thrust and no forceful pull.
- Methods aimed at the disc itself, such as decompression or flexion-distraction, not only at the sore muscles.
- Chiropractic and physiotherapy working together, with exercise added at the right time.
- Fees stated before care begins.
- How progress is measured: the first visit's tests repeated, and clear review points.
- Referral to a doctor, or to a hospital emergency department, when the signs call for it.
Before you decide, call or WhatsApp each center you are weighing, describe your problem, and ask how they would examine it.
How Much Does Slip Disc Treatment Cost in KL?
At Chiropractic Specialty Center, the fees for slip disc treatment come from the CSC quotation dated June 25, 2026:
| Item | Fee |
|---|---|
| Examination, new or returning patient | RM100 |
| Report on MRI images you bring (one area), or on up to two X-ray films | RM50 |
| Chiropractic adjustment | RM150; RM110 in a visit that also includes physiotherapy |
| Flexion-distraction | RM45; RM35 in a visit that also includes physiotherapy |
| Cervical or lumbar decompression | RM130 a unit; RM100 in a visit that also includes chiropractic |
| High-intensity laser therapy | RM130 a unit; RM100 in a visit that also includes chiropractic |
| Other physiotherapy | RM57 to RM180 a standard unit, by service; RM27 to RM150 in a visit that also includes chiropractic |
What you pay in total follows from the examination findings, the methods in your plan and the number of visits. Chiropractic fees do not vary between CSC centers, and physiotherapy is charged at the same rates in Bukit Damansara and Bandar Sri Damansara. Every item, including any charged separately, is on the chiropractic price list and the physiotherapy price list. The fee for a plan is explained and agreed before care begins.
It often helps to read about slip disc treatment options alongside slipped discs, whether a slipped disc can be helped, what helps a slipped disc, and slip disc symptoms.
The other guides in this series follow one question each:
Related KL Chiropractic & Physiotherapy Pages
Slip disc concerns can involve the lower back, neck, nearby nerves, posture habits, and daily movement patterns. Readers comparing “slipped disc treatment in KL” may also want to understand how chiropractic, physiotherapy, and rehabilitation information is explained across CSC’s Kuala Lumpur pages:
Kuala Lumpur Centers and Physiotherapy
- Chiropractor in Kuala Lumpur: Chiropractic With Physiotherapy: This page explains CSC’s Bukit Damansara chiropractic and physiotherapy information for spine, joint, posture, and rehabilitation-related care.
- Chiropractor in Bandar Sri Damansara with Physiotherapy: This page is useful for readers near Bandar Sri Damansara, Kepong, Desa ParkCity, Sungai Buloh, and nearby areas who want chiropractic information with or without physiotherapy coordination.
- Physiotherapy in KL & Malaysia: Spine & Joint Care: This page explains physiotherapy-based care for slip disc, spine, joint, posture, movement, and rehabilitation topics in Kuala Lumpur and Malaysia.
Other Guides in This Series
- Slip Disc Explained: Causes, Stages, Symptoms and Care
- Slip Disc Symptoms and What They Point To
- Can a Slipped Disc Heal? What Changes and What Remains
- Slipped Disc Chiropractor in KL: What I Check, Use and Avoid
- Slipped Disc Treatment in Malaysia: What I Would Ask First
- Slipped Disc Treatment in KL: From First Exam to Maintenance
- What Helps a Slipped Disc, and the Habits That Set It Back
- Non-Surgical Slipped Disc Treatment in KL: Surgery or Not?
- Slipped Disc Care at CSC®: Non-Invasive Options
- Slipped Disc and Spondylosis: How They Differ
- Slipped Disc in the Jaw: TMJ Displacement, Causes & Care Options
- Sciatica vs Slipped Disc: Video Explanation
Neck, Back and Sciatica Care
- Neck Pain Treatment in Kuala Lumpur: Symptoms, Causes and Care: how neck pain from the joints, muscles and discs is assessed and cared for.
- Neck and Upper Back Care in Kuala Lumpur: when neck trouble spreads down between the shoulder blades and is treated as one problem.
- Neck Stiffness Care in Kuala Lumpur: what lies behind a stiff neck and the gentle care it calls for.
- Back Pain Treatment in Kuala Lumpur: Symptoms, Causes and Care: the causes of back pain beyond the disc and how each is told apart.
- Sciatica Treatment: What the First Weeks Involve: the early weeks of care when pain travels from the back into the leg.
Questions About Slipped Disc Treatment
These are the questions about slip disc treatment I hear most often at the centers, answered the way I answer them there.
Can a slip disc heal on its own without treatment?
In my experience, no. The pain can ease and return in cycles, and a quiet spell is easy to mistake for healing. But the damage inside the disc stays. Left alone, it tends to progress, sometimes over years and sometimes quickly. Even with slip disc treatment, I have never seen a damaged disc restored completely to how it was, and surgery cannot do that either. The years ahead depend on what you keep doing: the daily habits, the exercises and the maintenance care that follows an active plan. My guide on how far a damaged disc can recover goes into this in depth.
How many sessions does slipped disc treatment take?
There is no fixed number. The stage, the level, the other conditions found with the disc and how closely the advice is followed all differ. What I can give you is two review points. With no change by the fifth session, I reassess the plan. If there is still none by the tenth, the two of us decide whether care should go on. The active plan ends at maximum medical improvement, when a further two to three weeks of care no longer changes the retested findings. From then on, care is given as needed, while the home exercises and habits continue.
Is the treatment painful?
It should not be. Every method is kept within what you can comfortably tolerate, and if anything hurts, you tell the clinician at once. Discomfort during care can inflame the disc and the tissues around it, and make the pain worse later. Discomfort during care means it is being done too aggressively, and one of my videos, Is Chiropractic Safe? 13 Questions Answered, carries the same warning. High-intensity laser should feel only mildly warm, decompression is a slow pull and release, and the Activator gives a light, quick impulse. My motto has always been no pain, more gain.
Should I see a chiropractor or a physiotherapist?
Neither on its own, in my view. The two professions are registered separately and bring different strengths. A chiropractor works on the alignment and movement of the spinal joints. A physiotherapist works on the muscles, the ligaments and the rebuilding that follows. A damaged disc involves all of these, which is why I tell people not to choose between them but to choose both. What matters more than the title is whether the care is gentle, non-rotatory and planned from your own findings.
Can slipped disc treatment be given during pregnancy?
Yes, with changes. For a pregnant woman, every examination is done lying on the back or the side, or seated. Nothing is done that stresses the baby or reduces the room the abdomen has. Care is given lying on the side, with gentle, hands-on methods only and no shockwave or other machine-based methods at all. My main concern is relaxin, a hormone released in pregnancy that rises toward the birth. It makes joints throughout the body more mobile, so everything is kept extremely gentle.
Can the problem come back after treatment?
It can. In my experience, neck and back problems often return. The damage inside the disc never fully disappears, and the habits behind it tend to creep back. In my video Sciatica vs Slipped Disc, I explain that the moment you improve is the moment to begin the exercises that prevent a return. The home exercises are reviewed every three to six months, and the sitting, sleeping and lifting habits stay in place for good. Those habits, more than any single treatment, decide how the disc fares in the long run.
How soon should slipped disc treatment start?
Soon after the problem is clear, in my view. Damage to a disc can progress slowly or quickly. The fastest change I have seen was a mild bulge that became a severe, ruptured herniation within ten days of forceful treatment. Pain is not a reliable guide either, since a disc can stop hurting while the nerve beside it keeps weakening. Starting early also means the habits change while you are still motivated to change them, and that is when change comes most easily.
References
- Hancock MJ, Maher CG, Latimer J, et al. Systematic review of tests to identify the disc, SIJ or facet joint as the source of low back pain. Eur Spine J. 2007;16(10):1539-1550.
- Coulter ID, Crawford C, Hurwitz EL, et al. Manipulation and mobilization for treating chronic low back pain: a systematic review and meta-analysis. Spine J. 2018;18(5):866-879.
- Shealy CN, Borgmeyer V. Decompression, reduction, and stabilization of the lumbar spine: a cost-effective treatment for lumbosacral pain. Am J Pain Manage. 1997;7:63-65. Preliminary findings; no PubMed record.
- Apfel CC, Cakmakkaya OS, Martin W, et al. Restoration of disk height through non-surgical spinal decompression is associated with decreased discogenic low back pain: a retrospective cohort study. BMC Musculoskelet Disord. 2010;11:155.
- Chen L, Liu D, Zou L, et al. Efficacy of high intensity laser therapy in treatment of patients with lumbar disc protrusion: a randomized controlled trial. J Back Musculoskelet Rehabil. 2018;31(1):191-196.
- Mohammed WAA, Salem NA, Mohasseb AM, et al. Effect of high-intensity laser therapy on disc size and functional outcome in patients with lumbar disc herniation. Photobiomodul Photomed Laser Surg. 2026;44(8):505-512.
- Kamath AG, Gill SS, Ravisangar S, et al. Laser disc decompression in the management of lumbar disc herniation: a systematic review and meta-analysis. Brain Spine. 2026;6:106251.
- Brouwer PA, Brand R, van den Akker-van Marle ME, et al. Percutaneous laser disc decompression versus conventional microdiscectomy for patients with sciatica: two-year results of a randomised controlled trial. Interv Neuroradiol. 2017;23(3):313-324.
- Hayden JA, van Tulder MW, Malmivaara A, Koes BW. Exercise therapy for treatment of non-specific low back pain. Cochrane Database Syst Rev. 2005;(3):CD000335.
These references cover how the source of back pain is tested, and manual care and exercise for back pain in general. They also include studies of spinal decompression and laser for lumbar disc problems. None of them evaluates care at Chiropractic Specialty Center.
The Author of Slip Disc Treatment in KL: 8 Stages, Methods, MRI and Price
Slip Disc Treatment in KL: 8 Stages, Methods, MRI and Price was written by Yama Zafer, D.C., who has 30+ years in chiropractic and physiotherapy and founded Chiropractic Specialty Center in Kuala Lumpur in 2006.
Last Updated: Slip Disc Treatment in Kuala Lumpur, Matched to Each Stage
Slip Disc Treatment in Kuala Lumpur, Matched to Each Stage was last reviewed and updated on October 17, 2026.