



Slip Disc Care in Kuala Lumpur: What Happens at the First Visit
Slip disc care at Chiropractic Specialty Center (CSC) in Kuala Lumpur begins with the patient's own story of the pain. Many people with a slipped disc arrive with an MRI report nobody has explained, and one question: how serious is this?
The first visit takes 30 minutes to two hours, and it is never rushed. The history comes first, then an examination of the spine and nerves. Then the MRI or X-ray images themselves are read, not just the report. By the end, the disc's stage and its seriousness on my scale of 0 to 10 are explained in plain words.
Chiropractors and physiotherapists then plan the care together, for a slipped disc in the neck as much as one in the lower back. The plan draws on non-rotatory chiropractic care with the Activator instrument, spinal decompression, flexion-distraction and guided exercise, and never twists a damaged disc. In two high-quality trials pooled by a 2010 review, people given advice alone trailed disc surgery at first and matched it later. The sections below cover what to bring, the scan report's words, the methods, home instructions, review points, referral and fees.
For more information about slip disc care, contact the Bukit Damansara (KL) main center: WhatsApp+60 17 269 1873 Call+603 2093 1000
Slip Disc Care at CSC: Key Takeaways
| Question | Short answer |
|---|---|
| What should come to the first visit? | All earlier records, with any scans on CD or film beside their reports. Written notes help too: how the problem began and changed, what has been tried, and the questions to ask. |
| How serious is a slipped disc on the 0 to 10 scale? | Seriousness is rated from 0 to 10 in my practice. A true bulge, swollen only a little, sits at 1 or 2. A disc that pushes the sac around the spinal nerves aside, or touches a nerve, sits at 3 to 5. |
| Is an MRI needed before the first visit? | Not always. The examination decides whether a scan would help. When a disc problem is suspected, I rely on an MRI, since I never guess a final diagnosis. |
| Can care begin on the first day? | It can, when the examination allows it: the fee list includes an examination and an adjustment on the same day. For a lower back problem, Kegel exercises, which squeeze the pelvic floor muscles, start at once; wider exercise waits until the spine is stable. |
| What else does slip disc care leave out? | Forceful neck pulls, hot packs on a damaged disc or an inflamed area, heavy massage and stretching in the early stage. Care stays within what the patient can comfortably tolerate. |
| How is progress checked? | By repeating the first visit's tests. No improvement by session five means a reassessment; none by session ten means the patient and the chiropractor decide together whether care continues. The rule comes from Is Chiropractic Safe? 13 Questions Answered. |
| When is a hospital the first stop? | New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours. |
Conservative Slipped Disc Care: What Two Reviews Found
Two research reviews point toward conservative slipped disc care for the lower back. In one, advice alone matched disc surgery over the longer term; in the other, physiotherapy reduced pain and disability compared with control groups. Neither tested care at CSC, so each is reported for what it measured, in whom and with what limits.
| Review | Who was studied | What was compared | What it found |
|---|---|---|---|
| Hahne 2010 | 18 randomized trials, 1,671 people with a lumbar disc herniation and radiculopathy (7 trials rated high quality) | Conservative care, including advice alone against microdiscectomy (2 trials) | Advice trailed surgery at first and matched it later; moderate evidence favoring stabilization exercises over no treatment |
| Singh 2021 | 11 randomized trials of physiotherapy for a lumbar prolapsed disc (4 pooled per measure) | Physiotherapy against control groups | Pain 0.91 points lower on a visual analog scale; disability 5.76 points lower on the Oswestry Disability Index; straight leg raising not significantly different |
In the 2010 review, radiculopathy means leg symptoms from an irritated nerve root, and microdiscectomy is the usual disc operation. Its finding on advice and surgery rests on two high-quality trials analyzed together (Hahne and colleagues, 2010). This matches my view: a surgery's true success is measured 2, 3, 4 and even 5 years later, not days or weeks after the operation.
The 2021 meta-analysis searched two databases and pooled four trials for each measure (Singh and colleagues, 2021). The Oswestry Disability Index it used is a questionnaire on how much the back limits daily life.
Neither review tested the slip disc care described on this page, which is planned from each patient's examination and images, leaves out twisting, and is retested at fixed sessions. The reviews show the direction the evidence points; each patient's own retests decide how care goes on.
Asking About a First Visit at the Two KL Centers
To ask about a first visit or appointment times, call or WhatsApp either Kuala Lumpur center. Scans done elsewhere come on their CD or film, with the printed reports, because the images themselves are read at the first visit.
- Bukit Damansara (KL, main center): Call +603 2093 1000 or WhatsApp +60 17 269 1873 to see the Bukit Damansara / KL center.
- Bandar Sri Damansara (KL): Call +603 6262 5777 or WhatsApp +60 12 455 6939 to see the Bandar Sri Damansara center.
Addresses, parking and opening hours for both centers are on the list of CSC centers.
Before the First Slip Disc Visit: Records, Scans and Notes
Three things matter most before slip disc care begins: every earlier record, the scan images themselves, and written notes on the problem. Every new patient is asked to prepare in five ways:
- Gather every earlier medical record. Any MRI, X-ray or CT scan done before is brought on its CD or film, beside the written report, so that the images can be read during the visit.
- Sit down beforehand and write the story of the problem: when and how it began, and how it has changed. List every step already taken: at home, after online videos, or with a physiotherapist, chiropractor, specialist, traditional practitioner, family doctor or anyone else. Each of them is asked about at the visit.
- Note the questions to be answered and what the visit should concentrate on. Once the examination begins, they are easy to forget.
- Wear comfortable clothing.
- Consider coming with a family member. Two people remember different parts of what was said, which helps when the next steps are discussed at home.
Every detail written down helps the clinician understand the problem, and the plan is only as good as that understanding. During the examination, mention even the slightest discomfort at once, even when it seems unimportant.
The First Visit in 7 Steps
Every first visit for slip disc care runs in the same order, though how long each step takes depends on the case.
- The history. Many questions come first, because pain in the back, neck, buttock or leg has several possible sources. It can come from a muscle, a ligament, the facet joints (small joints that link the vertebrae at the back) or the disc. It can also come from a thickened ligamentum flavum, an elastic ligament inside the spinal canal. Other sources are a vertebra that has slipped forward or backward (spondylolisthesis), a narrowed canal or nerve opening, and pressure on a nerve root.
- The examination. Range of motion, orthopedic tests, a neurological evaluation and muscle testing. For the neck, grip strength, the OK sign made with the thumb and index finger, and pinprick sensation in the hands are also compared on both sides.
- The urgent signs. Questions cover new numbness around the genitals or anus, new difficulty passing urine and any loss of bladder or bowel control. Any one of them means a hospital emergency department straight away, within hours, before anything else is done. Leg weakness that is getting steadily worse needs a careful assessment by a competent provider.
- The scan decision. Not every patient needs imaging. When a disc problem is suspected, an MRI is the test I rely on, and X-rays answer questions of alignment and the joints. When an X-ray shows a slipped vertebra, three more side views may be taken to judge its stability: bending forward, bending backward and standing straight. An MRI then shows how it affects the discs, joints and nerves.
- Reading the images. The MRI or X-ray images themselves are read, not only the radiologist's report, because a report can leave out fine detail that matters for care. The findings are then set against the history and the examination.
- The findings, explained. In plain words: which disc, which stage in my order, how serious it is on my scale of 0 to 10, which tissues around it are involved, and what is most likely producing the symptoms.
- The plan and its fee, agreed. The methods that suit this disc and those left out, how often and for how long, the first instructions for home, and the fee, all explained and agreed before care begins. When the examination allows it, the first session follows the same day.
Reading a Slip Disc MRI: Report Words and Seriousness
Slipped disc is the everyday name for a whole series of stages, and a scan report cannot always tell them apart. The reason, which I cover in my Back Pain to Leg Pain talk, is that the center of a worn disc cannot be seen clearly. The radiologist is not wrong; the stage simply cannot be documented, so the report says bulge. A report that says bulge can therefore describe a disc already pressing on a nerve. That is why, at the first visit, slip disc care starts by translating the report into my own definitions, which the slip disc stages guide sets out in full.
By those definitions, a true bulge is a disc whose fibers have swollen beyond their usual borders without pressing on the spinal cord or a nerve. A disc that pushes the thecal sac (the sac around the spinal nerves) aside, or touches a nerve root, has moved on. It is a protrusion, prolapse or herniation, even when the report still says bulge.
Slipped disc reports often use these words, and I explain them this way:
| Report word | What it means |
|---|---|
| Diffuse | The disc bulges in all directions. |
| Mild | It is swollen only a little and displaces neither the thecal sac nor any other sensitive structure. |
| Pseudo | A false bulge, in essence no bulge at all, which can be a normal variant for that person. |
In slipped disc care, seriousness is a separate question, and I score it on a scale where 0 means no concern and 10 means a life-altering problem. On that scale a true bulge sits at 1 or 2. A disc that presses the thecal sac aside, crowds the opening where a nerve exits, or touches a nerve root sits at 3 to 5.
Here is why a scan can understate a slipped disc. An MRI is taken lying down, and a morning scan follows a night in which the disc has drawn in fluid. Later, after hours at a desk or behind the wheel, body weight can press the same disc further out, onto a nerve. As I put it, once a person has been upright for a while, the truth comes out. I call this a disc bulge in transition: a bulge on the report, but a protrusion, prolapse or herniation under load. It explains numbness and tingling that the report alone does not.
What Slipped Disc Care Needs: My Five Essentials
Non-surgical care for a slipped disc has to be clear, detailed and aimed at the exact problem. In my view, that takes five things at the same time, and each first plan is checked against all five:
- Knowledge. An understanding of how discs are damaged, how they bulge, herniate and tear, and how the damage moves from one stage to the next, with the evidence behind it.
- Skill. The clinician's own skill decides how precisely each method is delivered.
- Methods suited to a disc. A disc lies deep. How deep depends on a person's size and the fat under the skin. A disc in the neck or upper back sits about 3 to 6 centimeters down. One in the lower back sits 4 to 10 centimeters down, or more. In Is Chiropractic Safe? 13 Questions Answered I ask how a manipulation alone could take care of a disc that deep. So a plan also draws on spinal decompression, flexion-distraction and high-intensity laser therapy, each chosen from the findings.
- Precision. Care aimed at the joints, discs, ligaments and muscles that the findings document, rather than routine treatment of the back. That is what I mean by focused conservative care; many routine forms of conservative care are of little use.
- Combined professions. Chiropractic, physiotherapy and rehabilitation working to a single plan. Holistic means comprehensive, and no single approach is comprehensive. In Is Chiropractic Safe? 13 Questions Answered, that is the reason I advise choosing both.
Most slipped discs also arrive with company: a thickened ligamentum flavum, enlarged facet joints, spondylosis, a slipped vertebra, bone spurs, degeneration at other levels, scoliosis or a narrowed canal. Each one found is planned for alongside the disc, and the guide to choosing slipped disc treatment in Malaysia describes how these conditions travel together.
Slipped Disc Care Methods Used at CSC
Each slip disc care plan draws on the methods below, matched to the tissues the examination finds. At CSC, chiropractors and physiotherapists treat the same patient, often within the same visit.
- Non-rotatory chiropractic manipulation with the Activator instrument, a hand-held tool.
- Spinal decompression on a decompression table, with lighter, shorter sessions for older patients whose canal is narrowed or whose joints are worn.
- Flexion-distraction, which moves the spine on a table built for it (the Cox method).
- High-intensity laser therapy and shockwave, aimed at the soft tissue around the injured level.
- Therapeutic ultrasound and interferential current, a form of electrotherapy, for the same tissues.
- Cold therapy from a cryotherapy machine. Its heat setting stays off any spine with a damaged disc or a facet joint problem.
- Trigger point and myofascial therapy for the muscles and fascia that tighten around an irritated nerve, without deep pressure on the muscles right beside the damaged level.
- Guided exercise with rehabilitation equipment, including core coordination work on the Spinercise® exercise system, once the spine is ready for it. The gym-style machines for building muscle are at the Bukit Damansara main center.
- Advice on posture, sitting and work set-up, home exercises and daily habits, with nutrition discussed where it bears on the muscles and joints.
On nutrition, my Back Pain to Leg Pain talk is direct. Supplements such as glucosamine, chondroitin and MSM can support muscles, ligaments and joints. Even so, I know of no compound that builds up the disc itself. For vitamins D3 and K2 and for magnesium glycinate, my advice in the same talk is to check with a doctor first.
Protecting a Damaged Disc During Care
- No twisting or cracking of a damaged disc. I am a Gonstead practitioner, trained in manual adjusting, and I still do not use a rotary adjustment on a slipped disc. My video Sciatica vs Slipped Disc gives the reason: rotary manipulation is kept for a spine where I am 100 percent sure that no disc is damaged. In that video I also ask: "Because how can you be sure? So it's better to be safe than sorry."
- No forceful neck pulls, towel yanks or strap devices, for the reasons in the video below and in whether the Ring Dinger® is safe.
- No hot packs. Heat stays off a damaged disc or an inflamed area. The reason, from my Back Pain to Leg Pain talk: heat adds to the inflammation.
- No heavy massage, and no one walking on the back. Massage, where it is used, is myofascial release by an experienced physiotherapist.
- No stretching or wider exercise in the early stage.
Care is kept within what the patient can comfortably tolerate, and the patient tells the clinician at once if anything hurts. Discomfort during care means it is being done too aggressively. My motto has always been "No pain, more gain."
Video: Is Chiropractic Safe? 13 Questions Answered
Thirteen questions patients put to me are answered here: how safe chiropractic is, which methods suit a damaged disc, when imaging is needed, and what the fifth and tenth sessions decide. The chapter list and the transcript are on the Is Chiropractic Safe video page.
Video: Neck Cracks Are Dangerous
Forceful neck pulls seen online raise safety questions. In this video I explain how the neck's small joints, its arteries and its discs make towel pulls, strap devices and similar yanks dangerous, and why neck care should be focused and never aggressive. Its key moments, with my words in an edited transcript, are listed on the Neck Cracks Are Dangerous video page.
First Instructions After the Visit: Exercise and Daily Habits
In slip disc care, Kegel exercises start at once for everyone with a lower back problem. Early on, two more are allowed: squeezing the buttock muscles, and raising the top leg while lying on one side. Everything else, stretching included, is held back until the spine has settled, which for most patients comes between the fifth and seventh sessions, and for a few as early as the third.
Until the next visit, the habits below take load off the slipped disc. My Neck and Back Self-Help Tips video says why now is the moment: "the best time to do it is when you're hurting, because when you're feeling better, you're not going to change anything."
- Sitting: with an acute or active back problem, stand after 15 to 20 minutes and stay on the feet for 30 seconds to a minute. With a mild back problem, stand every 30 to 40 minutes, and without back pain, every hour.
- Driving: while the back pain is acute and intense, a stint behind the wheel lasts about 15 minutes. Stop by 20 to 30 minutes at the latest, where it is safe, and walk. A gentle calf stretch can join the walk from the start, provided it causes no pain.
- Sleep: no less than six hours, ideally seven to eight without waking, lying on one side with the spine kept straight, or face up with a firm roll beneath both knees.
- Bending, twisting and lifting: none at the waist, and nothing over 2 kg if lifting cannot be avoided.
- Ice: an ice pack inside a cloth, on for 10 to 15 minutes by a timer, two or three times daily with two hours or more between sessions.
- Swimming laps wait; walking in water is gentler. Gym work waits too, and free weights, deadlifts and leg presses stay out even once the spine is stable.
- Yoga must be avoided with a slipped disc, since its folds and twists load an injured disc.
- Symptoms that linger are never ignored. The line I use for this in my Back Pain to Leg Pain talk: "Pain is not a bad thing. Ignoring pain is bad."
- Exercise is not started from videos or on one's own. Its dose and pace are set by a clinician, because some movements suit a disc only later.
The time spent in care is short beside the rest of the day, as my video Sciatica vs Slipped Disc puts it: "In a day, there's 24 hours. I see a patient 30 minutes, two hours. What about the other 22 hours? You have to mind your posture, your habits." The fuller set of home measures is in the guide to what helps a slipped disc.
Video: Poor Posture Damages Your Spine
In this video I show how sitting position, desk set-up and repeated movements load the spinal discs, from the muscles inward to the disc. To jump to a part of the video or read along, open the Poor Posture Spine video page.
How Progress Is Reviewed After the First Visit
In slip disc care, the first visit is the baseline for everything after it. Its tests are done again, the pain gets a score out of 10, and the patient is asked what has changed in sitting, walking and sleep.
Two review points are fixed. A fifth session with nothing better on retesting leads to a full reassessment. A tenth session that still shows nothing better leads to a shared decision, the patient's and the chiropractor's, on whether care goes on. Is Chiropractic Safe? 13 Questions Answered sets out why.
Active care runs until MMI, maximum medical improvement. I place that point where a further two to three weeks of care leave the retests unchanged. From then on, visits are as needed, while the home exercises, preventive care and daily habits continue.
Pain alone does not mark the end of care. In my words, symptoms are the last thing to show up and the first thing to leave: the pain of a slipped disc can ease while the disc and the muscles and ligaments around it are still healing, and pain that eases early can come back. So the retests, not the pain score alone, decide when active care ends, and I do not call that point a cure. A cure would mean every bit of function regained, which no one can promise for a damaged disc.
Honesty matters too: in Is Chiropractic Safe? 13 Questions Answered I ask patients to be open about what they did between visits.
When a Slipped Disc Is Referred Beyond CSC
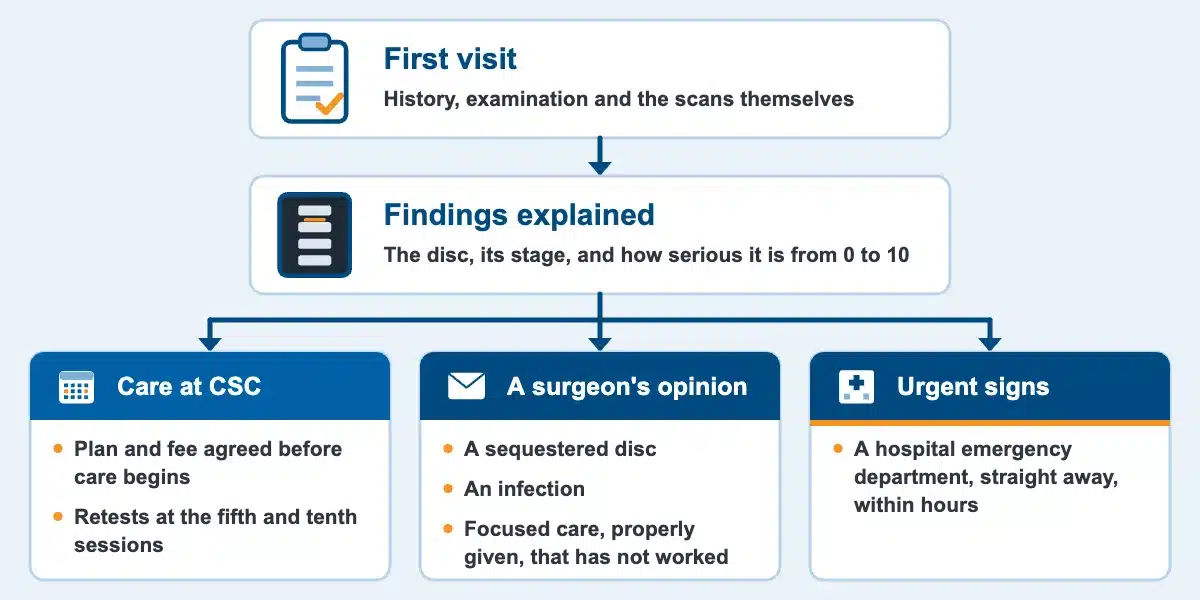
A slipped disc is referred beyond CSC when the findings call for it, and the patient hears so at the first visit. Hospitals have an essential place in slipped disc care, in emergencies and in surgery.
In my approach, a surgeon's opinion is sought for:
- A sequestered disc, where a piece has broken away completely.
- An infection.
- The urgent signs below.
- Focused conservative care, properly given, that has not worked.
A plan that needs a service CSC does not provide includes a referral to a suitably qualified provider.
Before the first visit, and at any point in care for back or leg pain from a slipped disc, any new or worsening numbness around your genitals, between your genitals and anus, or around your anus needs urgent medical attention: a thorough assessment at a hospital emergency department straight away, within hours. New difficulty passing urine needs the same, even before any loss of bladder or bowel control, and a loss of that control is urgent too. These symptoms can have different causes, and assessment helps identify the appropriate next step. Some may call for an invasive procedure, but being assessed does not mean that you necessarily need surgery.
Leg weakness that keeps getting worse should not be ignored. It calls for a careful assessment by a competent provider, and conservative care can continue only while the weakness itself is improving.
What Does a First Slip Disc Visit Cost at CSC?
Each fee below is taken from the CSC quotation dated June 25, 2026; the physiotherapy fees page lists every physiotherapy item.
| Item | Fee |
|---|---|
| First-visit examination | RM100 |
| Reading MRI images that are brought in, with a report of the findings (one area) | RM50 |
| Reading X-rays that are brought in (up to two films) | RM50 |
| Examination with a chiropractic adjustment, when care begins the same day | RM250 |
| Each chiropractic adjustment | RM150, or RM110 when physiotherapy is part of the same visit |
| Physiotherapy, per standard unit | RM57 to RM180, depending on the service, or RM27 to RM150 per unit with chiropractic in the same visit |
The examination findings, the methods chosen and the number of visits set the total cost of slip disc care, and a new scan is charged by the imaging center. The chiropractic price page lists every chiropractic item.
The fee for a plan is explained and agreed before care begins.
Slip Disc Care at CSC: First Visit Questions (FAQ)
Should a back support belt be worn for a slipped disc?
A belt does not improve the condition. My advice is to keep a belt for the acute and severe stages of back pain, and only for people who must stay active at work or when walking. It goes on firmly for walking or standing and is eased off when sitting, to its lightest setting, like a loose shirt; it never goes to bed. Some belts have two attachments, one for light wear and one for a firmer hold.
What if there is no MRI yet?
The examination comes first and decides whether a scan would help. For a suspected disc problem my choice is an MRI. Is Chiropractic Safe? 13 Questions Answered gives the reasons: it uses no radiation, and it pictures bone, joints, muscle, ligament and the room left for the nerves. An X-ray pictures bone alone.
CSC has no MRI scanner of its own. When an MRI is needed, CSC arranges the referral and the appointment at an imaging center or hospital, which charges for the scan separately; an MRI is not done on a walk-in basis.
Will the examination hurt?
The examination is kept within what the person can comfortably tolerate. The slightest discomfort is mentioned at once, even when it seems unimportant. Discomfort means a test is being done too aggressively, and the test is then changed. For a pregnant patient, the examination is done entirely lying on the side, lying on the back or sitting. Nothing in it may stress the baby or take away the room the abdomen normally has.
How many sessions does slip disc care take?
No number fits everyone, and none is given before the examination. In Is Chiropractic Safe? 13 Questions Answered I name what sets the pace. It depends on how severe the problem is, the other conditions that come with it, how closely the advice is followed, and consistency. Nothing in a plan is ready-made, because a slipped disc seldom comes on its own. What stays fixed are the review points: a retest by the fifth session, and a shared decision by the tenth if nothing has improved.
Is the spine cracked or twisted during slip disc care?
Not on a damaged disc. The chiropractic manipulation used is non-rotatory, with the Activator instrument, and flexion-distraction moves the spine on a table without twisting it. The cracking sound some people expect is cavitation, a release of gases from the joint. Methods that make that sound are not what I recommend after 40 when the spine shows degenerative changes, bone spurs or a pinched nerve. Is Chiropractic Safe? 13 Questions Answered gives my alternative: "Instead, the Activator is better." Diversified, the manual method most chiropractors use, involves even more rotation than Gonstead, so neither is used on a damaged disc. The three methods are compared in Gonstead, Diversified and Activator Techniques Explained.
What should be avoided before the first visit?
Until the first visit, hot packs stay off the back, and stretching, twisting, heavy lifting and long spells of sitting are best avoided. With an acute or active back problem, sitting is broken every 15 to 20 minutes by standing for half a minute to a minute. An ice pack wrapped in a cloth, on for 10 to 15 minutes, is the gentler choice. New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours.
How to Read This Guide
This guide describes how slip disc care at CSC starts, from the first visit to the review points. When a view comes from a video or talk of mine, I name it. Each study is named by its first author and its year, and what it found applies to the group it studied rather than to any one disc. A page cannot examine anyone or decide what a particular disc needs; that is the work of the first visit.
Peer-Reviewed References
- Hahne AJ, Ford JJ, McMeeken JM. Conservative management of lumbar disc herniation with associated radiculopathy: a systematic review. Spine (Phila Pa 1976). 2010;35(11):E488-504.
- Singh V, Malik M, Kaur J, Kulandaivelan S, Punia S. A systematic review and meta-analysis on the efficacy of physiotherapy intervention in management of lumbar prolapsed intervertebral disc. Int J Health Sci (Qassim). 2021;15(2):49-57.
These references describe conservative slipped disc care, for a lumbar disc herniation, in general; none of them looked at the care given at CSC.
The Author of Slip Disc Care at CSC KL: First Visit in 7 Steps
Slip Disc Care at CSC KL: First Visit in 7 Steps was written by Yama Zafer, D.C., who has 30+ years in chiropractic and physiotherapy and founded Chiropractic Specialty Center in Kuala Lumpur in 2006.
Last Updated: Slip Disc Care in Kuala Lumpur: What Happens at the First Visit
Slip Disc Care in Kuala Lumpur: What Happens at the First Visit was last reviewed and updated on October 22, 2026.