


C7-T1 Spine: Joint, Disc & Nerve Care in Kuala Lumpur
C7-T1 is the junction where the mobile cervical spine meets the far stiffer thoracic spine. Transition zones of that kind take more strain than the segments on either side of them. The nerve root leaving here is C8, and its territory is specific: the little finger, the ring finger and the inner edge of the forearm.
Tingling in the little finger is therefore the symptom that points to this level, often with weakness of grip or of spreading the fingers apart. That distribution separates it from carpal tunnel syndrome, which affects the thumb side of the hand and never the little finger.
Care at C7-T1 is gentle and non-rotatory at CSC, pairs chiropractic with physiotherapy, and is kept within what you can comfortably tolerate. This guide covers where C7 and T1 are, the C8 and T1 nerve root symptoms and the disc. It then turns to the warning signs and the whole neck.
For more information about the C7-T1 level, contact the Bukit Damansara (KL) main center: WhatsApp+60 17 269 1873 Call+603 2093 1000
Takeaway: Key Points on C7-T1 Care
| Question | Short answer |
|---|---|
| Where is C7-T1? | Low in the neck, at the point where the neck joins the upper back. C7 is usually the bump you can feel there, the vertebra prominens, and T1 is the first bone of the upper back, just below it. |
| Why does this level matter? | It is a vital transition zone. C7-T1 connects the mobile neck to the stable upper back. It protects the C8 nerve, which controls grip strength, finger motion and part of forearm sensation. |
| Which nerve roots are involved? | The C8 root leaves the spine at C7-T1 and serves the finger flexors. The T1 root leaves one level lower and serves the hand's small muscles (Margetis and colleagues, 2025). |
| What does C8 nerve root compression feel like? | Tingling or numbness in the ring and little fingers and along the inner forearm, a weak grip, and clumsy fine finger movements. Typing or gripping objects can tire the forearm quickly. |
| Which problems are common here? | Disc bulges, herniations, arthritis, bone spurs, facet irritation, cervical ribs and thoracic outlet compression can all occur here. Several of them can also press on the C8 nerve root as it leaves the spine. |
| Does a disc bulge at C7-T1 press on a nerve? | In my view, no, not as a true bulge in the shape the MRI captures. If the hand is affected, the disc is in transition and bulges further once the spine is loaded upright. |
| Can C7-T1 affect the rest of the neck? | Yes. C7-T1 issues may influence other neck segments from C0-C1 down to C6-C7, bringing posture strain, radiating arm symptoms and reduced shoulder stability. I see the whole neck as one chain. |
| Which methods are avoided? | Unsafe traction techniques such as towel jerks, Y-Strap pulls and Ring Dinger methods, which can aggravate the spinal cord and nerve roots. Yoga must be avoided too with a C7-T1 disc problem. |
| How does CSC care for C7-T1? | Gentle, non-rotatory chiropractic care combined with targeted physiotherapy, spinal decompression and posture rehabilitation at the Kuala Lumpur centers. All of it is kept within what you can comfortably tolerate. Surgery comes last, only if this focused care has not worked. |
C7-T1 Guide: Jump to a Section
- Where Is C7-T1? Locating C7 and T1
- C8 and T1 Nerve Root Compression Symptoms
- Disc Bulge and Herniation Symptoms
- Warning Signs That Need Urgent Care
- What CSC's KL Centers Offer
- Understanding the C7-T1 Segment
- Neck Issues and Problems: Scope, Causes & Impact
- How C7-T1 Malfunctions Affect the Entire Neck
- Upper Cervical and C7-T1: A Two-Way Connection
- Unsafe Neck Traction Methods: Why Towel Pulls, Y-Strap & Jerking Techniques Are Risky
- NSD Therapy®: A Non-Invasive Option for Mid & Lower Neck Conditions
- Common Problems at This Junction
- Key Statistics on C7-T1 Disorders
- Spatulated & Elongated TVP at C7: A Hidden Risk Factor
- Thoracic Outlet Syndrome & Its Link to the Lower Neck
- Cervical Rib & Disc Disorders
- Other Conditions That May Affect This Level
- Non-Invasive Solutions for C7-T1 Conditions
- Summary Table: C7-T1 Spine
- A Second Kuala Lumpur Center
- Conclusion
- Questions You Didn't Know to Ask
- FAQ: C7-T1 Spinal Joint, Disc & Nerve Care
Where Is C7-T1? Locating C7 and T1
The neck has seven bones, C1 to C7, and the upper back starts with T1. C7-T1 is the joint and disc between the last neck bone and the first upper back bone, roughly level with the tops of the shoulders.
C7 is easy to find. The vertebra prominens, the long single spinous process of C7, is usually the bump felt at the base of the neck (Kaiser and colleagues, 2023). It stands out most when the head bends forward, and C7-T1 sits just below it.
In shape, C7 is partly a neck bone and partly an upper back bone: a transitional vertebra (Kaiser and colleagues, 2023). T1, below it, is where the first pair of ribs attaches.
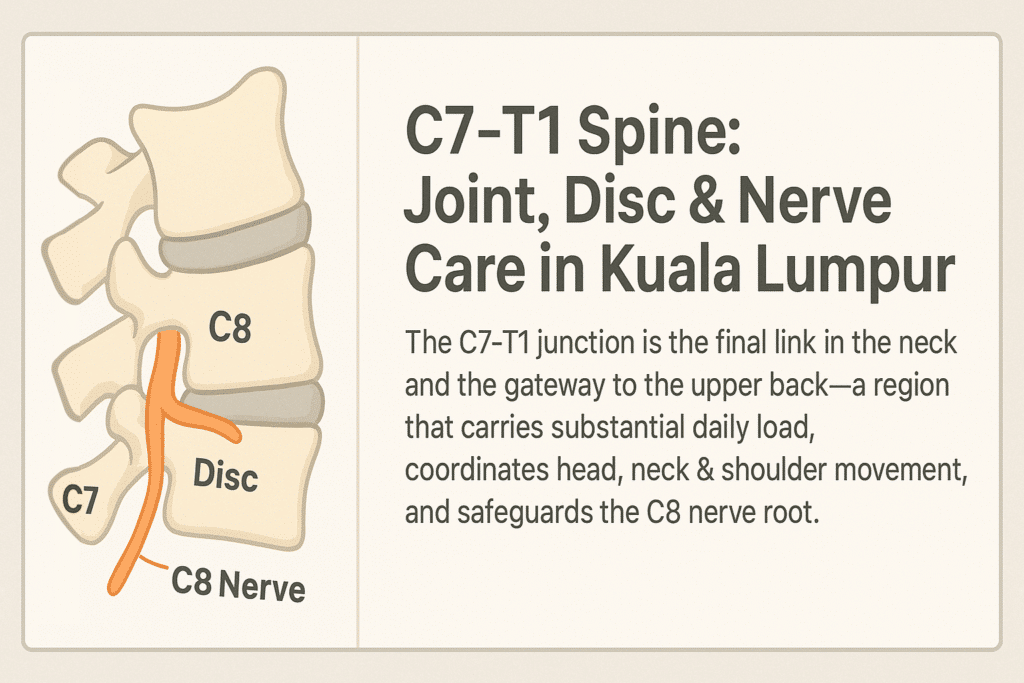
The levels above behave differently. A C6-C7 problem usually affects the C7 root, which runs to the middle finger, and a C5-C6 problem the C6 root, toward the thumb.
C8 and T1 Nerve Root Compression Symptoms
Two nerve roots matter here. The C8 root leaves the spine at C7-T1, and the T1 root leaves one level lower, between T1 and T2. Together they form the lower part of the brachial plexus, the nerve network that supplies the arm.
Strength testing checks C8 through the finger flexors and T1 through the interossei, the small muscles between the hand bones (Margetis and colleagues, 2025). C8 and T1 are affected less often than C6 and C7.
Symptoms of C8 nerve root compression usually include:
- Numbness or tingling in the ring and little fingers (C8 nerve distribution).
- Weak grip and clumsiness in fine finger movements.
- Loss of dexterity or forearm fatigue with simple tasks like typing or gripping objects.
- Pain along the inner edge of the forearm.
When the T1 root is involved, weakness spreading the fingers apart or holding them together stands out. The inner side of the upper arm can also feel numb.
The C8 root is the only nerve root without a vertebra of its own name. It leaves at the junction where the neck meets the upper back, and that is why C7-T1 has a pattern of its own.
As I explain it, a C7-T1 problem is not just neck pain and stiffness. It is felt along the inner side of the arm and can reach into the armpit, which is what we call a C8 radiculopathy.
With a pinched nerve at C7-T1, most people notice numbness, tingling, burning or pins and needles in the little finger, the pinky. At times it extends into the ring finger.
The C8 nerve bends the fingers. People with this problem struggle to make a fist or to hold objects, and the thumb weakens, including extending it.
A C8 radiculopathy is unusual, and it is tricky. The deep tendon reflexes do not show it: the biceps and triceps reflexes are no use in identifying a C8 radiculopathy.
If you are losing grip strength, or struggling to open a bottle or a jar, the lower neck is the likely source. That means C6-C7 or C7-T1.
How I Test the C8 Root
Other tests a clinician can use, always comparing both sides:
- The OK sign: the thumb and index finger form a tight circle, and the patient holds it while the clinician tries to pull it apart. A clear weakness on one side counts.
- Grip strength, which can be classed as a neurological test, with the fingers also spread out against resistance.
- A pinprick sensory test on the little finger and on the inner side of the middle finger, looking for a deficit.
The gold-standard test is EMG with a nerve conduction study. I rarely turn to it, as it can be painful, and I use it only if the care I prescribe is not working.
My own first choice for checking any possible nerve root involvement is always a cervical MRI. X-rays can add flexion, extension and neutral lateral views, with oblique, AP and lateral views. They show how the neck aligns while it carries weight.
A C8 or T1 problem can cause hand weakness even without neck pain. Weakness that keeps getting worse should be assessed promptly. Where weakness is present, conservative care can continue only while the weakness itself is improving.
Disc Bulge and Herniation Symptoms
Disc bulges and herniations happen less often at C7-T1 than at C5-C6 or C6-C7, but when they do, the hand is usually where they show.
My position is that a bulge, in the shape the MRI shows it, does not compress the C8 root. The picture is taken with the person lying still and the disc unloaded.
Once the spine carries weight again, through hours at a desk, a phone or a steering wheel, a weakened disc pushes further. I describe that as a disc in transition. It behaves like a protrusion or a herniation, and only then can it account for symptoms in the hand.
My sequence, from Why Spinal Discs Get Damaged: “A bulge becomes a protrusion, then a prolapse, then a herniation, a rupture, fragmentation, and sequestration.”
A partly torn-away piece makes a fragmented disc. A piece that separates completely makes a fully fragmented disc, also called sequestered.
Typical C7-T1 disc symptoms are a stiff neck with pain low at its base. Tingling in the ring and little fingers and a weaker grip are common too. Nerve damage at this level shows the same way, in the C8 and T1 territory.
Warning Signs That Need Urgent Care
The spinal cord also passes C7-T1. Clumsy hands, a change in walking or balance, or a new urgency to pass urine point to the cord rather than one nerve. They need prompt medical assessment (Margetis and colleagues, 2025).
Any change in bladder or bowel control calls for urgent medical attention at a hospital emergency department straight away, within hours.
When to Call 999
Sudden stroke signs are an emergency. Call 999 straight away for any of these signs, which the US Centers for Disease Control and Prevention lists, and let someone else drive:
- A face, an arm or a leg suddenly turning numb or weak, often worse on one side.
- Sudden confusion, or trouble with speech, either speaking or understanding it.
- A sudden problem seeing out of one eye or both eyes.
- Sudden difficulty walking, dizziness, unsteadiness or loss of coordination.
- A sudden and severe headache with no cause that anyone knows of.
After a fall, a road accident or a hard blow, Mayo Clinic's first-aid advice says to suspect a spinal injury if any of these appear. Call 999, and keep the person and their head and neck still:
- There was significant force to the head or the back.
- The neck or the back hurts severely.
- A head injury is followed by a lasting change in how awake or alert the person is.
- Weakness, numbness or paralysis appears, or the limbs, bladder or bowels cannot be controlled.
- The head, neck or back is twisted or held at an odd angle.
What CSC's KL Centers Offer
At Chiropractic Specialty Center, care for C7-T1 conditions is non-invasive, segment-specific and posture-corrective. Our integrated approach may include:
- Gentle joint mobilization without high-velocity neck rotation.
- Spinal decompression therapy where the C8 nerve is under pressure.
- High-intensity laser therapy (HILT) as a short-term addition to exercise, for disc and nerve problems.
- Targeted physiotherapy for posture, scapular stability and grip strength.
- Myofascial release for scalene, pectoralis minor and upper trapezius tension.
Every plan is tailored to the patient's age, structural findings and activity needs, with safety first throughout.
The chiropractors and physiotherapists at Chiropractic Specialty Center in Kuala Lumpur give integrative, non-rotatory care, tailored to each patient's age, condition and spinal structure. For personal input beyond this guide, call or message either center:
- Bukit Damansara (KL, main center): Call +603 2093 1000 or WhatsApp +60 17 269 1873 to see the Bukit Damansara / KL center.
- Bandar Sri Damansara (KL): Call +603 6262 5777 or WhatsApp +60 12 455 6939 to see the Bandar Sri Damansara center.
Understanding the C7-T1 Segment
C7-T1 is the cervicothoracic junction: a meeting point where the flexible cervical spine meets the more stable thoracic spine. Its disc cushions vertical forces, while its facet joints channel movement.
The C8 nerve root exits here, traveling through the brachial plexus into the arm and hand. Because this is a transitional zone, it is more vulnerable to mechanical stress from repetitive movement, poor posture or sudden loading forces like whiplash.
In my experience, C6-C7 and C7-T1 move less than the rest of the neck. That makes them harder to damage, but it does happen.
The C7-T1 junction is the final link in the neck and the gateway to the upper back. It carries substantial daily load, coordinates head, neck and shoulder movement, and safeguards the C8 nerve root.
This nerve controls fine grip strength, finger coordination and sensation in parts of the forearm. That makes C7-T1 essential for both precision and stability in upper limb function.
Changes here, whether from posture strain, repetitive stress or structural shifts, can influence every segment above and alter how the shoulders and arms perform. The sections that follow cover what makes C7-T1 unique and the conditions that often develop here. They also cover how it can affect other neck levels and the gentle approaches used in care.
Neck Issues and Problems: Scope, Causes & Impact
Neck problems can arise from a range of mechanical, degenerative and postural factors. The cervical spine houses and protects the spinal cord, supports the head's weight and enables multi-directional movement.
Disruption in its joints, discs or soft tissues can produce localized stiffness or radiating neurological symptoms. Common causes include:
- Degenerative disc disease and cervical spondylosis: wear over the years that reduces disc height and alters joint mechanics (Gore and colleagues, 1986).
- Disc herniation: nucleus pulposus material pressing on spinal nerves (Radhakrishnan and colleagues, 1994).
- Facet joint arthropathy: inflammation or degeneration of the cervical facet joints (Aprill and colleagues, 1990).
- Postural stress: prolonged forward head posture increasing load on the cervicothoracic junction (Neumann, 2017).
- Whiplash injuries: sudden flexion-extension strains damaging ligaments and discs (Sterling and colleagues, 2010).
Impact on daily life: neck disorders can limit movement, cause referred arm symptoms, disrupt sleep and affect work performance. In severe cases, they can lead to chronic disability.
For a child or teenager with neck and upper back stiffness from screens or study, see the guide to chiropractic care for children. That guide sets out how the neck and upper back are assessed. The guide to neck manipulation in children covers the age guidance.
Many people who read about the C7-T1 junction also want to know about upper back pain.
How C7-T1 Malfunctions Affect the Entire Neck
The C7-T1 segment is the structural bridge between the neck and upper back. Any malfunction here can disrupt the entire cervical chain from the occiput and C1 down to the lower cervical spine.
That includes a slipped disc (bulge or herniation), arthritic changes, bone spurs, muscle imbalance or nerve root compression.
I see the cervical spine as one kinematic chain, and the effect runs both ways. Trouble at the lowest link climbs to the middle levels, then to the upper neck and the base of the skull. Eventually it reaches the brainstem and the brain.
A head carried forward over a laptop, a phone or another handheld device loads the whole lower neck. In my view, the lower levels take that strain at least as much as the upper ones, with C4-C5 and C5-C6 as the workhorses.
The multifidus and erector spinae run from the base of the skull to C7, linking each level to the next. As I see it, they stress the segments one at a time and, collectively, bring degenerative and spondylotic change. If it worsens, a nerve or the cord can be impinged, sometimes with cord edema.
So my care is never aimed at C7-T1 alone. A problem here can occur by itself, but it is often linked with the levels from C4 to C6.
Impact on upper cervical segments (Occiput-C1, C1-C2 and C2-C3)
Upper levels: Occiput-C1, C1-C2 and C2-C3.
- Increased tension in the suboccipital muscles due to compensatory head positioning.
- Possible headaches, dizziness or visual disturbances from altered biomechanics.
Impact on mid-cervical segments (C3-C4 and C4-C5)
Middle levels: C3-C4 and C4-C5.
- Secondary joint overload as they absorb more motion.
- Facet irritation and muscle guarding leading to stiffness or reduced range of motion.
Impact on lower cervical segments (C5-C6 and C6-C7)
Lower levels: C5-C6 and C6-C7.
- Acceleration of disc wear and narrowing of nerve canals.
- Radiating symptoms such as shoulder ache, upper arm weakness or tingling in the forearm.
Because the cervical spine functions as an interconnected system, C7-T1 problems are worth assessing early and as part of the whole neck. That is a key principle in careful, comprehensive neck care (Fernandez-de-las-Peñas and colleagues, 2006; Radhakrishnan and colleagues, 1994).
Upper Cervical and C7-T1: A Two-Way Connection
The cervical spine operates as a single functional unit, meaning stress in one region often affects others. The upper cervical spine (C0-C3) governs fine head movements and balance. The C7-T1 junction bears heavy mechanical load as it transitions to the thoracic spine.
When C7-T1 suffers from disc narrowing, postural strain or degeneration, compensatory changes can occur in the upper neck. These include muscle overactivation, joint compression and altered proprioception.
Conversely, instability or stiffness in the upper cervical region can shift mechanical stress downward, accelerating wear at C7-T1. Care therefore has to evaluate the entire cervical chain, not just the symptomatic level, to avoid recurring problems (Fernandez-de-las-Peñas and colleagues, 2006).
For the top of the neck, the C2-C3 and upper cervical guides explain the four suboccipital muscles and the myodural bridges.
Unsafe Neck Traction Methods: Why Towel Pulls, Y-Strap & Jerking Techniques Are Risky
Certain viral or commercially marketed neck traction techniques, including towel-wrapped neck pulls and Y-Strap pulls, apply sudden force to the neck, and I never use them.
These maneuvers often involve rapid, high-force distraction without segmental control. Risks include:
- Vertebral artery strain leading to vascular injury.
- Excessive ligament stretch destabilizing the spine.
- Disc injury or herniation from uncontrolled loading.
- Nerve traction injuries causing radicular symptoms.
Safe cervical care at CSC prioritizes gradual mobilization, precise segment targeting and avoidance of high-force distraction.
Such methods should be avoided entirely, especially in individuals with undiagnosed vascular, disc or ligament conditions, and replaced with clinically guided, gentle mobilization techniques.
My own words in Neck Cracks Are Dangerous: “Aggressive neck care is never good and should always be avoided.”
NSD Therapy®: A Non-Invasive Option for Mid & Lower Neck Conditions
NSD Therapy® is a specialized, non-invasive program for mid and lower cervical spine conditions, without surgery or injections. It combines spinal decompression, targeted physiotherapy, posture correction and gentle mobilization, aimed at lowering mechanical stress on the discs, joints and nerves.
It focuses on controlled, segment-specific decompression and muscle rehabilitation, with joint spacing, spinal alignment and neck mobility as its aims. It is designed for disc bulges, herniations, spondylosis, postural strain and early nerve compression, without high-force or rotational techniques.
Common Problems at This Junction
- Disc protrusion or extrusion narrowing the nerve exit (foramen).
- Degenerative disc changes lowering disc height and altering mechanics.
- Facet joint irritation from postural strain or repetitive load.
- Postural rounding leading to muscle imbalance and joint compression.
Key Statistics on C7-T1 Disorders
These are the figures as I have them, with the sources given for them, followed by studies read for this page:
- C7-T1 herniations make up 4-8% of cervical disc cases, but can cause disproportionate hand and grip impairment (Boden and colleagues, 1990).
- Up to 70% of C8 nerve root compressions show measurable loss in grip strength (Sampath and colleagues, 1999).
- Multi-level involvement with C6-C7 occurs in over 55% of chronic radiculopathy cases (Caridi and colleagues, 2011).
- Forward head posture increases cervicothoracic disc pressure by 10-15% for every 2.5 cm of anterior head shift (Neumann, 2017).
- C7-T1 facet joint degeneration is present in nearly 40% of adults over age 50 (Gore and colleagues, 1986).
- C8 is among the nerve roots affected less often in the neck; C7 accounts for more than half of all cases (Margetis and colleagues, 2025).
- In an X-ray study of 200 symptom-free adults, 95% of men aged 60 to 65 had at least one sign of wear. Among women of that age, it was 70% (Gore and colleagues, 1986).
Spatulated & Elongated TVP at C7: A Hidden Risk Factor
The transverse process (TVP) of C7 can vary anatomically:
- Elongated TVP: extends further sideways than average, narrowing the space for muscles, nerves or vessels.
- Spatulated TVP: a broad, flattened shape increasing mechanical contact with surrounding tissues.
Being a junction, C7-T1 is where I see this. The transverse process on one or both sides is longer or fatter than usual, and it looks taller on an X-ray.
Both variants can crowd the neurovascular structures between the neck and shoulder. That predisposes some people to thoracic outlet syndrome (TOS) symptoms, especially with poor posture or repetitive strain.
Thoracic Outlet Syndrome & Its Link to the Lower Neck
TOS occurs when nerves or blood vessels in the thoracic outlet are compressed. At C7-T1, this may be aggravated by:
- An elongated or spatulated C7 TVP narrowing the costoclavicular space.
- Cervical rib development at C7 altering the passageway for the brachial plexus and subclavian vessels.
- Disc herniation or joint degeneration at C7-T1 adding secondary nerve irritation.
Symptoms of Thoracic Outlet Syndrome or TOS can include numbness in the ring or little fingers, forearm weakness and coldness in the hand.
Cervical Rib & Disc Disorders
A cervical rib is an extra rib arising from C7. It may be complete, attaching to the first rib, or incomplete, ending in soft tissue. In many cases, cervical ribs are silent. In others, they cause nerve or vessel compression, contributing to TOS.
When combined with a C7-T1 disc herniation, both mechanical and inflammatory factors can affect nerve function. Complex symptoms in the neck, shoulder and hand can follow.
In my words: the ribs should begin at the first thoracic bone, but a few people have a rib at their seventh cervical vertebra. It can complicate the condition and mimic thoracic outlet syndrome.
It is often misdiagnosed as thoracic outlet syndrome. In other cases, C7-T1 trouble and thoracic outlet syndrome are both present. Yet neither is named as the main cause, with the other as an aggravating condition.
That is why you need an experienced clinician, whether your medical doctor, a specialist or a chiropractor who understands these conditions thoroughly.
Other Conditions That May Affect This Level
- Multi-level disc bulges involving C6-C7 and C7-T1.
- Cervicothoracic kyphosis altering load distribution.
- Facet arthropathy from chronic joint stress.
- Whiplash injuries causing ligament strain at the junction.
- Postural syndromes from prolonged device or desk use.
Non-Invasive Solutions for C7-T1 Conditions
At Chiropractic Specialty Center, C7-T1 care focuses on precision and safety to avoid aggravating the spinal cord and delicate nerve roots. Yoga is left out of that care: with a C7-T1 disc problem it must be avoided.
After the assessment, care has to be focused and, above all, non-harmful, non-rotatory and integrative. C7-T1 follows the same rules as the rest of the neck.
Realigning a vertebra, even without rotatory methods, is only part of the work. The muscles, the ligaments and the spinal disc also need rehabilitation, re-education and strengthening.
In most cases, I find scar tissue and adhesions in these fibers. They sit particularly in the capsular ligaments of the facet joints, at the back or the front. That is why I often recommend ultrasound or high-intensity laser therapy for them.
Gentle myofascial and trigger point releases go alongside.
Our program includes:
- Segment-specific mobilization without rotation for joint stiffness.
- Spinal decompression therapy aimed at disc pressure on the C8 nerve.
- High-intensity laser therapy (HILT) for deep tissue and nerve problems, alongside exercise.
- Targeted physiotherapy for posture correction and upper limb strength.
- Rehab exercises for grip, finger movement and shoulder stability.
- For teenagers and where a gentler contact is needed, chiropractic manipulation that is non-rotatory using the Activator instrument.
CSC's chiropractors and registered physiotherapists in KL work together so that C7-T1 care is specific to each patient's needs and goals. Asked whether to pick chiropractic or physiotherapy, my reply in Is Chiropractic Safe? 13 Questions Answered is: “Don't choose between one or the other. Choose both.”
Care is kept within what you can comfortably tolerate, and any method that hurts is softened at once. The motto I work by is “No pain, more gain.”
As Is Chiropractic Safe? 13 Questions Answered sets out, a plan that shows no change by the fifth session is reconsidered. The tenth session is where we decide the next step together.
For me, surgery is the final step, not the first. My words in Sciatica vs Slipped Disc: Video Explanation: “Surgery should be the last option. Exhaust conservative route.”
The possible effects and risks are explained before care begins. The fee for a plan is explained and agreed before care begins.
My Rule Against Twisting the Neck
If your neck problem brings radiating arm pain, numbness or tingling, keep it away from rotatory maneuvers. The same goes for neck pain with pain between the shoulder blades or down the chest.
Whether it is new or long-standing, with or without weakness, never let anyone crack or twist your neck with rotatory maneuvers or exercises. That includes a chiropractor, a physiotherapist, a medical doctor and an orthopedic surgeon.
Pain down the chest should also be checked by a doctor first, because the heart can cause it.
Many people with these problems are given the wrong exercises. Much of what online videos advise does not suit the lower neck, and even sound advice has to match the person in front of you. Every exercise needs to be customized.
Surgery, Injections and Nucleoplasty
In my words: the neck is one of the most mobile joints in the body. We nod, we turn, we look; it is always moving and cannot be immobilized.
Surgery often has to be repeated, and unfortunately it never brings the problem to an end. I believe wholeheartedly that surgery should be an option only once a targeted, focused conservative route has been exhausted.
Not just any conservative route. Many conservative therapies offered for the neck are of no use, and some will harm a person with a lower neck problem. Care has to be highly specific and personalized to the underlying condition. That means a plan drawn from what the imaging and examination findings document, not run-of-the-mill neck treatment.
My personal opinion: I do not recommend injections, and I do not recommend nucleoplasty, which in my view has no value. Over the years, I have seen hundreds of patients, if not more, with no improvement whatsoever after it.
In many instances they were worse. If an invasive procedure is needed at all, I recommend avoiding radiofrequency nucleoplasty into the disc or the facet joints. The same goes for any facet joint injection.
Some research points the same way. A 2025 Cochrane review found insufficient evidence to support nucleoplasty for arm pain from a neck disc herniation (de Rooij and colleagues, 2025). All four of its trials carried a high risk of bias.
In the lower back, a double-blind trial found no benefit from radiofrequency heat in the disc wall over a sham procedure (Kvarstein and colleagues, 2009). Its authors advised against the treatment.
A 2019 report in Radiology reviewed steroid injections into the hip and knee (Kompel and colleagues, 2019). Its title reads: “Perhaps Not as Safe as We Thought?” It described four kinds of joint damage seen after these injections:
- arthritis that progressed faster
- fractures in the bone just beneath the cartilage
- complications of bone death (osteonecrosis)
- rapid destruction of the joint, including bone loss
That report looked at the hip and knee, not the neck.
After fusion surgery at the front of the neck, new nerve or cord problems at a neighboring level appeared at about 2.9% a year. Within ten years, they were expected in 25.6% of patients (Hilibrand and colleagues, 1999).
Summary Table: C7-T1 Spine
| Feature | Details |
|---|---|
| Segment | C7-T1: cervicothoracic junction, the cervical-thoracic transition zone |
| Key functions | Transfers neck motion to the upper back; protects the C8 nerve |
| Common issues | Disc herniation, degeneration, postural strain, TOS from the TVP or a cervical rib |
| CSC approach | Gentle chiropractic, physiotherapy, decompression therapy |
A Second Kuala Lumpur Center
Readers in Bandar Sri Damansara, Kepong and Sungai Buloh have a nearer option. Read about the chiropractor in Bandar Sri Damansara with physiotherapy; that center provides chiropractic together with physiotherapy.
The address, telephone number and opening hours are listed on Bandar Sri Damansara address, hours and phone. Travel details for the main center are on Bukit Damansara address, hours and phone.
Fees are published: see the chiropractic price in Kuala Lumpur and physiotherapy fees in Kuala Lumpur before you come in.
Conclusion
C7-T1 issues can affect both neck function and hand dexterity. CSC's integrated chiropractic and physiotherapy model provides careful, segment-specific care.
Questions You Didn't Know to Ask
Can C7-T1 issues cause hand weakness without neck pain?
Yes. The C8 nerve root exits between C7 and T1 and controls grip strength, finger movement and part of the forearm's sensation. If this nerve is compressed, even without neck pain, you might notice dropping objects, difficulty buttoning shirts or a weaker grip during daily tasks.
This can happen when disc herniations or bone spurs at C7-T1 press directly on the nerve without irritating pain-sensitive structures in the neck.
Why is this junction more vulnerable in people with poor posture?
Forward head posture and rounded shoulders put constant load on the cervicothoracic junction. Unlike the more flexible upper neck, C7-T1 is a transition zone with limited mobility. Over time, this load can flatten the disc, irritate the facet joints and cause muscle imbalances. That makes this segment more prone to degeneration and nerve compression.
Can problems here affect shoulder mobility?
Yes. Pain and muscle guarding at the base of the neck can change how the shoulder blade is held and moves. That can bring reduced arm elevation, shoulder fatigue or compensatory strain in the rotator cuff. Patients often mistake this for a shoulder-only problem when the source is in the neck.
How is C7-T1 different from other cervical spine levels?
Most cervical levels are surrounded by other mobile neck joints. C7-T1, however, sits between the flexible cervical spine and the rigid thoracic spine. This makes it a stress concentration point, especially during heavy lifting, repetitive upper limb work or high-impact sports.
Its nerve root (C8) also serves very specific hand and forearm functions, so damage here produces a distinctive symptom pattern.
Why are high-force traction and Y-Strap pulls risky here?
High-force or uncontrolled traction methods, such as the Y-Strap, towel pulls or the Ring Dinger, can overstretch ligaments and irritate nerve roots. They can even stress the spinal cord at the cervicothoracic junction.
Because the C7-T1 area is anchored to the less flexible upper back, sudden traction forces are unevenly distributed, increasing the risk of injury. Safe care should focus on controlled, segment-specific mobilization rather than forceful jerks.
FAQ: C7-T1 Spinal Joint, Disc & Nerve Care
Why is the C7-T1 level important?
C7-T1 links neck mobility to upper back stability and protects the C8 nerve, which controls grip strength and finger movement. As the meeting point of a flexible and a stiff region, it takes more strain than the levels around it. Changes here can travel up the neck as a chain. That is why it is examined as part of the whole neck.
What symptoms occur with C7-T1 issues?
You may experience neck stiffness, shoulder weakness, grip problems and tingling in the ring and little fingers. Pain can sit at the base of the neck, and fine finger tasks can become clumsy. Symptoms in both hands, a change in walking or new bladder trouble suggest the spinal cord is involved. These need a prompt medical assessment.
How does CSC treat problems at this level?
CSC uses gentle mobilization, physiotherapy, decompression therapy and rehabilitation, with the aim of protecting nerve function and mobility. There is no twisting or cracking, and care is kept within what you can comfortably tolerate. The possible effects and risks are explained before care begins, and yoga is left out of any C7-T1 disc plan.
Where is C7-T1 located on the spine?
At the base of the neck, where the last neck bone, C7, meets the first upper back bone, T1. The bump most people feel there when they bend the head forward is usually the C7 spinous process, the vertebra prominens. C7-T1 sits just below it, roughly level with the tops of the shoulders.
What are the symptoms of C7-T1 nerve root compression?
Compression of the C8 root brings tingling or numbness in the ring and little fingers and the inner forearm. A weak grip and clumsy fine finger movements are common. If the T1 root is involved, the small hand muscles weaken, so spreading the fingers apart becomes hard. Weakness that keeps getting worse needs a prompt assessment.
What are the symptoms of a C7-T1 herniated disc?
A stiff neck with pain low down, tingling in the ring and little fingers, and a weaker grip are typical. In my view, a disc that shows as a simple bulge on the MRI does not press on the nerve. Arm and hand symptoms mean the disc is in transition, behaving like a protrusion or a herniation.
What is T1 radiculopathy?
It means the T1 nerve root, which leaves the spine just below T1, is irritated or compressed. The main signs are weakness of the small hand muscles, which spread the fingers and hold them together. Numbness on the inner side of the upper arm is another. It is less common than C6 or C7 problems, and the examination sorts it from the C8 root.
Which activities should be avoided with this disc problem?
Yoga must be avoided, and so must towel pulls, Y-Strap pulls and the Ring Dinger. Long hours with the head bent toward a laptop or phone load the junction too. With a painful neck, standing up every 15 to 20 minutes and moving for 30 seconds to a minute belongs in the plan. With a damaged disc, I keep to one rule: no twisting and no repetitive movements.
How to Read This Guide
I wrote this guide. Statements in the first person give my clinical positions, drawn from my videos, talks and written answers, and each quoted video is named. The figures in the statistics list are kept as I have them, with the studies read for this page listed beside them.
This guide describes C7-T1 in general. Each person's own symptoms need an examination to explain them.
Peer-Reviewed Medical References
- Aprill C, Dwyer A, Bogduk N. Cervical zygapophyseal joint pain patterns. II: A clinical evaluation. Spine (Phila Pa 1976). 1990;15(6):458-461.
- Boden SD, McCowin PR, Davis DO, Dina TS, Mark AS, Wiesel S. Abnormal magnetic-resonance scans of the cervical spine in asymptomatic subjects: a prospective investigation. J Bone Joint Surg Am. 1990;72(8):1178-1184.
- Caridi JM, Pumberger M, Hughes AP. Cervical radiculopathy: a review. HSS J. 2011;7(3):265-272.
- Centers for Disease Control and Prevention. Signs and symptoms of stroke. CDC; 2026.
- de Rooij JD, Verhagen AP, Harhangi BS, et al. Nucleoplasty for cervical radicular pain due to disc herniation. Cochrane Database Syst Rev. 2025;11:CD011852.
- Fernandez-de-las-Peñas C, et al. The influence of cervical spine dysfunction on upper quarter pain. Clin J Pain. 2006;22(3):230-236.
- Gore DR, Sepic SB, Gardner GM. Roentgenographic findings of the cervical spine in asymptomatic people. Spine (Phila Pa 1976). 1986;11(6):521-524.
- Hilibrand AS, Carlson GD, Palumbo MA, Jones PK, Bohlman HH. Radiculopathy and myelopathy at segments adjacent to the site of a previous anterior cervical arthrodesis. J Bone Joint Surg Am. 1999;81(4):519-528.
- Kaiser JT, Reddy V, Launico MV, Lugo-Pico JG. Anatomy, head and neck: cervical vertebrae. StatPearls. Treasure Island (FL): StatPearls Publishing; 2023.
- Kompel AJ, Roemer FW, Murakami AM, Diaz LE, Crema MD, Guermazi A. Intra-articular corticosteroid injections in the hip and knee: perhaps not as safe as we thought? Radiology. 2019;293(3):656-663.
- Kvarstein G, Måwe L, Indahl A, et al. A randomized double-blind controlled trial of intra-annular radiofrequency thermal disc therapy: a 12-month follow-up. Pain. 2009;145(3):279-286.
- Margetis K, Magnus W, Mesfin FB. Cervical radiculopathy. StatPearls. Treasure Island (FL): StatPearls Publishing; 2025.
- Mayo Clinic Staff. Spinal injury: first aid. Mayo Clinic; 2023.
- Neumann DA. Kinesiology of the Musculoskeletal System: Foundations for Rehabilitation. 3rd ed. Elsevier; 2017.
- Radhakrishnan K, Litchy WJ, O'Fallon WM, Kurland LT. Epidemiology of cervical radiculopathy: a population-based study from Rochester, Minnesota, 1976 through 1990. Brain. 1994;117(Pt 2):325-335.
- Sampath P, Bendebba M, Davis JD, Ducker T. Outcome in patients with cervical radiculopathy: prospective, multicenter study with independent clinical review. Spine (Phila Pa 1976). 1999;24(6):591-597.
- Sterling M, et al. Whiplash: clinical course and prognostic factors. J Orthop Sports Phys Ther. 2010;40(5):274-283.
These references cover neck anatomy, scan findings, nerve root problems, injections, nucleoplasty, disc heat treatment, neck surgery, stroke signs and first aid in general. None of them evaluates care at Chiropractic Specialty Center.
The Author of C7-T1 Nerve Root Compression Symptoms, Location and Pain
C7-T1 Nerve Root Compression Symptoms, Location and Pain was written by Yama Zafer, D.C., who has 30+ years in chiropractic and physiotherapy and founded Chiropractic Specialty Center in Kuala Lumpur in 2006.
Last Updated: C7-T1 Spine: Joint, Disc & Nerve Care in Kuala Lumpur
C7-T1 Spine: Joint, Disc & Nerve Care in Kuala Lumpur was last reviewed and updated on October 16, 2026.
Baca halaman ini dalam Bahasa Malaysia: Slip Disc C7-T1: Saraf C8, Jari Kelingking dan Rawatan Leher