


Back Pain Care by Spinal Segment: What It Involves
Back pain care at CSC uses non-twisting methods, which means the spine is not twisted in order to produce a click. Movement is restored instead through table-based techniques such as flexion-distraction and through instruments that deliver a small, fast impulse to one segment at a time, alongside the exercise that holds the change.
Order matters more than technique. The irritated segment is settled, the movement it has lost is restored, and it is then loaded enough for the change to persist. Omitting that last stage is the most common reason back pain returns, because pain settles well before capacity does. Work done between visits is where most of the durable change occurs.
This guide to back pain care by spinal segment, from L1-L2 to L5-S1 and the tailbone, is published by Chiropractic Specialty Center, Bukit Damansara (KL) main center: WhatsApp+60 17 269 1873 Call+603 2093 1000
Three Essentials in Segment-Aware Back Pain Care
- Segment-specific assessment: posture, movement and palpation from L1 to S1 and the tailbone, to identify which level or levels are contributing before non-invasive care is planned.
- Calm first, then build: gentle non-rotatory mobilization and movement re-education to settle the sensitive level, followed by core control that protects it.
- Planned checkpoints: progress is reviewed at set points, and loading is reintroduced in stages as the involved segment tolerates it.
What a Gentle, Non-Rotatory Plan Looks Like
Plans start calm and precise, with no forceful twisting and no end-range cracking, especially while inflammation is present.
How care begins
- Non-rotatory mobilization that targets the involved segment in very small ranges.
- No deep paraspinal pressure over sensitive spots.
- Methods chosen case by case, for example brief flexion-distraction to ease loading without rotation, SOT blocks and Activator for gentle alignment input, and angle-controlled decompression, high-intensity laser, ultrasound or low-setting focused shockwave when indicated.
When movement is added
Movement is added only once the sensitive level tolerates light contact without a flare. Spine-neutral movement re-education and core control that protect L4-L5 and L5-S1 are introduced in small, testable steps. Progress is reviewed at set checkpoints, for example at the fifth, tenth and fifteenth visit, and the plan is adjusted to the response.
How to choose a provider
Ask whether care stays non-rotatory during inflammatory phases, whether flexion-distraction, SOT and Activator are available, and whether sessions are short and comfort-first rather than long or forceful. Ask, too, whether examination findings are correlated with any available imaging before methods are chosen. This is educational guidance only; follow a plan only after a thorough assessment by a registered clinician.
Arranging an Assessment for Back Pain
To arrange an assessment for back pain, see the Bukit Damansara contact page and the Bandar Sri Damansara contact page, or call either center directly:
- Bukit Damansara (KL, main center): Call +603 2093 1000 or WhatsApp +60 17 269 1873 to see the Bukit Damansara / KL center.
- Bandar Sri Damansara (KL): Call +603 6262 5777 or WhatsApp +60 12 455 6939 to see the Bandar Sri Damansara center.
Segment-Specific Back Pain (L1-L2 to L5-S1 and Tailbone)
Back pain may arise from soft tissues, joints, discs or irritated nerves. The patterns below are common at each level, but individuals vary.
L1-L2 (upper lumbar)
- Often linked with a front-of-hip or groin ache, or upper-thigh tension.
- Typical issues: disc changes, small-joint irritation, hip-flexor strain.
- May feel worse with long sitting or sudden backward bending.
L2-L3
- Front-thigh fatigue or tightness; stiffness rising from sitting.
- Disc changes and joint irritation are common; quadriceps or iliotibial tension may show up.
- Prolonged or slumped sitting can aggravate it.
L3-L4
- Ache around the knee or front-outer thigh; pain on step-downs or squats.
- Disc changes, facet (small-joint) irritation and muscle imbalance are frequent.
- Often helped by posture work and gentle, non-rotatory segmental mobility.
L4-L5 (high-load segment)
- Buttock or outer-leg pain; sitting and bending feel tight.
- A common site for disc changes and joint irritation; recurrent strains are typical.
- Core control and hip mechanics matter at this level.
L5-S1 (lumbosacral junction)
- Low-central back pain, possibly with back-of-thigh tension.
- Disc changes, sacral-base stress and hamstring tightness are common contributors.
- Prolonged bent-forward postures or heavy lifting can flare symptoms.
Tailbone (coccyx)
- Pain when sitting on hard surfaces, or when leaning back.
- Often related to a fall, prolonged sitting or pelvic-floor tension.
- Cushioned sitting and gradual mobility are usually better tolerated.
Why Back Pain Has Become So Common
Low back pain is one of the leading causes of disability worldwide and a common reason for missed workdays. Four contributors come up again and again:
- Sitting for long periods.
- Too little physical activity.
- Neglecting a minor back problem.
- Care that does not match the cause.
Why Long Periods of Sitting Aggravate Back Pain
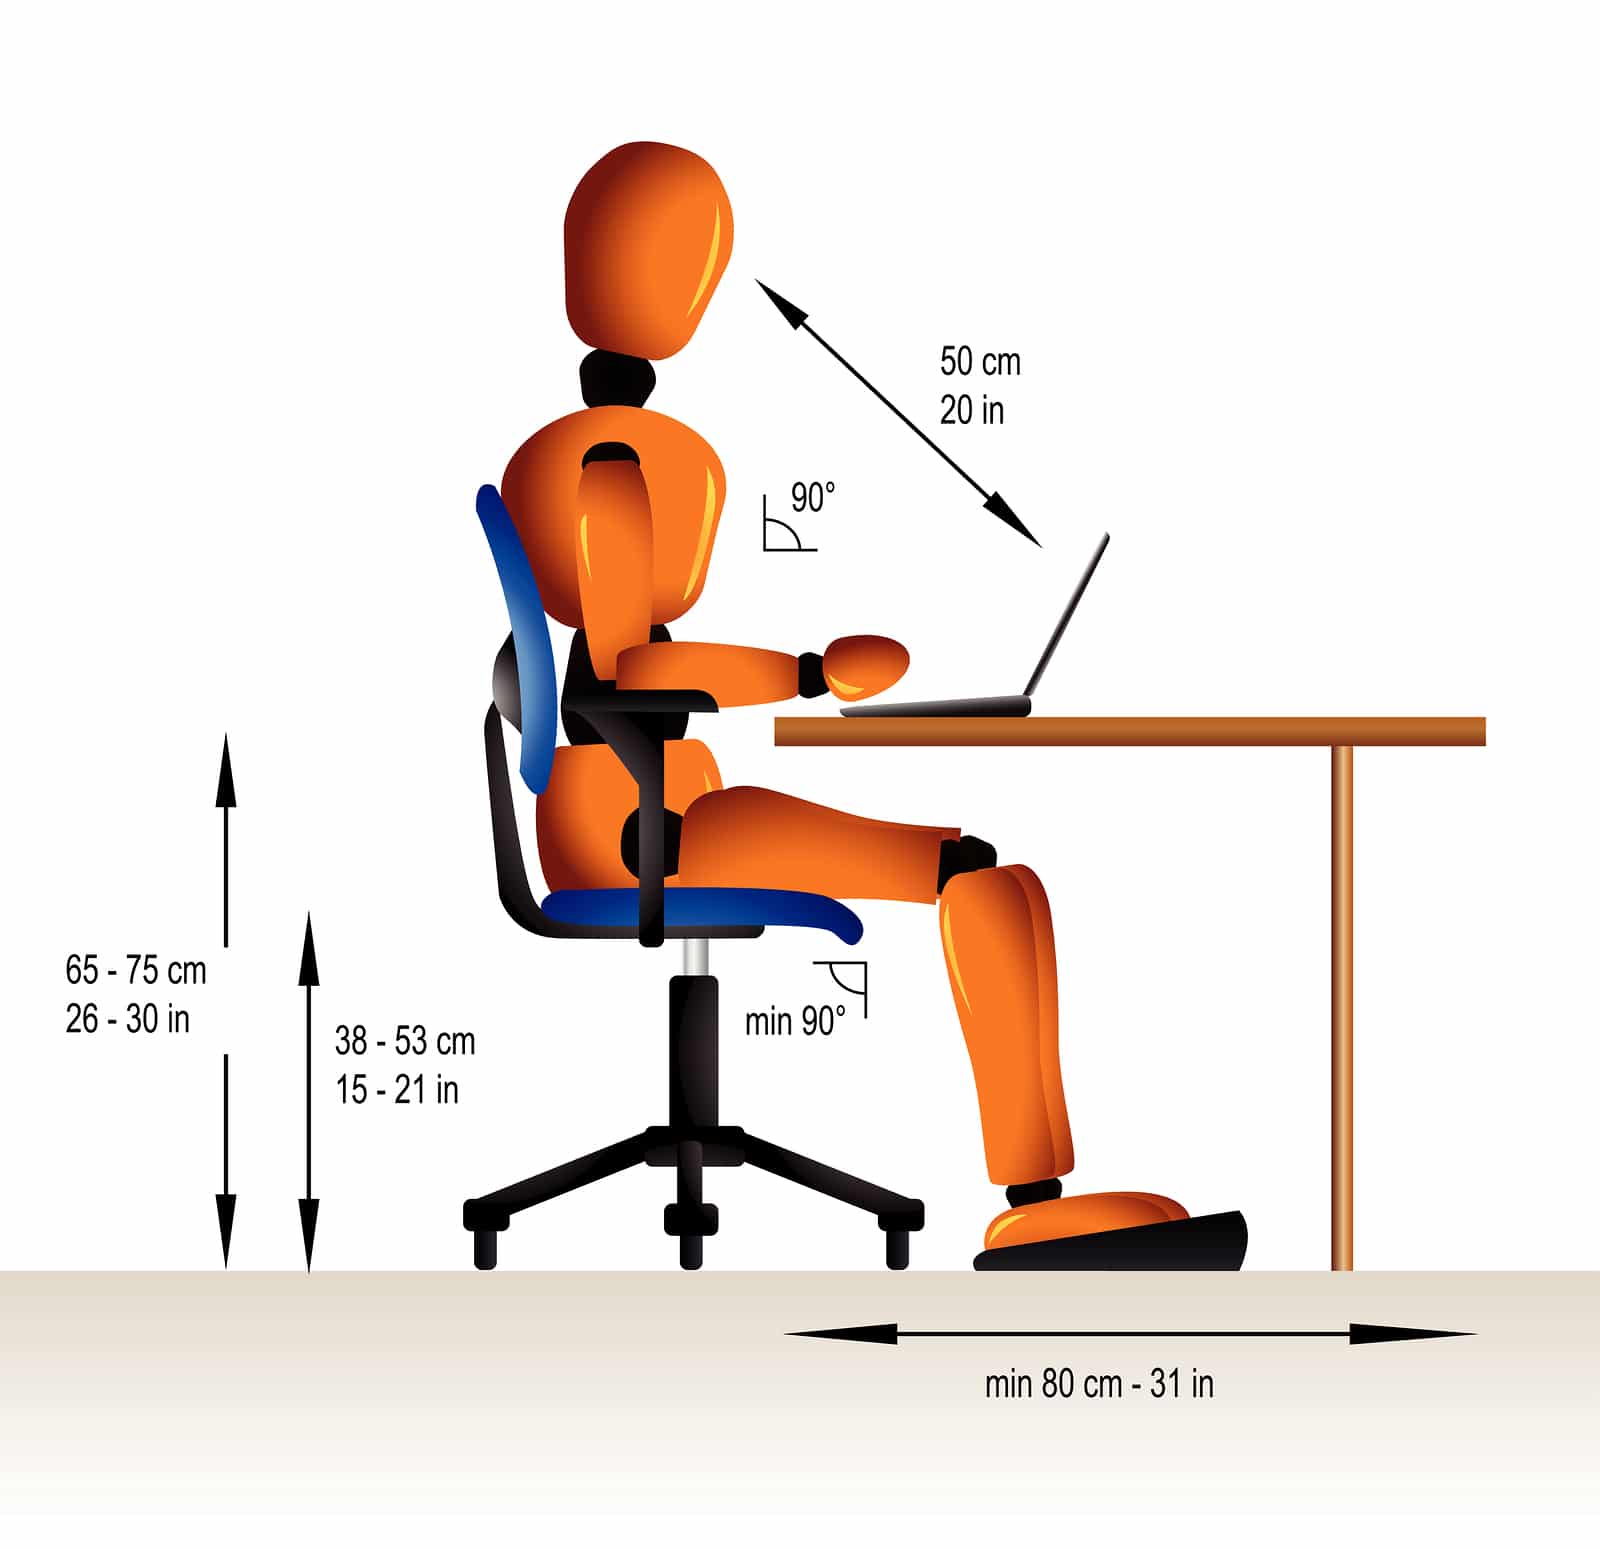
Pressure inside the lumbar discs changes with posture. In vivo measurements show that it is lowest lying down, higher standing, and higher again when sitting slumped or leaning forward, especially while lifting (Wilke HJ, et al. Spine. 1999;24(8):755-762). Long hours in one flexed position keep that load on the same structures.
Posture awareness matters most for people whose work involves sitting, particularly at a laptop, which tends to pull the spine into a slightly flexed position. You may not be able to avoid sitting, but you can change position often and break up long periods in one posture. If that is not enough on its own, an assessment can identify what else is contributing.
Do Not Neglect Minor Pain
It is easier to manage a simple problem than a complicated one such as a herniated disc. Some early care can start at home: an ice pack for up to 15 minutes, with a towel between the ice and the skin, can ease a recent flare. If the pain continues or returns, it is worth having it assessed.
Why the Cause Matters More Than the Sore Spot
Many centers in the Klang Valley offer care for back pain, and the methods vary widely. What separates them most is how carefully the cause is identified before care begins. An accurate diagnosis is the first step, and care that works out what is driving the pain is more useful than care aimed at the sore area alone.
Rotatory adjustments, in which the patient lies on the side and the spine is twisted, can feel satisfying, but in some cases they further irritate an inflamed joint capsule or disc. For that reason chiropractic and physiotherapy at CSC stay non-rotatory while the back is irritable.
Gentle, Well-Timed Physiotherapy
In the early stage, when joints, discs or soft tissues are irritable, forceful stretching, twisting or high-pressure techniques can flare symptoms. End-range stretches, deep paraspinal pressure and any maneuver that provokes pain are avoided. Mobility and strengthening are introduced once the tissues tolerate them.
- Heat and cold: hot packs can feel soothing, but during an inflammatory flare they may increase irritability, so heat is reserved for later phases.
- Manual work: deep myofascial release directly over the facets, spinous processes or paraspinal muscles can aggravate a sensitive back, so contact stays light until the spine settles.
- Ultrasound: when used, it is a dose-controlled modality, not a pressure massage. The applicator glides on a continuous layer of gel with light, even contact.
In short, the area is calmed first, and then movement re-education and progressive loading are added, always pain-aware and non-rotatory. More detail is on the physiotherapy page.
What to Do in the First Week
The first few days set the tone, and several instinctive responses work against recovery.
- Keep moving, in small doses. Bed rest tends to slow the return to normal activity. Short, frequent walks are better than lying down.
- Change position often. The position that hurts most is the one to break up, not the one to endure.
- Keep going to work if you can, even in a reduced form. Staying connected to normal activity is associated with better recovery than waiting until the pain has gone completely.
- Do not rush to a scan. Disc bulges, protrusions and degenerative changes appear on imaging in many people with no symptoms, and the proportion rises with age (Brinjikji W, et al. AJNR Am J Neuroradiol. 2015;36(4):811-816). An early scan often adds worry without changing the plan.
- Judge progress by function, not by the pain score: how far you walked, how long you sat, whether you slept.
Why Back Pain Comes Back, and What Reduces That
Recurrence is the part most people are not warned about. An episode settles, the exercises stop, and months later the pain returns. The useful question is not only how to make this episode settle but what to keep doing afterward.
- Exercise is the measure with the evidence. Exercise therapy reduces pain and improves function in chronic low back pain compared with no treatment or usual care (Hayden JA, et al. Cochrane Database Syst Rev. 2021;9:CD009790). The version that helps is the one you continue.
- Two sessions a week is a reasonable maintenance dose. It does not have to be the full rehabilitation program, but it does have to continue.
- Sleep and general activity matter. Both influence how much pain a given load produces.
- Building load tolerance works better than avoidance. A back that is protected from everything becomes less able to handle anything.
What Spine Surgery Aims to Do
Surgery can help selected cases, and it remains available if conservative care does not help, but for most mechanical back pain it is a distant last resort. The usual surgical goal is decompression: removing disc or bone material that is pressing on a nerve. Surgery addresses that one component. It does not by itself change the muscle, ligament, joint and movement factors that often contribute to back pain, which is one reason symptoms can recur if those are not also addressed.
Every operation carries risks, which can include increased pain, numbness or weakness in the legs and, rarely, more serious complications. If spine surgery has been suggested, a second opinion and a trial of appropriate conservative care are reasonable steps before a decision that cannot be reversed. The three most common procedures are outlined below.
Laminectomy
A laminectomy removes the lamina, the bony arch at the back of a vertebra that protects the spinal canal and anchors muscles. It is used to relieve pressure on the spinal cord or nerves, for example in spinal stenosis. Because bone and soft tissue are removed, some patients need a fusion at the same time to stabilize the segment, and recovery and recurrence vary from person to person.
Discectomy and Microdiscectomy

A discectomy removes disc material that is compressing a nerve root. A microdiscectomy removes a smaller portion through a smaller opening. Discectomy may be considered when conservative care has not been sufficient. It removes the disc material irritating the nerve; it does not address joint, muscle or movement factors, and outcomes vary.
Spinal Fusion
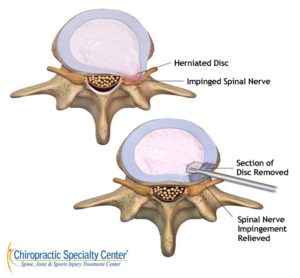
Spinal fusion joins two or more vertebrae so that they no longer move independently. It is often performed together with other procedures such as discectomy or laminectomy, for conditions such as spinal stenosis or instability. The loss of movement at the fused level can increase the load on the neighboring segments over time. Potential benefits and trade-offs should be discussed with the surgeon for each individual case.
In a large historical cohort of workers’ compensation patients with chronic low back pain, 26% of those who had a lumbar fusion had returned to work within two years, compared with 67% of similar patients managed without surgery. Among the fusion patients, 27% had a reoperation and 36% had complications, daily opioid use rose by 41% after surgery, and 76% continued to use opioids (Nguyen TH, et al. Spine. 2011;36(4):320-331). These results come from an observational study in a workers’ compensation setting and do not apply to every patient, but they show why a second opinion and conservative care are worth exploring before fusion.
NSD Therapy®: A Team-Based Plan for Back Pain
NSD Therapy® is not one machine or a single technique. It is a structured plan delivered by a chiropractor and physiotherapist team, aimed at calming irritated tissues and improving movement without forceful methods.
- It starts with a careful assessment of posture, movement and segment sensitivity.
- Care begins gently to settle the area; loading and exercise are added only when the back tolerates them.
- Depending on the findings, the plan may include angle-controlled spinal decompression, flexion-distraction, high-intensity (Class IV) laser, therapeutic ultrasound, electrotherapy, low-setting focused shockwave for tender points, and segment-specific, non-rotatory chiropractic mobilization.
- Each step stays comfortable, with no twisting and no deep pressure over sensitive spots.
It may be considered for ongoing back pain that tends to flare, whether it stays in the lower back or travels toward the hips or legs, after an individual evaluation. Sessions are short and stay within a comfortable range, with clear checkpoints to review progress and guidance on everyday movements as things settle.
Back Pain That Needs Prompt Medical Assessment
Most back pain is mechanical, but a few situations call for medical assessment rather than waiting:
- Even if your back or leg pain is familiar or longstanding, new or worsening numbness around your genitals, between your genitals and anus, or around your anus needs urgent medical attention: a thorough assessment by a competent clinician the same day. New difficulty passing urine needs the same, even while you still control your bladder and bowels, and so does any loss of that control. These changes can have several causes. Some may call for an invasive procedure, but assessment helps identify what has changed and the appropriate care; it does not automatically mean surgery.
- Weakness that is getting worse or a foot that drags should not be ignored. Have it assessed promptly by a competent provider; conservative care may still be a reasonable route once that assessment is done.
- Fever with back pain, or back pain after a recent infection, injection or procedure, needs urgent medical assessment.
- Unexplained weight loss, night pain that wakes you, or a history of cancer should be assessed promptly by a doctor.
- Back pain after a significant fall or collision, or in anyone with osteoporosis or long-term steroid use, should be checked for fracture.
Where Care Is Provided
Assessment and care are available at both Kuala Lumpur centers. The main one is described on the page for our Kuala Lumpur center in Bukit Damansara. A second center serves the northwest of the city; you can read about our Bandar Sri Damansara center. For travel, parking and opening hours, see the Bukit Damansara contact page and the Bandar Sri Damansara contact page.
Readers who want to know costs first can check the chiropractic price in Kuala Lumpur and physiotherapy price list in Kuala Lumpur pages.
FAQs: Back Pain
What is segment-specific back pain (L1-L2 to L5-S1 and tailbone)?
Back pain can start in soft tissues, small joints, discs or nearby nerves, and the pattern differs by level. L1-L2 tends to cause front-of-hip or groin tightness; L2-L3 front-thigh fatigue or stiffness rising from a chair; L3-L4 an ache around the knee or front-outer thigh; L4-L5 buttock or outer-leg tension; L5-S1 low-central back pain with a pull at the back of the thigh; and the tailbone pain on hard chairs or when leaning back. Your history and movement screen show which segment is sensitive, so care can be targeted.
What does a gentle, non-invasive plan look like?
It starts with a segment-specific assessment of posture, movement and palpation, with a review of existing imaging if available. Care begins with a calm-first phase with no twisting and no deep pressure over sensitive spots. Depending on the findings, the plan may include non-rotatory mobilization, carefully dosed modalities such as laser, ultrasound or low-setting focused shockwave, and spine-neutral movement re-education. As irritability settles, core control and graded loading are added. Progress is reviewed at set checkpoints and the plan is adjusted to the response.
Peer-Reviewed References
- McKenzie RA. The Lumbar Spine: Mechanical Diagnosis and Therapy. Waikanae, New Zealand: Spinal Publications; 1981.
- Wilke HJ, Neef P, Caimi M, Hoogland T, Claes LE. New in vivo measurements of pressures in the intervertebral disc in daily life. Spine (Phila Pa 1976). 1999;24(8):755-762.
- Rubinstein SM, de Zoete A, van Middelkoop M, Assendelft WJJ, de Boer MR, van Tulder MW. Benefits and harms of spinal manipulative therapy for the treatment of chronic low back pain: systematic review and meta-analysis of randomised controlled trials. BMJ. 2019;364:l689.
- O’Sullivan P. Diagnosis and classification of chronic low back pain disorders: maladaptive movement and motor control impairments as underlying mechanism. Man Ther. 2005;10(4):242-255.
- Saragiotto BT, Maher CG, Yamato TP, et al. Motor control exercise for chronic non-specific low-back pain. Cochrane Database Syst Rev. 2016;(1):CD012004.
- Nguyen TH, Randolph DC, Talmage J, Succop P, Travis R. Long-term outcomes of lumbar fusion among workers’ compensation subjects: a historical cohort study. Spine (Phila Pa 1976). 2011;36(4):320-331.
- Brinjikji W, Luetmer PH, Comstock B, et al. Systematic literature review of imaging features of spinal degeneration in asymptomatic populations. AJNR Am J Neuroradiol. 2015;36(4):811-816.
- Hayden JA, Ellis J, Ogilvie R, Malmivaara A, van Tulder MW. Exercise therapy for chronic low back pain. Cochrane Database Syst Rev. 2021;9(9):CD009790.
The Author of Back Pain Care: What Gentle, Non-Twisting Methods Mean
Back Pain Care: What Gentle, Non-Twisting Methods Mean was written by Yama Zafer, D.C., who has 30+ years in chiropractic and physiotherapy and founded Chiropractic Specialty Center in Kuala Lumpur in 2006.
Last Updated: Back Pain Care by Spinal Segment: What It Involves
Back Pain Care by Spinal Segment: What It Involves was last reviewed and updated on October 3, 2026.