Slip Disc Symptoms and What They Point To

Slip disc symptoms follow the nerve rather than the disc, which is why a lumbar disc problem is felt in the calf and a cervical one in the thumb or the little finger. Each nerve root supplies a defined strip of skin and a defined group of muscles, so the site of numbness and the pattern of weakness indicate which level is involved before any imaging is taken.

In my examinations the positional patterns are consistent. A lumbar disc usually worsens with sitting, bending forward and rising from a chair, and eases with walking. A cervical disc usually worsens with long spells of looking down and often eases when the arm rests on top of the head.

Slip disc symptoms most often affect the lower back and the neck, and they can reach the buttock, thigh, leg, shoulder or arm when a nearby nerve root is irritated. Stiffness, tingling, numbness, weakness and pain that keeps coming back are the usual signs. In my experience, neck or back pain that returns several times a year is one of the surest of them. Weakness is the sign that concerns me most. Many disc problems are cared for without surgery: my assessment matches the symptoms to the nerve involved, and gentle, non-rotatory chiropractic care, physiotherapy and guided rehabilitation are planned from what it finds.

For more information about slip disc symptoms, contact the Bukit Damansara (KL) main center: WhatsApp+60 17 269 1873 Call+603 2093 1000

Slip Disc Symptoms: Key Takeaways

PointWhat to know
Common symptomsPain in the neck or back that can travel into an arm or a leg, with stiffness, tingling, numbness or weakness along the path of the nerve.
Signs I watch forPain that returns several times a year and lasts a few days each time, pain on coughing, sneezing or turning over in bed, and pain that is worse at night.
Most serious signWeakness in an arm, hand or leg, because in my view it means the nerve is no longer working fully. It can appear with little or no pain.
Without symptomsDisc bulges show up on scans of many people with no back pain, about 30% at age 20 and 84% at age 80 in a review of 33 studies, so a scan is read together with the examination (Brinjikji et al., 2015).
WhereThe lower back is the most common site and the neck the second; in the lower back most occur at L4-L5 and L5-S1, and in the neck at C5-C6 and C6-C7.
Signs that cannot waitNew numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours.
Care at CSCFocused care planned from the examination and imaging findings: gentle, non-rotatory chiropractic care and physiotherapy together, with twisting and forceful methods avoided. Progress is reviewed by the fifth session.
Slip Disc Symptoms: Page Guide & Key Sections

What Are the Common Slip Disc Symptoms and Signs?

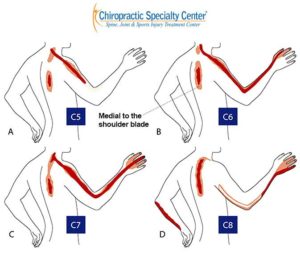
Four arm diagrams labeled C5 to C8, shading where pain from each neck nerve root can spread through the shoulder blade area, arm and hand

Disc problems are common, and in my experience many people who have one do not know the full range of symptoms it can cause. Slip disc, or slipped disc, is the everyday name for a disc that bulges, protrudes, prolapses or herniates. I use the name loosely, as most people do; in reality a disc does not slip.

A slip disc can occur anywhere along the spine, from the neck to the lower back. The lower back and the neck move the most, which helps explain why most disc problems occur there. A slip disc can also be present without noticeable pain, or with only mild signs. Early signs can be confusing, and a mild disc problem can resemble a muscle spasm or a spinal joint problem such as posterior facet syndrome or facet hypertrophy, which is why the examination matters.

I sort slip disc symptoms into two groups, classic and hidden.

Classic Symptoms

  • Pain in the neck or back
  • Pain affecting one side of the body
  • Pain that radiates into the hips, thighs, knees and legs
  • Pain in the shoulders, arms, elbows or wrists

The most common signs in the lower back are pain in the back, buttocks or legs, sometimes with numbness or tingling. The feeling is often cramp-like, around the lower back or the buttock, and at times it runs down the leg like sciatica, a feeling I describe in my video Bulging Disc vs Herniated Disc. From the neck, the same kind of problem can travel down the arm.

Pain in the neck, shoulders or lower back that returns several times a year is, to me, one of the surest signs of a disc problem. Each flare-up often lasts a few days or more. In my video Poor Posture Damages Your Spine, I make the point that no back pain should be called normal. Pain that comes and goes still deserves attention.

Hidden Symptoms

Less obvious symptoms can come from a disc problem as well:

  • Numbness or tingling in the upper back, shoulders, arms, wrists, hands or fingers
  • Numbness or tingling in the buttocks, thighs, legs, feet or toes
  • Pain or sensitivity when coughing or sneezing
  • Pain that increases at night
  • Symptoms that worsen with prolonged walking or standing
  • Weakness in the arms, legs, hands or feet
  • A burning sensation in the upper back, buttocks, hips, legs, shoulders or arms
  • Electric shock-like sensations in the arms, upper back or legs

A torn disc has a pattern of its own, which I describe in my talk Back Pain to Leg Pain. Pain can wake you as you roll over at night, a cough can stab through the back, and laughing can be uncomfortable, since each movement shakes the torn fibers.

Symptoms Without Neck or Back Pain

Some people come to me with symptoms only in an arm or a leg, and no neck or back pain at all. A disc can still be the cause. When the pain-sensing fibers of a badly damaged disc stop working, the disc can fall quiet while the nerve beside it keeps weakening. Weak legs with little or no back pain are a reason for an examination, not a reason to wait.

Symptoms From the Upper and Mid-Back

Disc problems between the shoulder blades are less common, because the upper and mid-back move far less than the neck or the lower back. When they occur, the pain can sit in the mid-back or run between the ribs and around the chest wall. A disc there that presses on the spinal cord can bring numbness, tingling or weakness in the legs or feet.

Arranging a Slip Disc Assessment in KL

A first visit starts with the history and an examination of the spine, the nerves to the arms or legs (strength, sensation and reflexes) and any X-ray or MRI report, so that the symptoms can be matched to a disc level before care options are discussed. I ask patients to bring the scans themselves on a CD or film, not just the written reports. A written note of their questions, what they have tried and how the symptoms have changed is useful too. Depending on the complexity, the assessment takes from 30 minutes to two hours, and I do not rush it. Addresses, opening hours and directions are on the Bukit Damansara and Bandar Sri Damansara contact pages. Either Kuala Lumpur center can arrange it:

Can a Slip Disc Exist Without Symptoms?
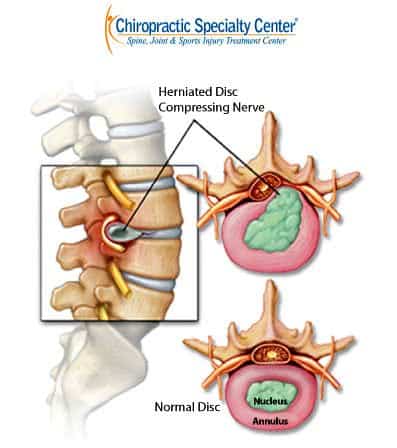
Side and top views comparing a herniated disc pressing on a spinal nerve with a normal disc, its nucleus and annulus labeled

Yes. A bulge or herniation can be present with few or no symptoms. In my talk Back Pain to Leg Pain I go further: zero is the most common symptom of spinal disc damage. Research points the same way. In a review of 33 imaging studies covering 3,110 people without back pain, disc bulges were found in 30% of 20-year-olds and 84% of 80-year-olds, and disc protrusions in 29% and 43% (Brinjikji et al., 2015). A finding on a scan is therefore read together with the symptoms and the examination.

A quiet disc still matters to me. As I say in the same talk, pain itself is not the enemy; ignoring it is. Mild symptoms that keep returning are worth having assessed before they grow.

Muscle Spasm or Slip Disc Symptoms?

In my experience, a disc problem is often first called a muscle spasm, and while that label sticks, the disc can go on worsening unnoticed. A true spasm usually follows a strain, an awkward movement or a long time in one position. The pain stays in the back or neck, the muscle feels tight and tender to touch, and it usually settles within days to a few weeks. Slip disc symptoms more often travel into the buttock and leg or the shoulder and arm along a nerve's path, can bring tingling, numbness or weakness, and tend to worsen with sitting, bending, coughing or sneezing.

The two often occur together, because muscles tighten around an irritated disc. In my video Neck Trigger Points and Exercises, I warn that joint, nerve and disc problems of the neck can all pass for muscle trouble at times. So I examine the nerves, the joints and the muscles before I call anything a spasm.

The lower back is the most common site of a disc problem, and the lower neck is the second. In the lower back, most occur at L4-L5 and L5-S1 and some at L3-L4; in the neck, most occur at C5-C6 and C6-C7 and some at C4-C5. In my talk Back Pain to Leg Pain I trace the lumbar order to bending: most of the forward bend at the waist happens at L4-L5.
Basic Facts About a Slip Disc

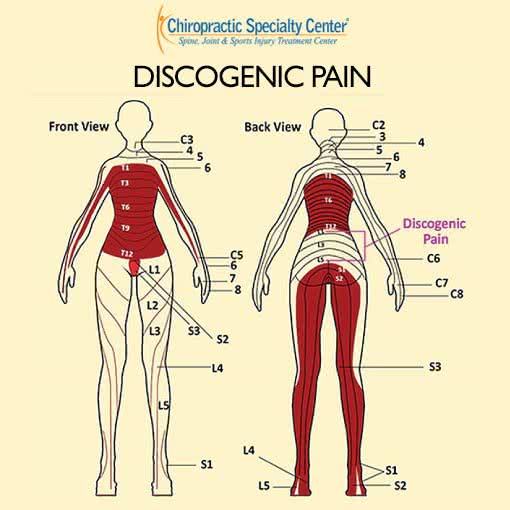
Front and back body charts titled Discogenic Pain, shading the areas where pain from neck and lower back discs can be felt, with the nerve root levels C3 to S3 labeled

A slip disc occurs when the soft, jelly-like inner portion of a spinal disc (the nucleus pulposus) pushes into or through its tougher outer layer (the annulus fibrosus). Radiologists describe the change as a bulge, a protrusion or an extrusion, according to how much of the disc's edge is involved and the shape of the displaced material (Fardon et al., 2014). It can cause pain when the disc material presses on or irritates a spinal nerve or, in the neck or upper back, the spinal cord.

In my own terms, the path starts with a degenerated or damaged disc. It then moves through stages, each a progression of the one before: a bulge, then a protrusion, a prolapse, a herniation (which I treat as the same as a rupture), an extrusion and finally a fragmentation. A true bulge, as I define it, does not press on a nerve. A report that calls a nerve-pressing disc a bulge is using the word loosely. The degenerative disc disease page sets out each stage.

The severity of symptoms varies with where the change occurs and whether it affects a nerve in the area.
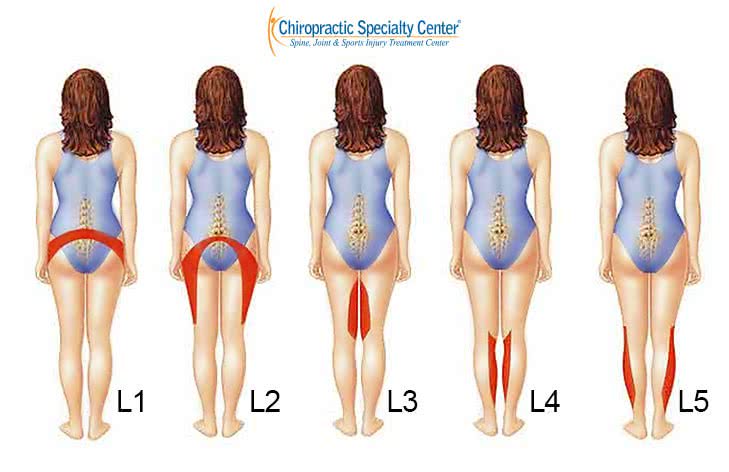
Five back views labeled L1 to L5, each shading where pain from that lumbar nerve root can be felt in the hips, thighs and legs

Why Slip Disc Symptoms Occur

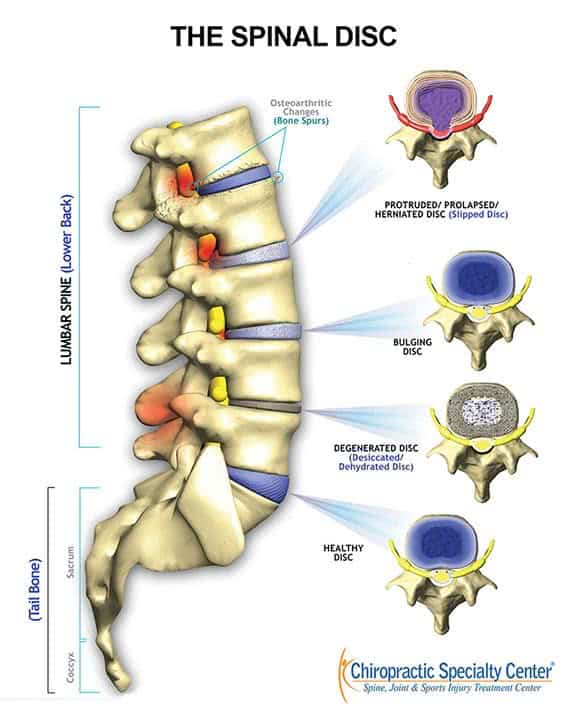
Side view of the lumbar spine with top views of a healthy disc, a degenerated (dehydrated) disc, a bulging disc and a protruded, prolapsed or herniated disc, and bone spurs from osteoarthritis

Spinal disc symptoms usually develop when structural changes inside the disc affect nearby nerves. A spinal disc has a soft inner center (the nucleus pulposus) surrounded by strong outer fibers called the annulus fibrosus. When these fibers weaken or develop small fissures, the inner material may begin to push outward.

In my view, where a tear sits matters as much as how large it is. A tear toward the front of the disc matters less than one at the back, which lies directly in front of the spinal canal and beside the openings where the nerves leave.

If the bulge or herniation approaches a nerve root, the nerve can become irritated. In many cases the symptoms are not caused only by pressure. Inflammation around the nerve root can also contribute to tingling, numbness, or radiating pain along the arm or leg.

The exact pattern of symptoms often follows a dermatomal distribution, meaning the nerve signals travel along predictable pathways in the body. This is why a spinal disc issue in the neck may cause symptoms into the shoulder, arm, or hand, while a disc issue in the lower back may influence the buttock, thigh, or leg. Clinicians call pain along the path of a nerve root radicular pain, and a loss of nerve function, such as numbness, weakness or a weaker reflex, radiculopathy. A neck disc pressing on the spinal cord can reach further still, down to weakness in the legs.

Conservative Approaches for Spinal Disc Issues

When I speak of conservative care for a disc, I mean focused care. Each plan is drawn from what the examination and imaging findings document, aims at those causes, covers the whole spine and does no harm. Routine back or neck treatment is not that, and many forms of it are of no use. Surgery comes into consideration only after focused care of that kind, properly given, has not worked.

MRI studies often show that a spinal disc issue may exist alongside several other structural changes. These may include ligamentum flavum thickening, facet joint enlargement, mild spinal canal narrowing, or muscular deconditioning. Because of this, conservative care is tailored to the specific combination of factors affecting the spine.

At Chiropractic Specialty Center, conservative care can combine gentle chiropractic methods, hands-on physiotherapy, machine-assisted physiotherapy, spinal decompression, cold therapy, and targeted strengthening and mobility exercises designed to improve spinal stability. Heat therapy and hot packs are kept off a spine with a disc problem.

A key principle is avoiding aggressive twisting or high-force manipulation when disc structures are vulnerable. Instead, the focus is on controlled, low-force methods that aim to restore motion while protecting the affected spinal structures. Care is kept within what you can comfortably tolerate. Discomfort during care means it is being done too aggressively, so tell the clinician at once.

For the same reason, I ask anyone with a disc problem to avoid yoga: many poses twist or bend a vulnerable disc, and yoga has no place at any stage of slip disc care at CSC.

The goal of conservative care is to improve spinal mechanics, reduce nerve irritation, and support the body's natural ability to stabilize the affected segment. My approach follows one principle: increase what is beneficial and decrease what is harmful. That takes an accurate diagnosis, a proper plan, careful execution with as few flaws as possible, and changes to posture, habits and daily activity. At the fifth session I review progress, and the plan changes if nothing has improved. Should there still be no improvement by the tenth, the patient and I decide together whether care continues.

Why Gentle Approaches Are Often Preferred for Disc-Related Issues

When spinal discs are weakened or structurally compromised, aggressive traction or twisting maneuvers can place additional stress on vulnerable tissues. For this reason, careful evaluation and gentle techniques are used at CSC when disc structures are involved. Rotary manipulation, the twisting kind, is a method I use only when I am 100% sure a spine has no disc damage. I give that rule in my video Sciatica vs Slipped Disc.

In my talk Back Pain to Leg Pain I describe the fastest worsening of a disc I have seen. It took ten days, after forceful treatment: a mild bulge on one MRI, and a severe herniation with a rupture on the next. High-force traction maneuvers sometimes seen online may appear dramatic, but the biomechanics of the cervical spine explain why cautious, controlled approaches are preferred.

Video: Why Forceful Neck Pulls May Increase Disc and Joint Stress

When spinal discs, joints, or wear-related cervical changes are present, sudden neck pulls and aggressive traction methods may place additional stress on already vulnerable tissues. In this video I explain how forceful neck traction affects cervical discs, joints, ligaments, nerve pathways, and nearby vascular structures, and why gentler, more controlled approaches are often preferred when disc-related issues are involved. As I put it there, a mild disc bulge can become a severe herniation under that kind of force.

Key moments and an edited transcript of this video are on our Neck Cracks Are Dangerous video page.

Key Moments From the Video

  • 00:00 Why Forceful Neck Pulls May Be Risky
    An overview of why sudden traction may increase stress across cervical discs, joints, and ligaments.
  • 00:14 Y-Strap and Ring Dinger Mechanics
    Explains how high-force traction methods load the cervical spine.
  • 00:38 Cervical Joints, Discs, and Ligaments
    A focused explanation of the structures commonly affected during sudden pulling maneuvers.
  • 01:11 Nerve Pathways and Vertebral Arteries
    Explains why nearby nerves and vascular structures require careful consideration.
  • 01:45 Spondylosis and Force Tolerance
    Explains why disc degeneration, bone spurs, and cervical spondylosis may reduce tolerance to sudden force.
  • 02:14 When Aggressive Pulls Become More Dangerous
    A key section for people with existing disc bulges, protrusions, or degenerative changes.
  • 02:51 Bone Spurs and Uncovertebral Joint Changes
    Shows how wear-related cervical changes may increase vulnerability.
  • 03:38 Vertebral Artery Considerations
    A focused explanation of how vascular structures may be affected.
  • 05:32 Who May Be More Vulnerable
    Discusses disc-related and age-related factors that may increase risk.
  • 09:19 How Cervical Discs Respond to Sudden Force
    Explains how a mild disc bulge can become a herniation, and how annular tears appear on MRI reports.
  • 09:38 Gentle vs Aggressive Cervical Approaches
    Explains why neck care should be safe, focused and specific, and never aggressive or violent.

Slip Disc Symptoms in Younger Adults and Teenagers

Slip discs were once thought of mainly as a problem of older adults, but I now see a growing number of younger adults and teenagers with disc symptoms. Long hours of sitting and of looking down at phones and tablets are common in their histories. My youngest spinal disc patient was a seven-year-old girl, and her herniation was not mild but moderate, bordering on severe. Age is only one factor, alongside genetics, daily habits, posture and earlier injuries. The symptoms are the same at any age, so the signs on this page apply to them too.

How Postural Habits Influence Spinal Disc Health

Modern lifestyle habits play a major role in how spinal discs respond to daily stress. Sitting upright loads the lower back with the weight of the whole upper body, and leaning forward adds more. Prolonged sitting, sustained forward-head posture, and repetitive bending can gradually increase mechanical pressure on the discs of the spine.

Over time, these mechanical stresses may contribute to disc dehydration, reduced resilience of the outer fibers, and increased vulnerability to bulging or herniation. While symptoms are active, I ask patients to stand and walk for 30 seconds to a minute after every 15 to 20 minutes of sitting. For someone with no back problem, every 30 to 40 minutes will do. In the video below I put it simply: take care of your posture, and your spine will take care of you.

For the chapter list and the transcript, open the Poor Posture Spine video page.

How Serious Are Slip Disc Symptoms?

Pain is a poor measure of a disc. In my talk Back Pain to Leg Pain I say that pain is not a yardstick but a symptom. Severe neck or back pain does not always mean a large herniation, and a large herniation can come with little pain. So I never judge a disc by the pain alone. The examination of strength, sensation and reflexes, read with the imaging, tells me more.

Of all the signs, weakness concerns me most, because it shows that a nerve is no longer working fully. Numbness that spreads, or a hand or foot that stops doing what it should, is a reason to be examined soon. Waiting for the pain to settle is not enough.

A damaged disc can also change at very different speeds: in my experience it can worsen quickly or over years. On the disc bulge page I explain the 0 to 10 scale I use to rate how serious a disc finding is.

When Spinal Disc Symptoms Should Be Assessed

Most spinal disc symptoms develop gradually and can often be managed through focused conservative care.

If slip disc symptoms include back or leg pain, get urgent medical attention, a thorough assessment at a hospital emergency department straight away, within hours, if numbness develops or worsens around your genitals, between your genitals and anus, or around your anus. New difficulty passing urine needs the same urgent assessment; loss of bladder or bowel control does not have to occur first, and if it does occur, it is urgent too. These symptoms have several possible causes. Some may call for an invasive procedure, but the assessment determines what care is appropriate, rather than assuming surgery is necessary.

Leg weakness that keeps getting worse should not be ignored. It calls for a careful assessment by a competent provider, and conservative care can continue only while the weakness itself is improving. The same applies to weakness in an arm or hand that keeps getting worse, and to walking that becomes unsteady.

Back Pain to Leg Pain Video: Disc or Sciatica?

In this recorded talk, I explain how slip disc symptoms develop, why they can travel into the leg or arm, and how non-surgical care is structured. It covers disc anatomy, pressure changes during sitting and sleep, symptom patterns linked to nerve irritation, and the stages of disc bulge, protrusion and herniation.

The chapters of this talk, each with a short summary, are on the Back Pain to Leg Pain video page.

Key Moments From the Lecture

  • 00:00 Spinal Disc and Neck Problems Are Common
    How common neck and back problems are, and how far their symptoms can reach, from mild neck stiffness to arm symptoms and weakness in the legs.
  • 02:43 Understanding the Neck, Mid-Back, and Lower Back
    A clear explanation of how the spine works as one connected system and how strain in one area may affect another.
  • 06:22 Spinal Disc Anatomy Explained
    A simple walkthrough of the nucleus pulposus and annulus fibrosus and how discs handle pressure.
  • 18:30 Healthy Disc vs Damaged Disc
    A side-by-side look at a disc whose fibers hold the nucleus in place and one whose torn fibers let it migrate toward the nerve.
  • 28:49 Stages of Disc Change
    Explains the difference between disc bulge, protrusion, prolapse, and herniation.
  • 38:00 Pressure Inside the Disc
    Why a disc under high internal pressure cannot draw in the nutrients it needs, explained with a pressure-cooker comparison.
  • 45:12 Standing vs Sitting Pressure Differences
    Shows how body position changes mechanical pressure across spinal discs.
  • 57:13 Deadlifts and the Ligamentum Flavum
    How heavy deadlifts may thicken the ligamentum flavum, the ligament at the back of the spinal canal, and why that matters as a disc wears.
  • 1:12:46 Sciatica and Nerve Root Irritation
    A focused explanation of why symptoms may travel into the leg.
  • 1:33:12 Cracking, Surgery and Conservative Care
    Why cracking and twisting are avoided on a damaged disc, and why surgery is kept as the last option after a condition-based conservative route.

Is Chiropractic Safe? 13 Common Questions Explained

In this video I answer common questions about chiropractic: whether it is considered safe, what causes the cracking sound, when an MRI may be more helpful than an X-ray, and how chiropractic and physiotherapy work together. It also covers imaging, spinal disc considerations, knee mechanics, ergonomics, and how gentle chiropractic joint mobilization is approached. For a suspected disc problem, I call the MRI the gold standard. It carries no radiation, and it shows the disc, the nerves and the room around them along with the bone; an X-ray shows bone alone.

To jump to a part of this video or read along, see the Is Chiropractic Safe video page.

Key Moments From the Video

00:00 Safety, Imaging, and What the Video Covers
A quick overview of the most common questions about chiropractic, physiotherapy, spinal imaging, and care expectations.

00:33 Is Chiropractic Considered Safe?
A direct explanation of safety considerations, gentle methods, and why proper assessment matters.

01:35 Gonstead, Diversified and Methods That Avoid Twisting
Explains two standard methods and the gentler, non-rotatory options used when a disc is involved.

02:44 Why Safety Depends on the Chiropractor and the Technique
A useful section on how spinal disc issues may influence technique selection and why gentler approaches are often preferred.

03:02 Who Should Perform Chiropractic Methods?
Explains why professional training and assessment are important before any spinal methods are considered.

04:01 What Causes the Cracking Sound?
Explains what commonly creates the popping or cracking sound during chiropractic joint mobilization.

04:22 Techniques That Make the Sound, and the Activator
A simple explanation of the methods that tend to produce the sound and the Activator option for worn joints.

05:28 Does Chiropractic Only Focus on the Spine?
Discusses how knee, shoulder, and joint mechanics may also be considered.

06:06 Knee Mechanics and Joint Function
Explains how a knee out of alignment may stress the meniscus.

07:27 What Sessions Commonly Feel Like
A practical explanation of comfort levels and what people commonly expect.

11:16 When X-Ray or MRI May Be Recommended
An educational section on when imaging is and is not needed.

12:46 MRI vs X-Ray Explained
Shows when MRI may provide clearer soft-tissue and disc information.

13:42 Sciatic-Type Symptoms
Explains common considerations when symptoms travel into the leg.

14:56 Chiropractic or Physiotherapy?
Explains how these approaches may work separately or together.

15:35 What Holistic Care Means
Explains integrative care involving chiropractic, physiotherapy, and rehabilitation.

Common Questions About Slip Disc Symptoms

Can a slip disc heal without surgery?

Many slip disc problems settle with focused conservative care and changes to daily habits. Surgery comes last, kept for when that care, properly given, has not worked. The exception is urgent: new numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours. In my view no treatment, surgery included, returns a damaged disc fully to its original state, so the aim is a disc that stays settled under daily load. At CSC, care combines gentle, non-rotatory chiropractic care, physiotherapy, spinal decompression and guided rehabilitation, planned from the assessment, and progress is checked by repeating the tests from the first visit.

Do all disc bulges cause symptoms?

No. Disc bulges are common in people who have no back pain at all. A review of 33 imaging studies covering 3,110 people without symptoms found disc bulges in 30% of 20-year-olds and 84% of 80-year-olds (Brinjikji et al., 2015). That is why a bulge on an MRI report is matched to the symptoms and the examination: the level of the bulge should fit the nerve pattern, the positions that worsen or ease the pain, and the findings on strength, sensation and reflexes before it is treated as the cause. Where a report shows only a bulge but the arm or leg has symptoms, I call it a disc bulge in transition: the disc reads as a bulge while you lie still in the scanner, yet under body weight, sitting or standing, it can push further out and reach a nerve.

Why do slip disc symptoms travel down the arm or leg?

Each nerve root that leaves the spine supplies a defined strip of skin and a defined group of muscles. When a disc irritates or presses on a root, through direct pressure or the inflammation around it, the symptoms are felt along that root's path rather than at the disc. That is why a lumbar disc problem can be felt in the buttock, calf or foot, and a cervical one in the shoulder blade, arm, thumb or little finger. The site of numbness and the pattern of weakness point to the level involved.

Is chiropractic safe for a slip disc?

Chiropractic care is safe, in my view, when a registered chiropractor delivers it correctly and plans it from the condition, and problems come from the methods a practitioner chooses. With a disc problem, I avoid twisting and forceful manipulation, because rotation can aggravate a disc. Instead, care at CSC uses flexion-distraction and chiropractic manipulation that is non-rotatory using the Activator instrument, alongside physiotherapy and spinal decompression. Care is kept within what you can comfortably tolerate. Discomfort during care means it is being done too aggressively, so tell the clinician at once. An examination, and imaging when a disc problem is suspected, comes before any adjustment.

How is a muscle spasm told apart from slip disc symptoms?

A spasm usually starts after a strain, an awkward movement or a long time held in one position, stays in the back or neck, and leaves the muscle tight and tender to the touch. Disc symptoms more often spread into the buttock and leg or the shoulder and arm along the path of a nerve, and can bring tingling, numbness or weakness; sitting, bending, coughing or sneezing tend to make them worse. The two often occur together, so an examination of the nerves, strength and reflexes is what separates them.

When do slip disc symptoms need urgent attention?

New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours. Leg weakness that keeps getting worse should not be ignored. It calls for a careful assessment by a competent provider, and conservative care can continue only while the weakness itself is improving. Without these signs, most disc symptoms develop gradually and can be assessed calmly, starting with a history and an examination of the nerves to the arms and legs.

Can a slip disc in the neck cause symptoms in the legs?

It can. When a disc in the neck presses on the spinal cord rather than a single nerve root, the effects can reach the legs. They include weakness, legs that feel heavy or unsteady, and trouble walking or standing, a pattern I cover in my talk Back Pain to Leg Pain. Clumsy hands can come with it. Signs like these call for a prompt, careful examination. In my view an MRI of the neck is the clearest way to see the cord and the disc together. With a neck problem, any new change in bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours.

Do painkillers or supplements settle a slip disc?

Painkillers and anti-inflammatory medicines can ease symptoms for a while, and decisions about them belong with your doctor. In my view they do not change the disc itself, because a slipped disc is a mechanical problem. Supplements are no different. Whatever glucosamine, chondroitin, MSM or hyaluronic acid may do elsewhere, none of them builds a disc back up. I make that point in my talk Back Pain to Leg Pain, and it is why my plans center on load, posture, sleep and focused treatment.

What should I do at home while slip disc symptoms are active?

Keep the load on the disc low. While symptoms are active, stand and walk for 30 seconds to a minute after every 15 to 20 minutes of sitting, and avoid bending, twisting, lifting and yoga. Easy walking on level ground is welcome. Sleep for six hours at the very least, and for seven to eight without waking where you can. Side-lying with a straight spine and a bolster between the knees suits most people; lying on the back works too, with a bolster beneath the knees. On a damaged disc I choose cold over heat: a cold pack wrapped in a cloth, 10 to 15 minutes at a time, two or three times daily, with at least two hours between rounds. For a lower back disc, Kegel exercises can start at once; other exercise waits until the examination shows the disc has settled.

This page is general education about slip disc symptoms. It cannot diagnose a disc problem or assess anyone's own symptoms; that takes an examination by a qualified clinician.

References

  1. Fardon DF, Williams AL, Dohring EJ, Murtagh FR, Gabriel Rothman SL, Sze GK. Lumbar disc nomenclature: version 2.0: recommendations of the combined task forces of the North American Spine Society, the American Society of Spine Radiology, and the American Society of Neuroradiology. Spine (Phila Pa 1976). 2014;39(24):E1448-E1465.
  2. Brinjikji W, Luetmer PH, Comstock B, et al. Systematic literature review of imaging features of spinal degeneration in asymptomatic populations. AJNR Am J Neuroradiol. 2015;36(4):811-816.
  3. Deyo RA, Mirza SK. Herniated lumbar intervertebral disk. N Engl J Med. 2016;374(18):1763-1772.
  4. Hahne AJ, Ford JJ, McMeeken JM. Conservative management of lumbar disc herniation with associated radiculopathy: a systematic review. Spine (Phila Pa 1976). 2010;35(11):E488-E504.
  5. Leininger B, Bronfort G, Evans R, Reiter T. Spinal manipulation or mobilization for radiculopathy: a systematic review. Phys Med Rehabil Clin N Am. 2011;22(1):105-125.

These references describe spinal disc problems and their care in general. None of them evaluates care at Chiropractic Specialty Center.

The Author of Slip Disc Symptoms in KL | Signs & Care Options

Slip Disc Symptoms in KL | Signs & Care Options was written by Yama Zafer, D.C., who has 30+ years in chiropractic and physiotherapy and founded Chiropractic Specialty Center in Kuala Lumpur in 2006.

Last Updated: Slip Disc Symptoms and What They Point To

Slip Disc Symptoms and What They Point To was last reviewed and updated on October 16, 2026.